Nausea and vomiting are common symptoms that can reduce quality of life and indicate life-threatening illness. Acute nausea and vomiting last up to 7 days. In the absence of alarm symptoms, they are typically treated symptomatically and without an extensive evaluation. Typical causes include gastroenteritis or other viral syndromes, foodborne illness, acute migraine headaches, vestibular disturbances, early pregnancy, and adverse effects of medication. Chronic nausea and vomiting last 4 weeks or longer and have a broad differential diagnosis. Causes can be gastrointestinal, infectious, metabolic, neurologic, psychiatric, or related to medications and toxins. A careful history of related factors is essential to guide the initial evaluation and narrow the differential diagnosis. These factors include associated symptoms, timing of onset and duration of symptoms, exacerbating or relieving factors, alarm symptoms, medication and substance use, relationship with recent food ingestion, and comorbidities. Nonpharmacologic management options include fluid and electrolyte replacement; small, frequent meals; and avoidance of trigger foods. Antiemetic drugs effectively reduce symptoms of acute nausea and vomiting, but chronic symptoms are often more challenging to treat. When a specific etiology is not identified, a serotonin antagonist or dopamine antagonist can be used. However, medications may also target the suspected cause of symptoms and the neurotransmitters involved in central and peripheral pathways of nausea and vomiting. Pharmacologic therapy should be used for the shortest time necessary to control symptoms.
Nausea and vomiting are common symptoms that lead patients to visit family physicians. Although usually self-limiting, they are significant causes of reduced quality of life and can indicate life-threatening illness.1,2
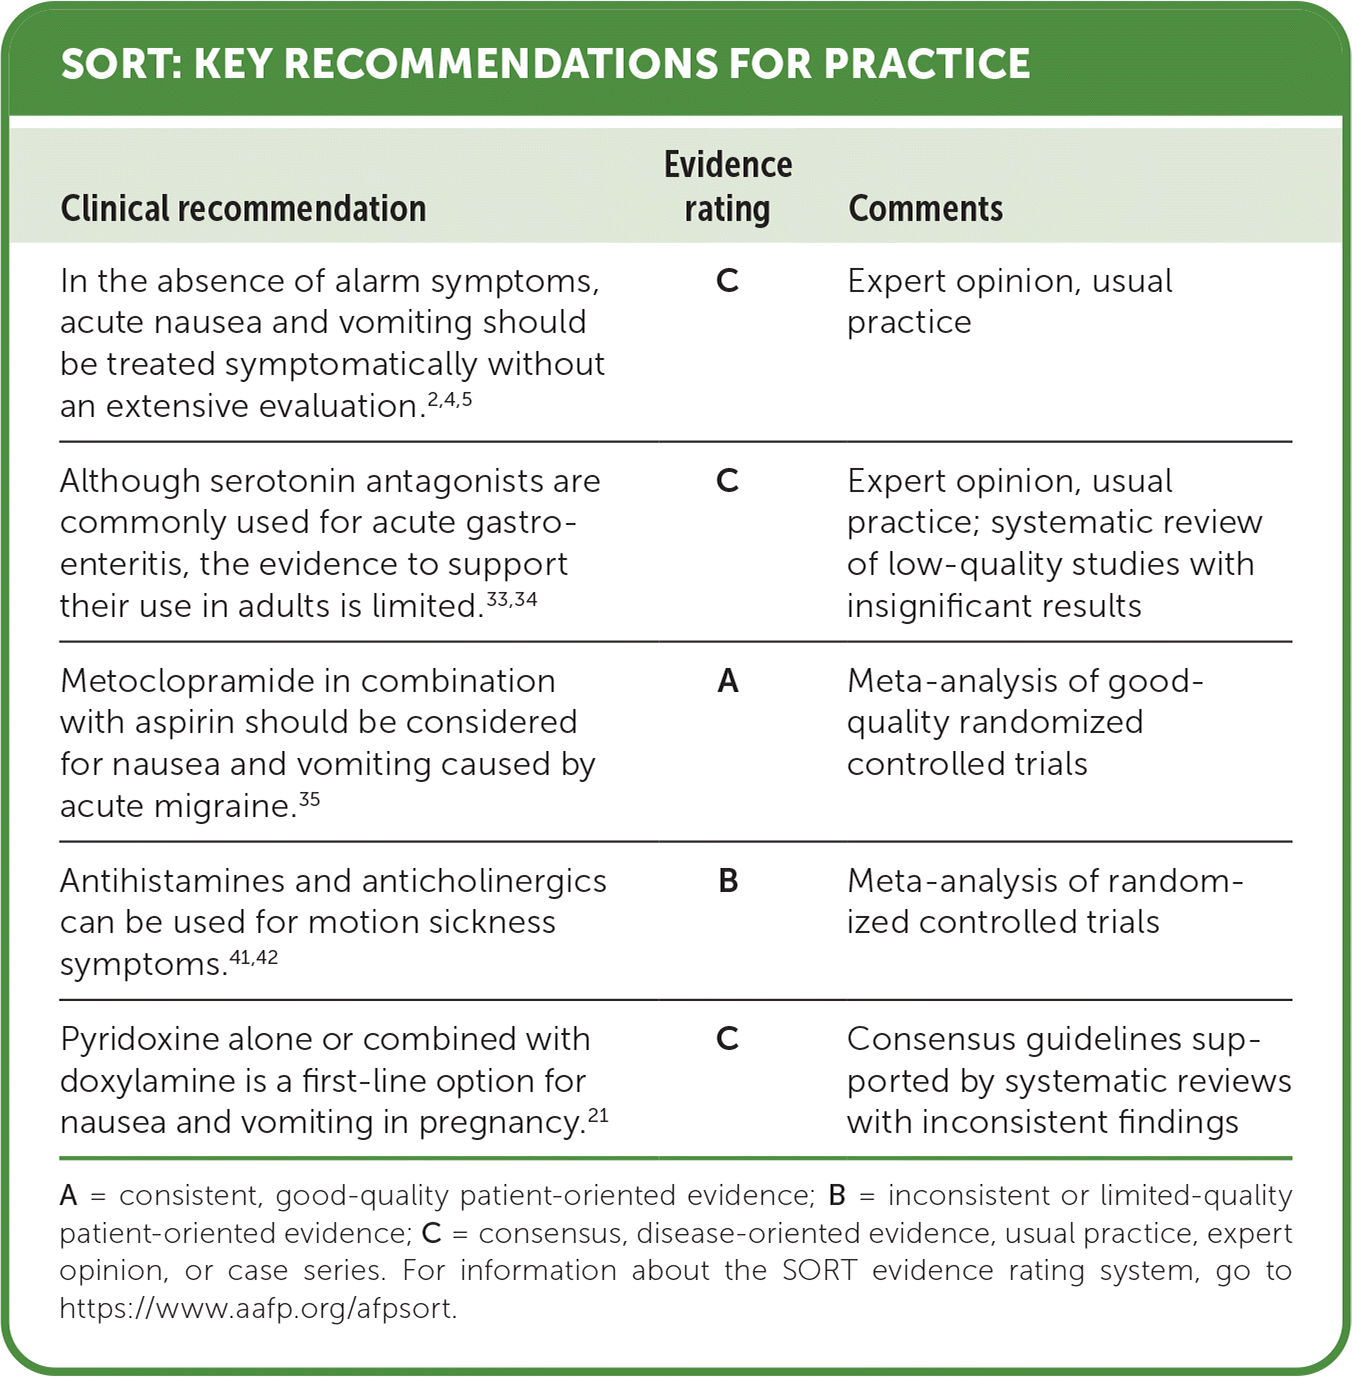
SORT: KEY RECOMMENDATIONS FOR PRACTICE
| Clinical recommendation | Evidence rating | Comments |
|---|---|---|
| In the absence of alarm symptoms, acute nausea and vomiting should be treated symptomatically without an extensive evaluation.2,4,5 | C | Expert opinion, usual practice |
| Although serotonin antagonists are commonly used for acute gastroenteritis, the evidence to support their use in adults is limited.33,34 | C | Expert opinion, usual practice; systematic review of low-quality studies with insignificant results |
| Metoclopramide in combination with aspirin should be considered for nausea and vomiting caused by acute migraine.35 | A | Meta-analysis of good-quality randomized controlled trials |
| Antihistamines and anticholinergics can be used for motion sickness symptoms.41,42 | B | Meta-analysis of randomized controlled trials |
| Pyridoxine alone or combined with doxylamine is a first-line option for nausea and vomiting in pregnancy.21 | C | Consensus guidelines supported by systematic reviews with inconsistent findings |
A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.
Nausea is the unpleasant sensation that vomiting might occur, whereas vomiting is the forceful expulsion of gastric contents from the mouth. Vomiting should be distinguished from regurgitation, the involuntary reflux of gastric contents into the esophagus and sometimes mouth without abdominal wall contractions, and from rumination, which is the voluntary, effortless flow of gastric contents into the mouth, where they are typically rechewed and swallowed. Retching involves spasmodic contractions with a closed glottis; it often precedes vomiting.3
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.