Substance misuse and substance use disorder continue to be major causes of morbidity and mortality, and family physicians are well positioned to provide evidence-based prevention and management for these conditions. Of people 12 years and older, 13% reported using a nonprescribed controlled substance in the past month, and 24% had at least one episode of binge drinking of alcohol, defined as five or more drinks for men and four or more drinks for women on one occasion. Benzodiazepines are used by 12% of the U.S. population. Clinicians should incorporate standardized screening and brief intervention for use of alcohol and other substances into routine care of adult patients, as well as referral to specialized treatment services when indicated. Use of nonstigmatizing, person-first language has been shown to positively affect care for patients with substance use disorders. Alcohol screening and brief intervention have been shown to reduce excessive drinking by 40% in patients at 6 months postintervention. Office-based treatment of alcohol use disorder with medications approved by the U.S. Food and Drug Administration, such as acamprosate and naltrexone, remains underutilized, presenting another opportunity for family physicians to positively affect the health of their patients and communities. With elimination of the X-waiver, any clinician with Schedule III prescriptive authority can treat opioid use disorder with buprenorphine in their office-based practice. Opioid overdose education and naloxone coprescribing are other tools family physicians can employ to combat the overdose crisis.
The medical approach to substance use has significantly changed over the past decade. Decreases in opioid prescribing and increases in synthetic opioid availability have fueled a crisis of overdose deaths, exceeding 100,000 U.S. deaths annually.1 In response, research and funding priorities have shifted, and the medical profession has adopted new tools for prevention, screening, assessment, and treatment. The American Academy of Family Physicians strongly supports family physicians and residents incorporating diagnosis, treatment, and prevention of substance use disorders (SUDs) into their routine clinical practices.2,3 For purposes of this article, “substance use disorder” indicates that an individual meets the specicfic Diagnostic and Statistical Manual of Mental Disorders, 5th ed. (DSM-5), criteria for a substance use disorder 4; substance misuse indicates not meeting those criteria for the disorder and using in hazardous situations or above limits for low-risk alcohol use. This article shares key updates in the primary care field and focuses on adult care. An article focusing on adolescents has been previously published in American Family Physician.5
SORT: KEY RECOMMENDATIONS FOR PRACTICE
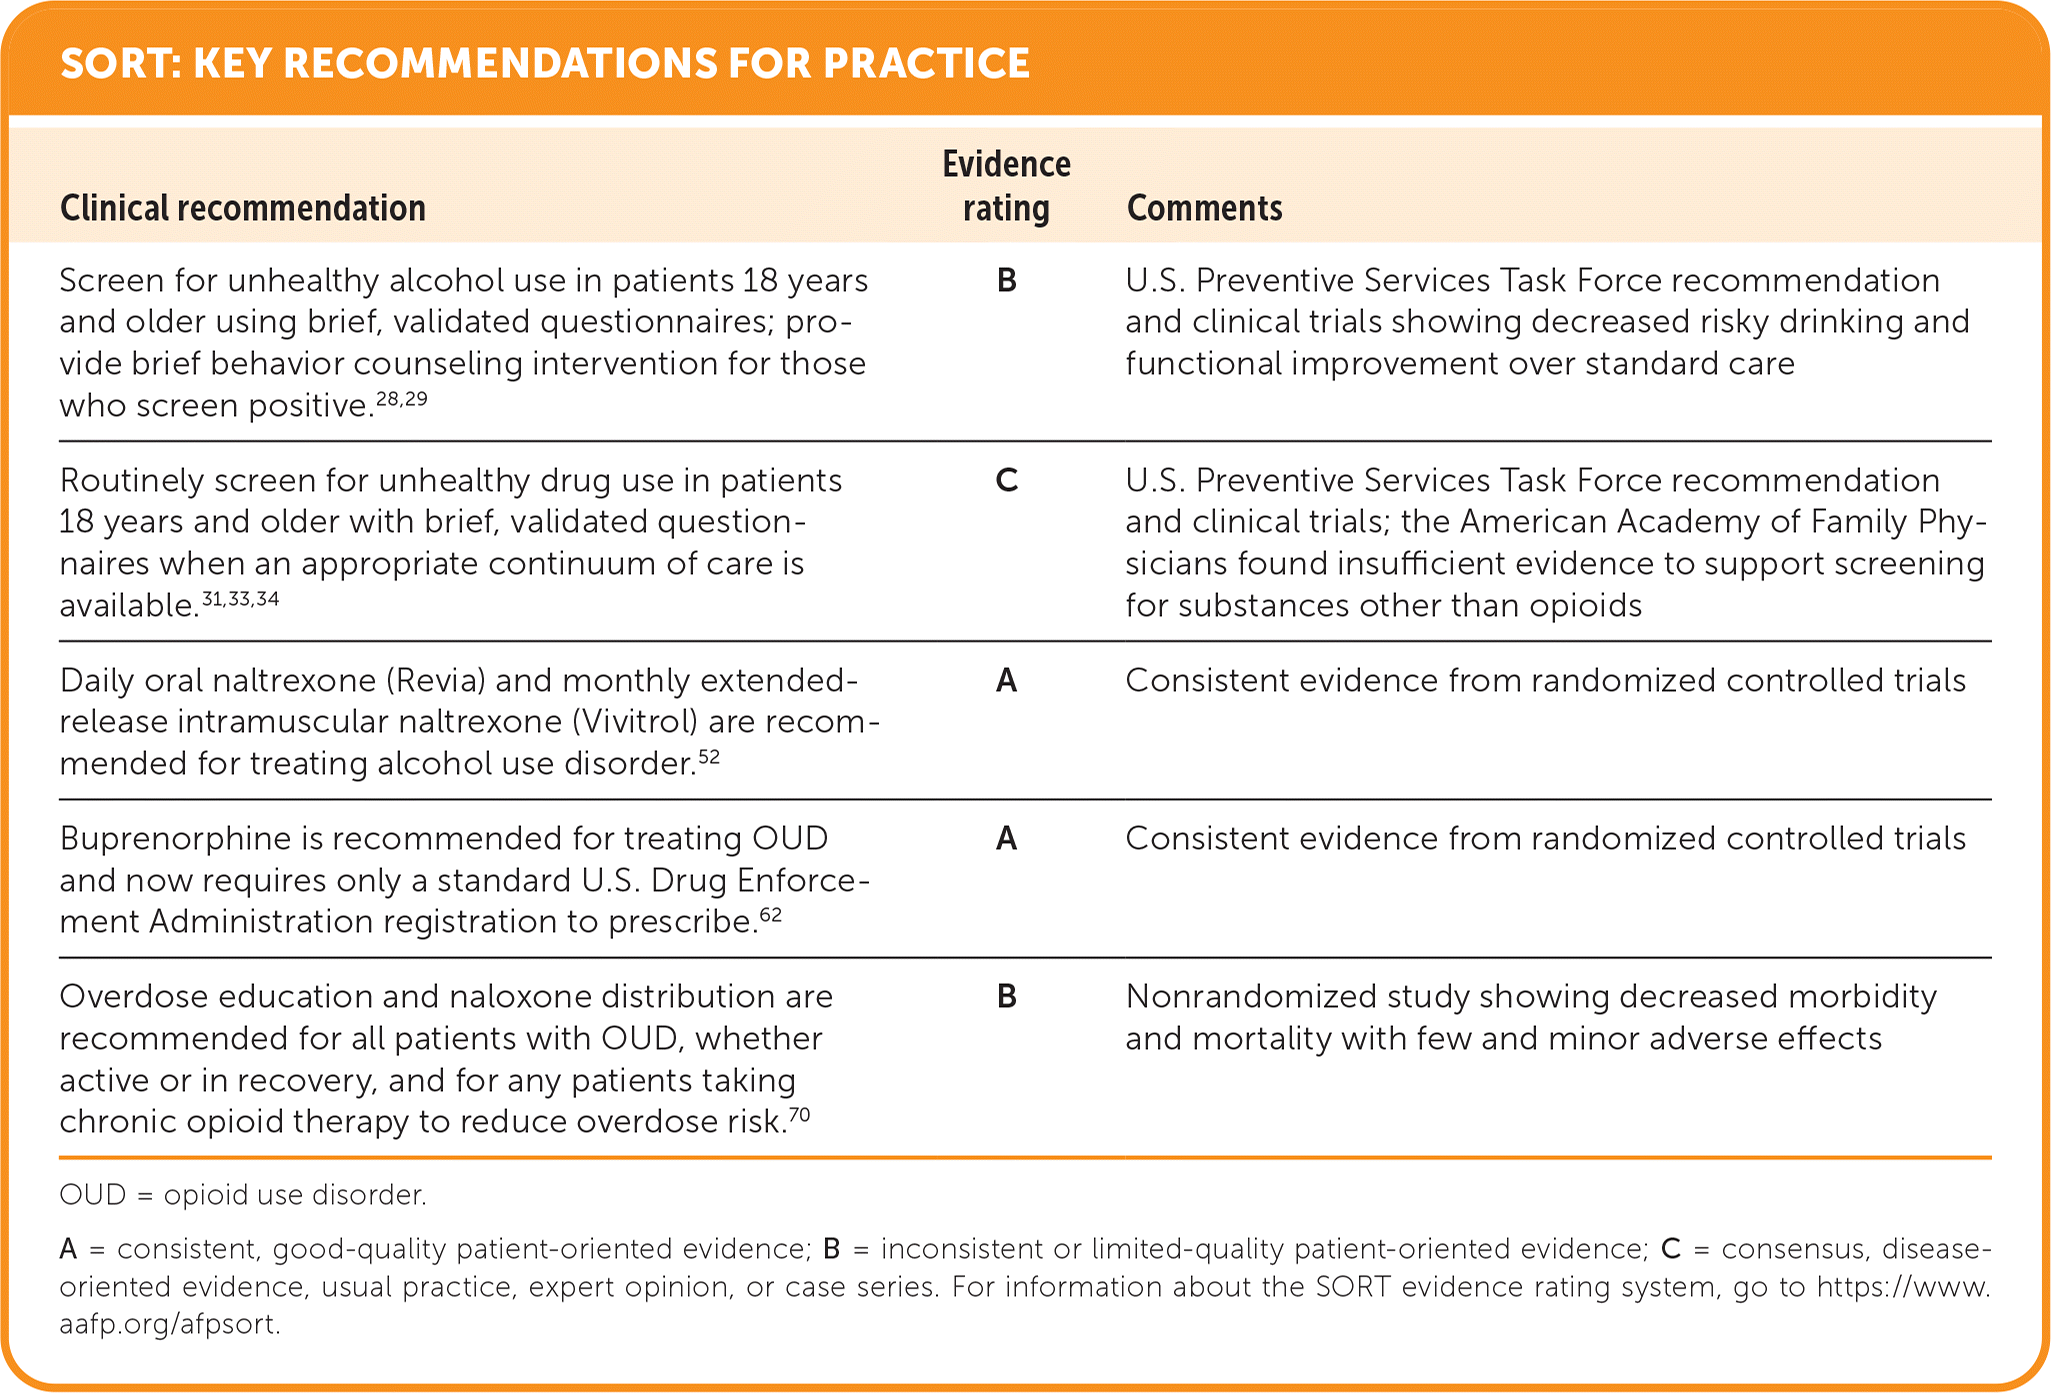
OUD = opioid use disorder.
A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.