

Key Points for Practice
• For acute or chronic pain not related to cancer, sickle cell disease, or end-of-life care, consider nonpharmacologic and nonopioid pharmacologic treatments before prescribing opioids.
• Other diagnoses and alternative treatments should be considered before initiating opioid therapy or continuing for more than 30 days.
• When discontinuing opioid therapy, a slow taper can minimize withdrawal symptoms. Slow tapers are often less than 10% of the daily dosage per month, especially after use for one year or more.
From the AFP Editors
Approximately 1 in 14 adults reported having pain that limited their life and work on most days during the past three months. Chronic pain impairs physical functioning, mental health, and quality of life. Nearly 1 in 10 people who commit suicide had evidence of chronic pain at the time of death.
Black, Hispanic, and Asian people are less likely to be assessed or treated for pain. White, American Indian, and Alaska Native people have a higher risk of prescription opioid–related overdose deaths; however, safeguards and monitoring are more often applied to Black patients.
The 2016 Centers for Disease Control and Prevention (CDC) opioid prescribing guidelines resulted in laws, regulations, and policies that were unintended and often exceeded the clinical recommendations by including cancer and palliative care, rapid opioid tapers, and rigid thresholds that limited the treatment of opioid use disorder and led to patient dismissal and abandonment by physicians. The CDC has released new recommendations for prescribing opioids.
Given the continued overuse of opioids to treat pain, the guidelines continue to suggest limiting their use in patients with acute or chronic pain. The guidelines do not apply to children or patients with sickle cell disease or cancer-related pain or who are receiving palliative or end-of-life care.
Alternatives to Opioids for Pain
Table 1 outlines nonpharmacologic therapies for acute and chronic pain.
TABLE 1. Nonpharmacologic Therapies for Pain
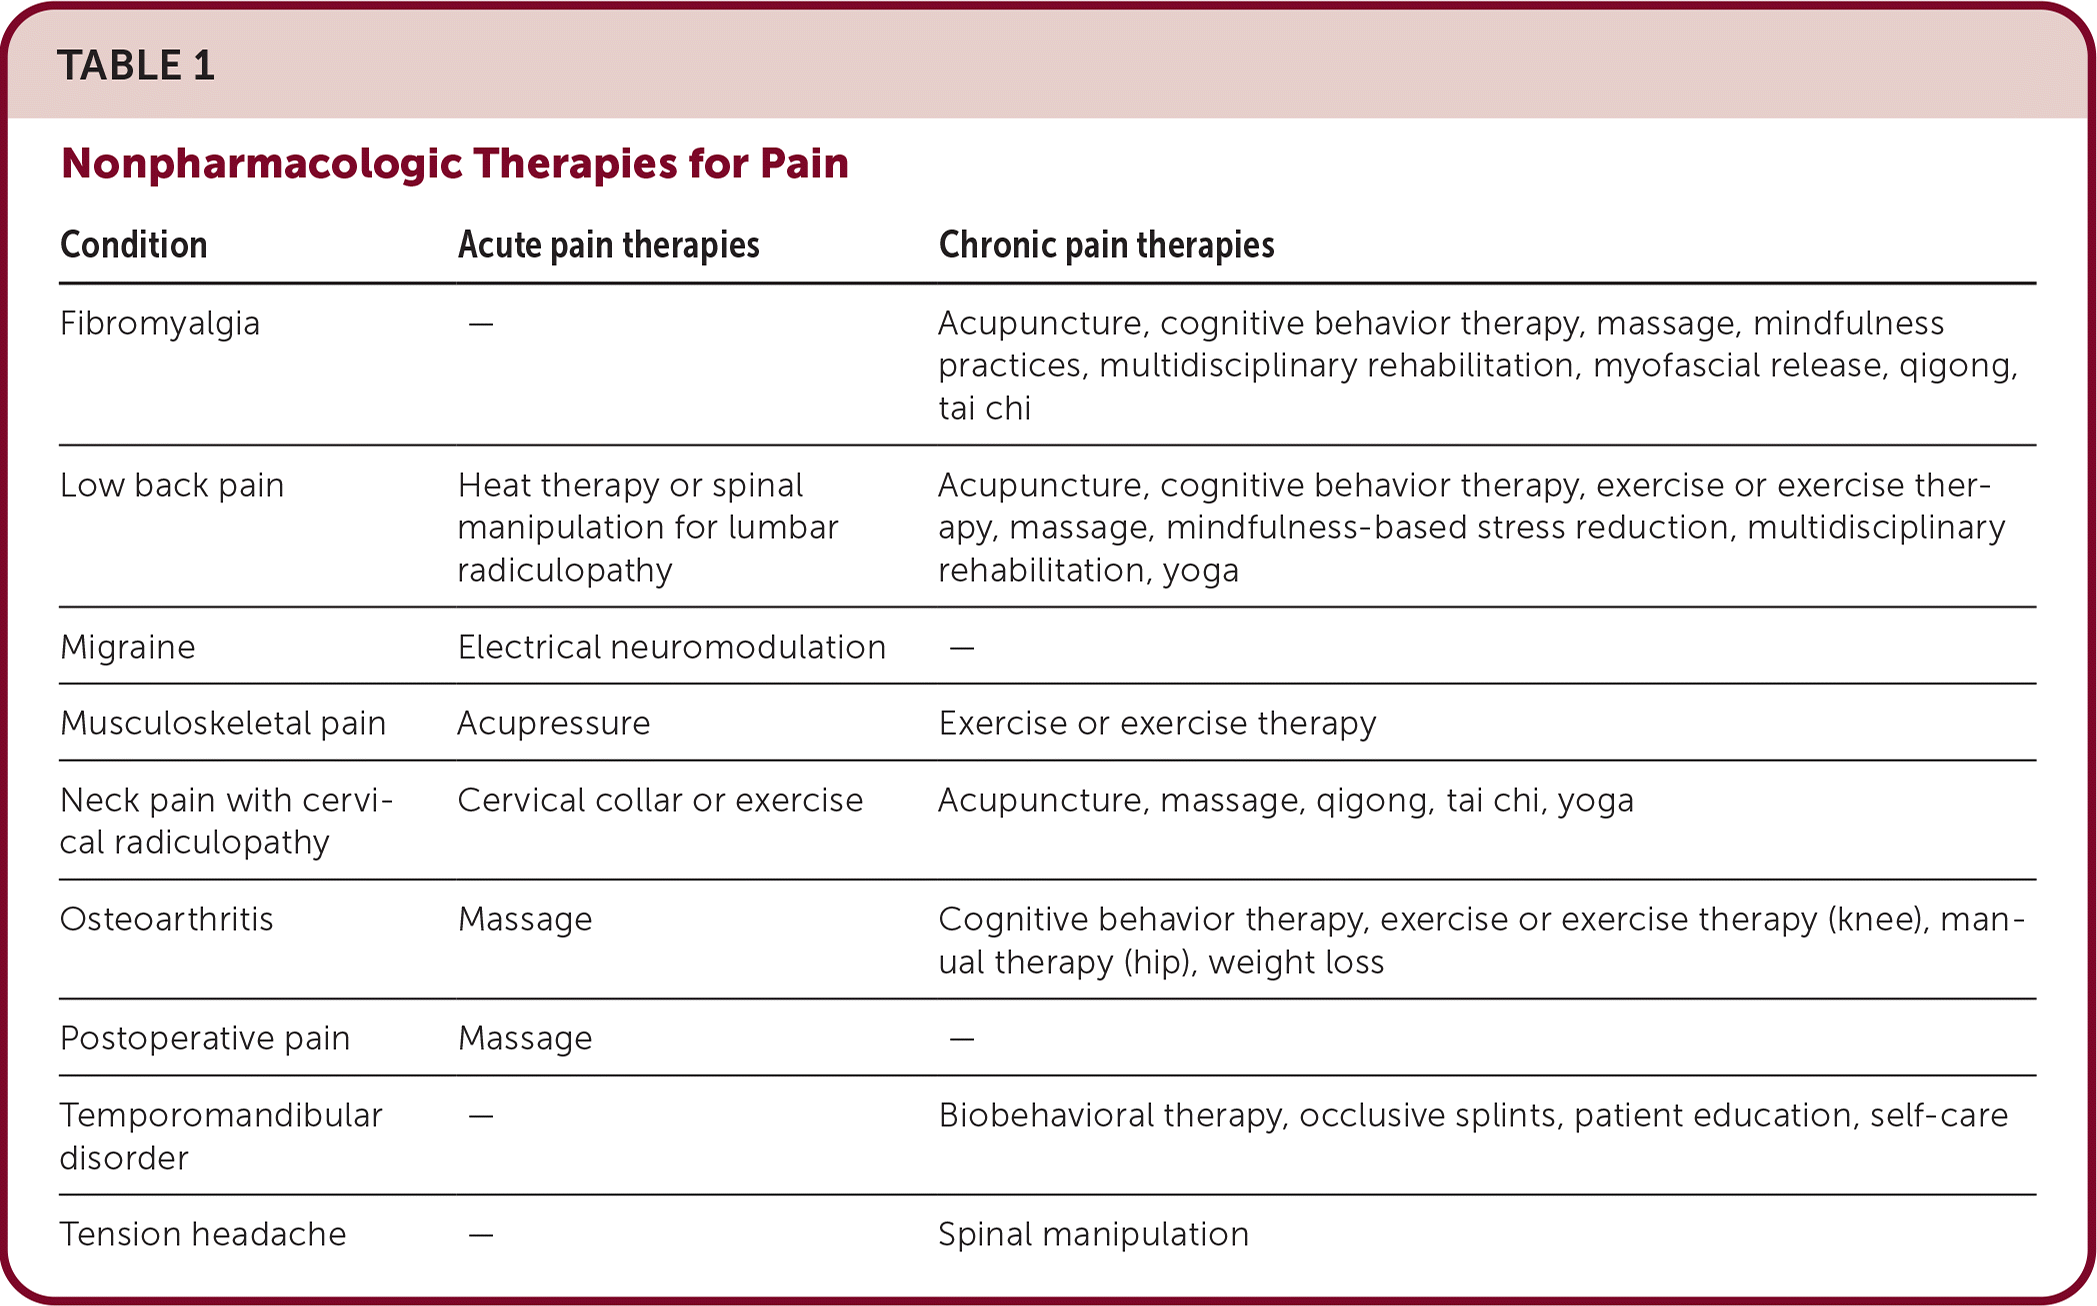
| Condition | Acute pain therapies | Chronic pain therapies |
|---|---|---|
| Fibromyalgia | — | Acupuncture, cognitive behavior therapy, massage, mindfulness practices, multidisciplinary rehabilitation, myofascial release, qigong, tai chi |
| Low back pain | Heat therapy or spinal manipulation for lumbar radiculopathy | Acupuncture, cognitive behavior therapy, exercise or exercise therapy, massage, mindfulness-based stress reduction, multidisciplinary rehabilitation, yoga |
| Migraine | Electrical neuromodulation | — |
| Musculoskeletal pain | Acupressure | Exercise or exercise therapy |
| Neck pain with cervical radiculopathy | Cervical collar or exercise | Acupuncture, massage, qigong, tai chi, yoga |
| Osteoarthritis | Massage | Cognitive behavior therapy, exercise or exercise therapy (knee), manual therapy (hip), weight loss |
| Postoperative pain | Massage | — |
| Temporomandibular disorder | — | Biobehavioral therapy, occlusive splints, patient education, self-care |
| Tension headache | — | Spinal manipulation |
ACUTE PAIN
Multiple nonpharmacologic therapies and modalities can be used to relieve acute pain. These approaches can be used alone or in addition to nonopioid medications. Some treatments are not covered by medical insurance programs, and the CDC encourages health insurers to provide or increase payment for these therapies.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
