
Already a member or subscriber? Sign in now

Five Trauma-Informed Communication Strategies to Improve Patient Interactions

RACHEL FIORE, PhD, CCC-SLP
PETER DEBLIEUX, MD
SANDY HYATT, PsyD

FPM. 2025;32(3):21-25.

Author disclosures: no relevant financial relationships.

These evidence-based strategies can help you understand your patients' context so you can better care for and empower them.

Primary care is a demanding field, requiring a high cognitive load due to complex patient histories, broad differential diagnoses, multiple treatment options, expanding medication lists, and a variety of team members. Physicians are tasked with managing all of these variables while also communicating well with patients to create a detailed picture of their health.

However, research has consistently found gaps in patient comprehension of even basic components of their visits,1 and patients often express that their physician does not fully understand their concerns or undervalues their perspective.2 Overcoming these barriers is crucial, as improved communication enhances not only the exchange of information but also the therapeutic relationship.3,4

THE IMPORTANCE OF EFFECTIVE COMMUNICATION
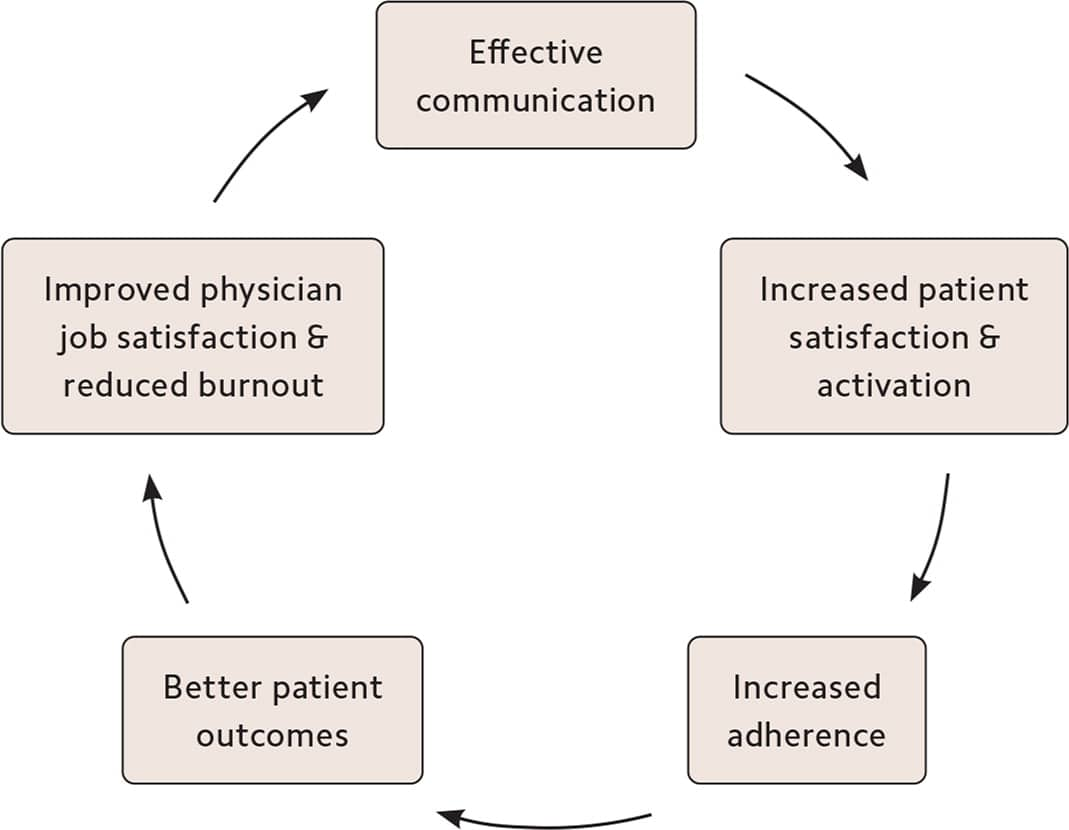
Effective communication often requires a trauma-informed mindset, given that roughly half of primary care patients have undergone some form of trauma.5 This means approaching each patient with empathy and curiosity about “What happened to you?” rather than “What is wrong with you?”

This article presents five communication strategies that can help create psychological safety, build trust, and facilitate better patient interactions, particularly with individuals who have experienced trauma.

KEY POINTS

  • Clear and effective communication improves patient satisfaction, treatment adherence, and health outcomes.
  • Effective communication often requires a trauma-informed mindset; this involves approaching patients with empathy and curiosity about their experiences and creating psychological safety.
  • Evidence-based communication strategies include perspective-taking, emotional attunement, patient activation, shared decision-making, and teach-back.

PERSPECTIVE-TAKING

When patients enter the examination room, they bring with them their own unique background, including race, gender, profession, spirituality, fears, biases about the health care system, lived experiences, and their community's opinions. The simple practice of imagining yourself as the patient, looking at the situation through the patient's eyes, can increase patient satisfaction6 and help combat bias.7 It can also benefit physicians, protecting against burnout by reducing clinical monotony, increasing pro-social helping behaviors, and supporting their emotional balance.8

To use perspective-taking in a patient encounter, take a moment before you step into the exam room and imagine that you are the patient. Consider their potential experiences, biases, fears, and hopes. Perhaps they are feeling skeptical, tired, in pain, or overwhelmed while having to interact with a physician they may perceive as intimidating, naive, dismissive, or even adversarial. Enter with a sense of curiosity and flexibility, and invite the patient to help you understand their perspective.

Dr. Fiore is director of the Standardized Patient Project, Louisiana State University Health Sciences Center (LSUHSC), New Orleans.

Dr. DeBlieux is assistant dean for advanced learning and simulation, LSUHSC.

Dr. Hyatt is an assistant professor of clinical psychiatry, LSU School of Medicine.

Send comments to fpmedit@aafp.org, or add your comments to the article online.

Author disclosures: no relevant financial relationships.

  1. 1.Pietrzykowski T, Smilowska K. The reality of informed consent: empirical studies on patient comprehension — systematic review. Trials. 2021;22:1-8.
  2. 2.Greene J, Ramos C. A mixed methods examination of health care provider behaviors that build patients’ trust. Patient Educ Couns. 2021;104(5):1222-1228.
  3. 3.Ward P. Trust and communication in a doctor-patient relationship: a literature review. Arch Med. 2018;3(3):36.
  4. 4.Riedl D, Schüßler G. The influence of doctor-patient communication on health outcomes: a systematic review. J Psychosom Med Psychother. 2017;63(2):131-150.
  5. 5.Blatt B, LeLacheur SF, Galinsky AD, Simmens SJ, Greenberg L. Does perspective-taking increase patient satisfaction in medical encounters? Acad Med. 2010;85(9):1445-1452.
  6. 6.Drwecki BB, Moore CF, Ward SE, Prkachin KM. Reducing racial disparities in pain treatment: the role of empathy and perspective-taking. Pain. 2011;152(5):1001-1006.
  7. 7.Lamothe M, Boujut E, Zenasni F, Sultan S. To be or not to be empathic: the combined role of empathic concern and perspective taking in understanding burnout in general practice. BMC Fam Pract. 2014;15:1-7.
  8. 8.Forkey H, Szilagyi M, Kelly ET, Duffee J. Trauma-informed care. Pediatrics. 2021;148(2):e2021052580.
  9. 9.Scott-Fordsmand H. Evaluating emotions in medical practice: a critical examination of “clinical detachment” and emotional attunement in orthopaedic surgery. Med Health Care Philos. 2022;25(3):413-428.
  10. 10.Hibbard JH, Stockard J, Mahoney ER, Tusler M. Development of the Patient Activation Measure (PAM): conceptualizing and measuring activation in patients and consumers. Health Serv Res. 2004;39(4):1005-1026.
  11. 11.Becker ER, Roblin DW. Translating primary care practice climate into patient activation: the role of patient trust in physician. Med Care. 2008;46(8):795-805.
  12. 12.Alvarez C, Greene J, Hibbard J, Overton V. The role of primary care providers in patient activation and engagement in self-management: a cross-sectional analysis. BMC Health Serv Res. 2016;16:1-8.
  13. 13.Joosten EAG, DeFuentes-Merillas L, De Weert GH, Sensky T, Van Der Staak CPF, de Jong CAJ. Systematic review of the effects of shared decision-making on patient satisfaction, treatment adherence and health status. Psychother Psychosom. 2008;77(4):219-226.
  14. 14.The SHARE Approach — Essential Steps of Shared Decision Making: Expanded Reference Guide With Sample Conversation Starters. Agency for Healthcare Research and Quality. Updated September 2020. Accessed March 20, 2025. https://www.ahrq.gov/health-literacy/professional-training/shared-decision/tool/resource-2.html
  15. 15.Talevski J, Wong Shee A, Rasmussen B, Kemp G, Beauchamp A. Teachfpm20250500p21-back: a systematic review of implementation and impacts. PLoS One. 2020;15(4):e0231350.

Copyright © 2026 by the American Academy of Family Physicians.

This content is owned by the AAFP. A person viewing it online may make one printout of the material and may use that printout only for his or her personal, non-commercial reference. This material may not otherwise be downloaded, copied, printed, stored, transmitted or reproduced in any medium, whether now known or later invented, except as authorized in writing by the AAFP. See permissions for copyright questions and/or permission requests.
