

The use of patient risk scores allows for more targeted interventions, equitable panel sizes, and efficient resource allocation.

To deliver on the promise of high-quality, value-based care for our patients in the context of workforce shortages and an aging population, risk stratification is essential. It involves systematically categorizing patients by risk level based on their health status and other factors.1–3 This allows for more targeted interventions, equitable panel sizes, efficient resource allocation, and a proactive, population-based approach to care.4,5
The Military Health System (MHS) has been exploring risk stratification for many years as a way to encourage more appropriate care delivery and reduce “low-value care.”6,7 Based on the MHS’ recent implementation of risk stratification in primary care, this article describes risk scoring options, use cases, and lessons learned.
KEY POINTS
- Risk stratification is essential to delivering value-based care, enabling targeted interventions and efficient resource allocation.
- Adjusting panel sizes based on patient acuity allows clinicians to achieve target capacity while getting credit for the complexity of their patient needs.
- Clinics should explore various risk-score methodologies and select the one that best fits their needs.
RISK SCORING METHODS
Risk stratification is based on a qualitative or quantitative “risk score.” Multiple methodologies exist for calculating this score.
FPM previously published a methodology based on gender and age.8 Perhaps the best known and most widely used methodology is the Johns Hopkins Adjusted Clinical Group (ACG) System, which offers an array of outputs (including numeric scores, resource utilization bands, and patient need groups) and inputs (including utilization patterns, social determinants of health, and medications). It has been used successfully in a variety of settings.9 Other methodologies use a qualitative score, sometimes called a “worry score,” which clinical staff assign based on their knowledge of the patient. This approach has proven beneficial in the prediction of decompensation in the inpatient setting.10 Some health systems have developed their own methodology, such as the University of California-San Francisco’s risk score for the purpose of panel weighting.11
The MHS has used several risk-scoring methodologies over the years, including the ACG System, the Illness Burden Index (IBI, an offshoot of the ACG), and a proprietary system called the Health Risk Score (HRS). The HRS uses regression analysis on cost and claims data to identify weights for diagnoses. Weights are cumulative in patients with multiple diagnoses and represent the proportionate resources needed to care for them. For example, a healthy patient with no chronic conditions might have a risk score of 0 or 0.5, while a patient with several chronic conditions might have a risk score of 6 or more.
Three years ago, the MHS sought to reimagine primary care delivery based on the principles of value-based care, and the first step was to determine which of these risk-scoring methodologies we would use. We compared de-identified risk scores for all three methods using three years of data representing more than 3.2 million TRICARE Prime patients enrolled in military treatment facilities. We found no statistically significant difference in primary care utilization between the scoring methods, although all three methods did show a positive correlation. In other words, higher risk scores were associated with greater utilization. Demographic variables did not affect these results.
With no quantitative difference to promote one methodology over the others, we looked at qualitative factors. At the time, the ACG and IBI undervalued complex disease in childhood. The HRS factored in higher values for children (because of childhood disease and increased appointment demand due to well-child examinations) and for active-duty service members (because of military medical requirements). Additionally, we were already using the HRS to drive primary care sub-capitation rates. Thus, we chose the HRS methodology.
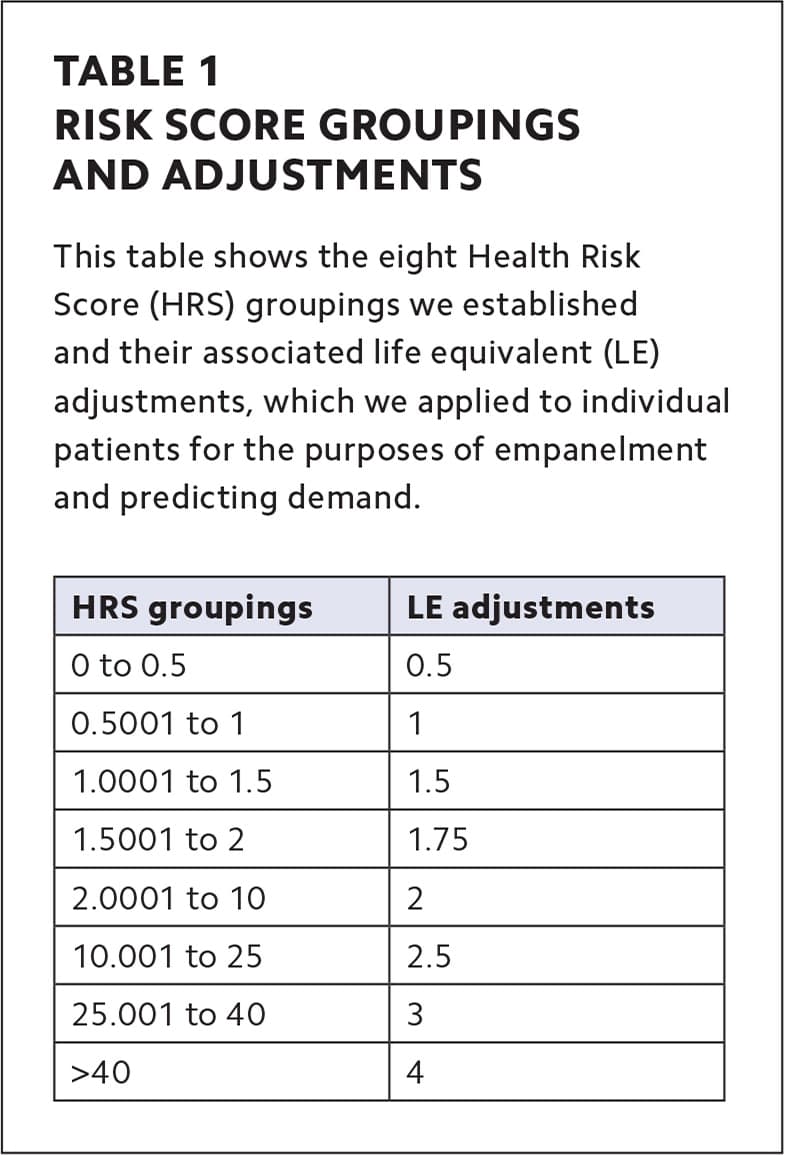
To operationalize the HRS, we calculated the average primary care utilization rate for each HRS score and identified eight distinct groupings. For example, at the lowest level, patients with risk scores of 0 to 0.5 were grouped together because they had similar primary care utilization rates; at the highest level, patients with risk scores above 40 were grouped together because they had similar primary care utilization rates. (See all eight groupings in Table 1.)
Risk Score Groupings and Adjustments
| HRS groupings | LE adjustments |
|---|---|
| 0 to 0.5 | 0.5 |
| 0.5001 to 1 | 1 |
| 1.0001 to 1.5 | 1.5 |
| 1.5001 to 2 | 1.75 |
| 2.0001 to 10 | 2 |
| 10.001 to 25 | 2.5 |
| 25.001 to 40 | 3 |
| >40 | 4 |
THREE USE CASES
The following cases, based on the MHS experience, illustrate how risk stratification can be used in primary care.
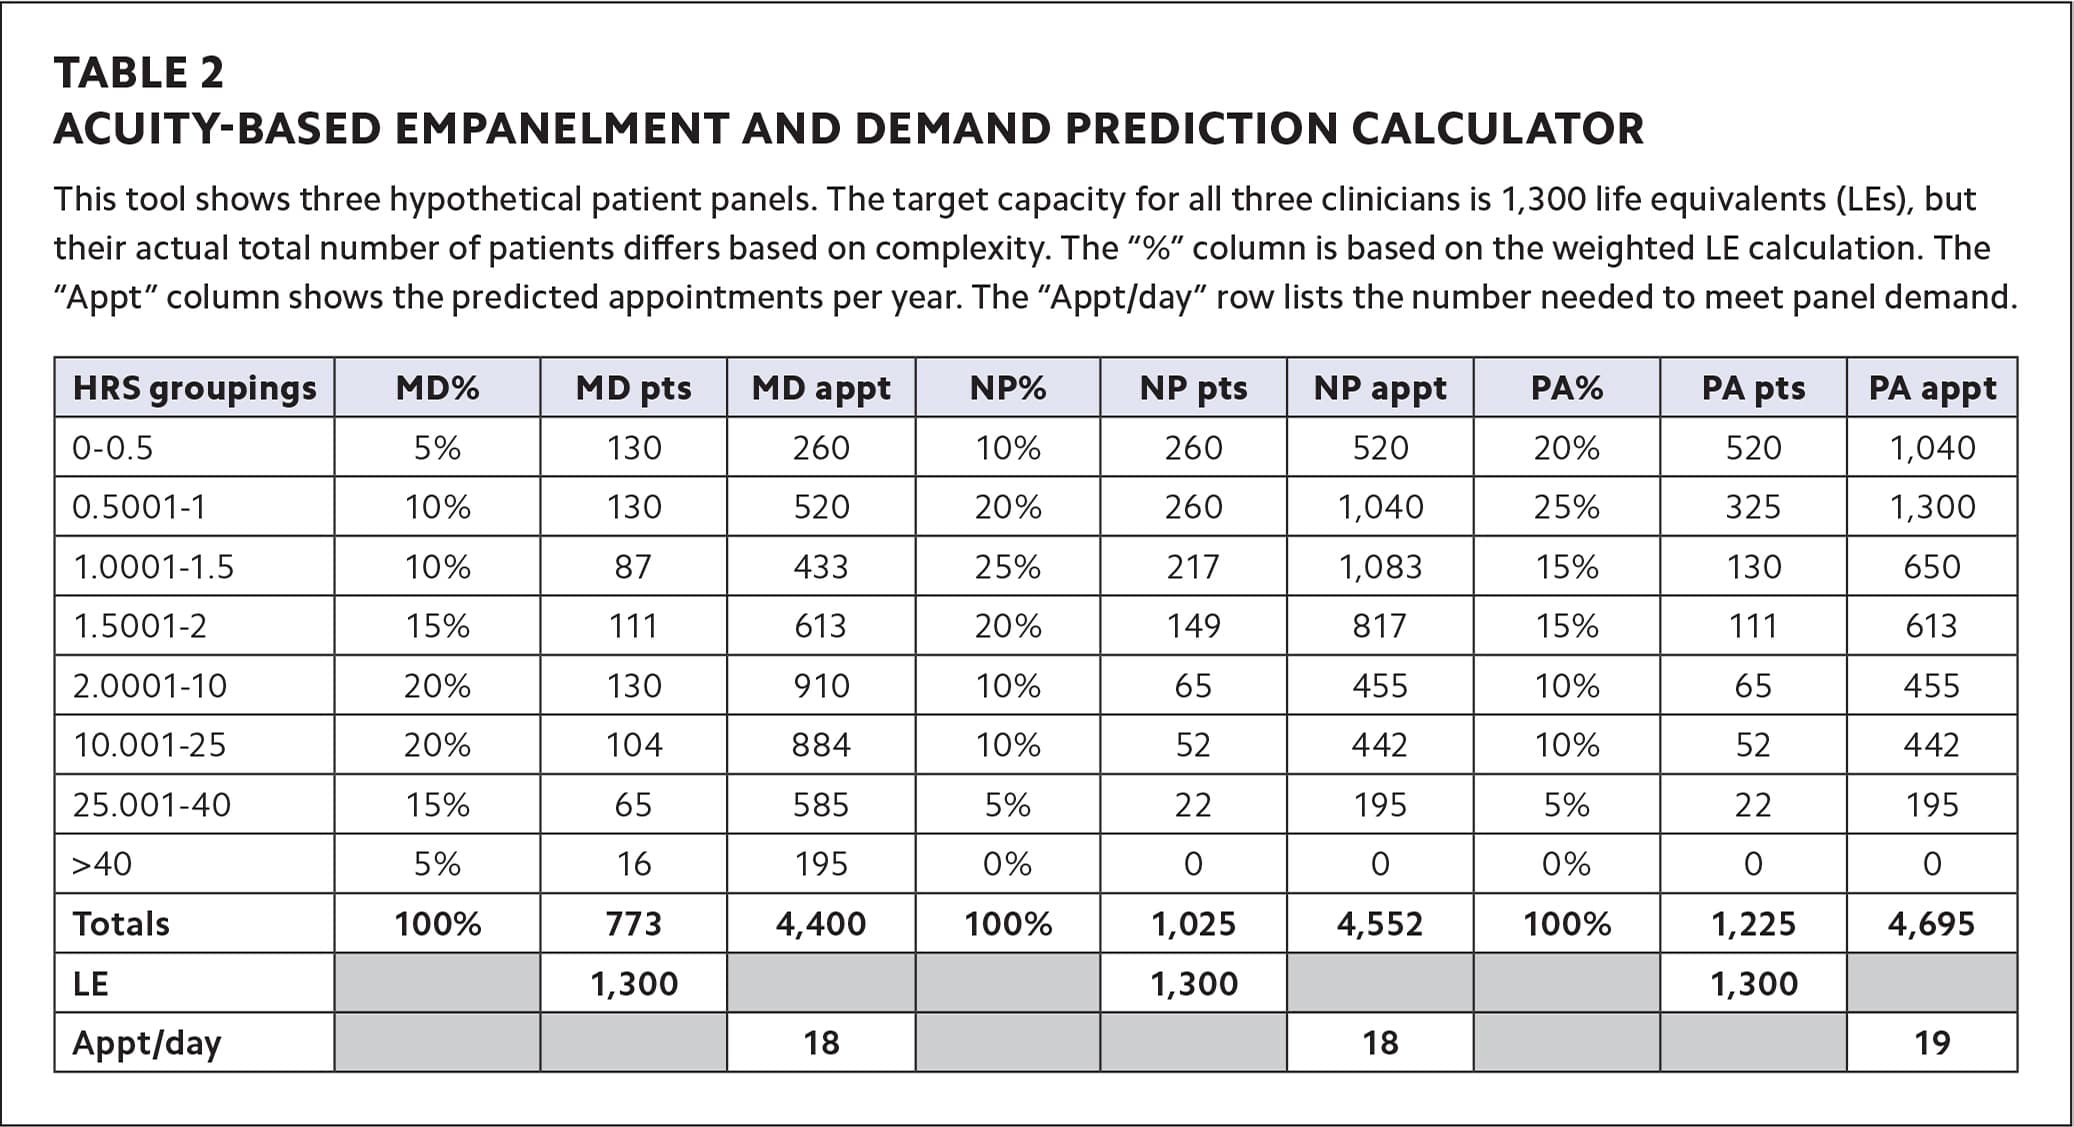
Use case #1: Adjusting clinicians’ panels based on patient acuity. Although no two patients are the same, patients historically have been placed on primary care clinicians’ panels as equals, with no consideration for their complexity or demand for resources. The MHS had done some panel weighting in the past using the IBI for internal medicine; however, using the HRS for panel weighting across primary care begat a new approach. For each of our eight HRS groupings, mentioned above, we calculated the average primary care utilization (visits per year) for the prior 12 months. We then compared these rates to the MHS norm of four visits per year and determined a multiplication factor to represent the relative demand of patients in each grouping. We termed these multiplication factors “life equivalents” (LEs). For example, at the lowest level, patients with risk scores of 0 to 0.5 had a 0.5 LE adjustment; at the highest level, patients with risk scores above 40 had a 4.0 LE adjustment. (See Table 1.) We applied the LE adjustment to each patient within each HRS grouping on a clinician’s panel, thus generating a weighted panel size. (See Table 2.)
The LE adjustment allowed us to assign one panel capacity target (1,300 LEs) to each primary care clinician regardless of specialty and to adjust each clinician’s actual number of patients up or down based on complexity. Thus, we were able to design panels specific to individual clinicians, practices, locations, or other desired factors. We created an empanelment calculator (Table 2) that allowed us to see how various panel adjustments would affect the capacity target. We found this especially useful when we needed to rapidly redistribute patients following a clinician’s deployment or departure from clinic. Using acuity-based empanelment, we could ensure that no one took on an overly complex set of patients as they were redistributed.
ACUITY-BASED EMPANELMENT AND DEMAND PREDICTION CALCULATOR
| HRS groupings | MD% | MD pts | MD appt | NP% | NP pts | NP appt | PA% | PA pts | PA appt |
|---|---|---|---|---|---|---|---|---|---|
| 0–0.5 | 5% | 130 | 260 | 10% | 260 | 520 | 20% | 520 | 1,040 |
| 0.5001–1 | 10% | 130 | 520 | 20% | 260 | 1,040 | 25% | 325 | 1,300 |
| 1.0001–1.5 | 10% | 87 | 433 | 25% | 217 | 1,083 | 15% | 130 | 650 |
| 1.5001–2 | 15% | 111 | 613 | 20% | 149 | 817 | 15% | 111 | 613 |
| 2.0001–10 | 20% | 130 | 910 | 10% | 65 | 455 | 10% | 65 | 455 |
| 10.001–25 | 20% | 104 | 884 | 10% | 52 | 442 | 10% | 52 | 442 |
| 25.001–40 | 15% | 65 | 585 | 5% | 22 | 195 | 5% | 22 | 195 |
| >40 | 5% | 16 | 195 | 0% | 0 | 0 | 0% | 0 | 0 |
| Totals | 100% | 773 | 4,400 | 100% | 1,025 | 4,552 | 100% | 1,225 | 4,695 |
| LE | 1,300 | 1,300 | 1,300 | ||||||
| Appt/day | 18 | 18 | 19 |
Use case #2: Predicting primary care demand. Having the eight HRS groupings and knowing the average primary care utilization rates of each allowed us to begin to predict primary care demand. Using this data, we added a column to the acuity-based empanelment calculator (Table 2) to capture the total number of appointments expected per year for a clinician’s empaneled patients in each HRS grouping. From the annual total, we could then calculate how many appointments the clinician needed to provide on average per workday to meet the demand of their panel. Additionally, a multivariate regression analysis showed that, independent of demographic variables, a one-point increase in a patient’s HRS led to an additional 0.5 primary care encounters per year. This helped further solidify our confidence in using the HRS to predict primary care demand.
At the individual patient level, knowing their risk score allows for more effective and proactive management, which can help drive down utilization and cost of care. One challenge we faced was getting the patient’s risk score imported into the electronic health record (EHR) from another data source so teams could see it. Once we resolved that technical issue, team members could identify better strategies for secondary and tertiary prevention because they knew the complexity of the patient, understood the patient population, and had the ability to target subgroups.
Use case #3: Adjusting staffing and resources to meet population needs. During our initial investigation of the HRS and development of LEs based on average primary care utilization, we noticed a pattern. Nearly 58% of our patient population fell into the lowest HRS group, which had an average primary care demand of fewer than two appointments per year (see Figure 1). At the same time, our primary care clinics were staffed to provide numerous ancillary services such as embedded behavioral health care, clinical pharmacy services, and nurse case management — costly services that more than half of our population did not require. In light of this data, we developed a hybrid model for primary care delivery. Under the model, patients falling into the lowest HRS grouping were cared for in an acute care setting with a heavier focus on primary prevention. These clinics were leaner in terms of staffing and operated with more availability for same-day care and virtual care. Patients in the remaining seven HRS groups were cared for in a traditional “patient-centered medical home” (PCMH) setting that included the ancillary service staffing. Applying this model to a hypothetical group of 10,000 patients, we estimated that we would need 22 fewer staff members to operate both the acute care and PCMH clinics. This illustrates how population management can help clinics better estimate needed resources and potentially bring about significant financial relief.
FIGURE 1. PERCENTAGE OF TOTAL ENROLLMENT BY RISK SCORE GROUPING
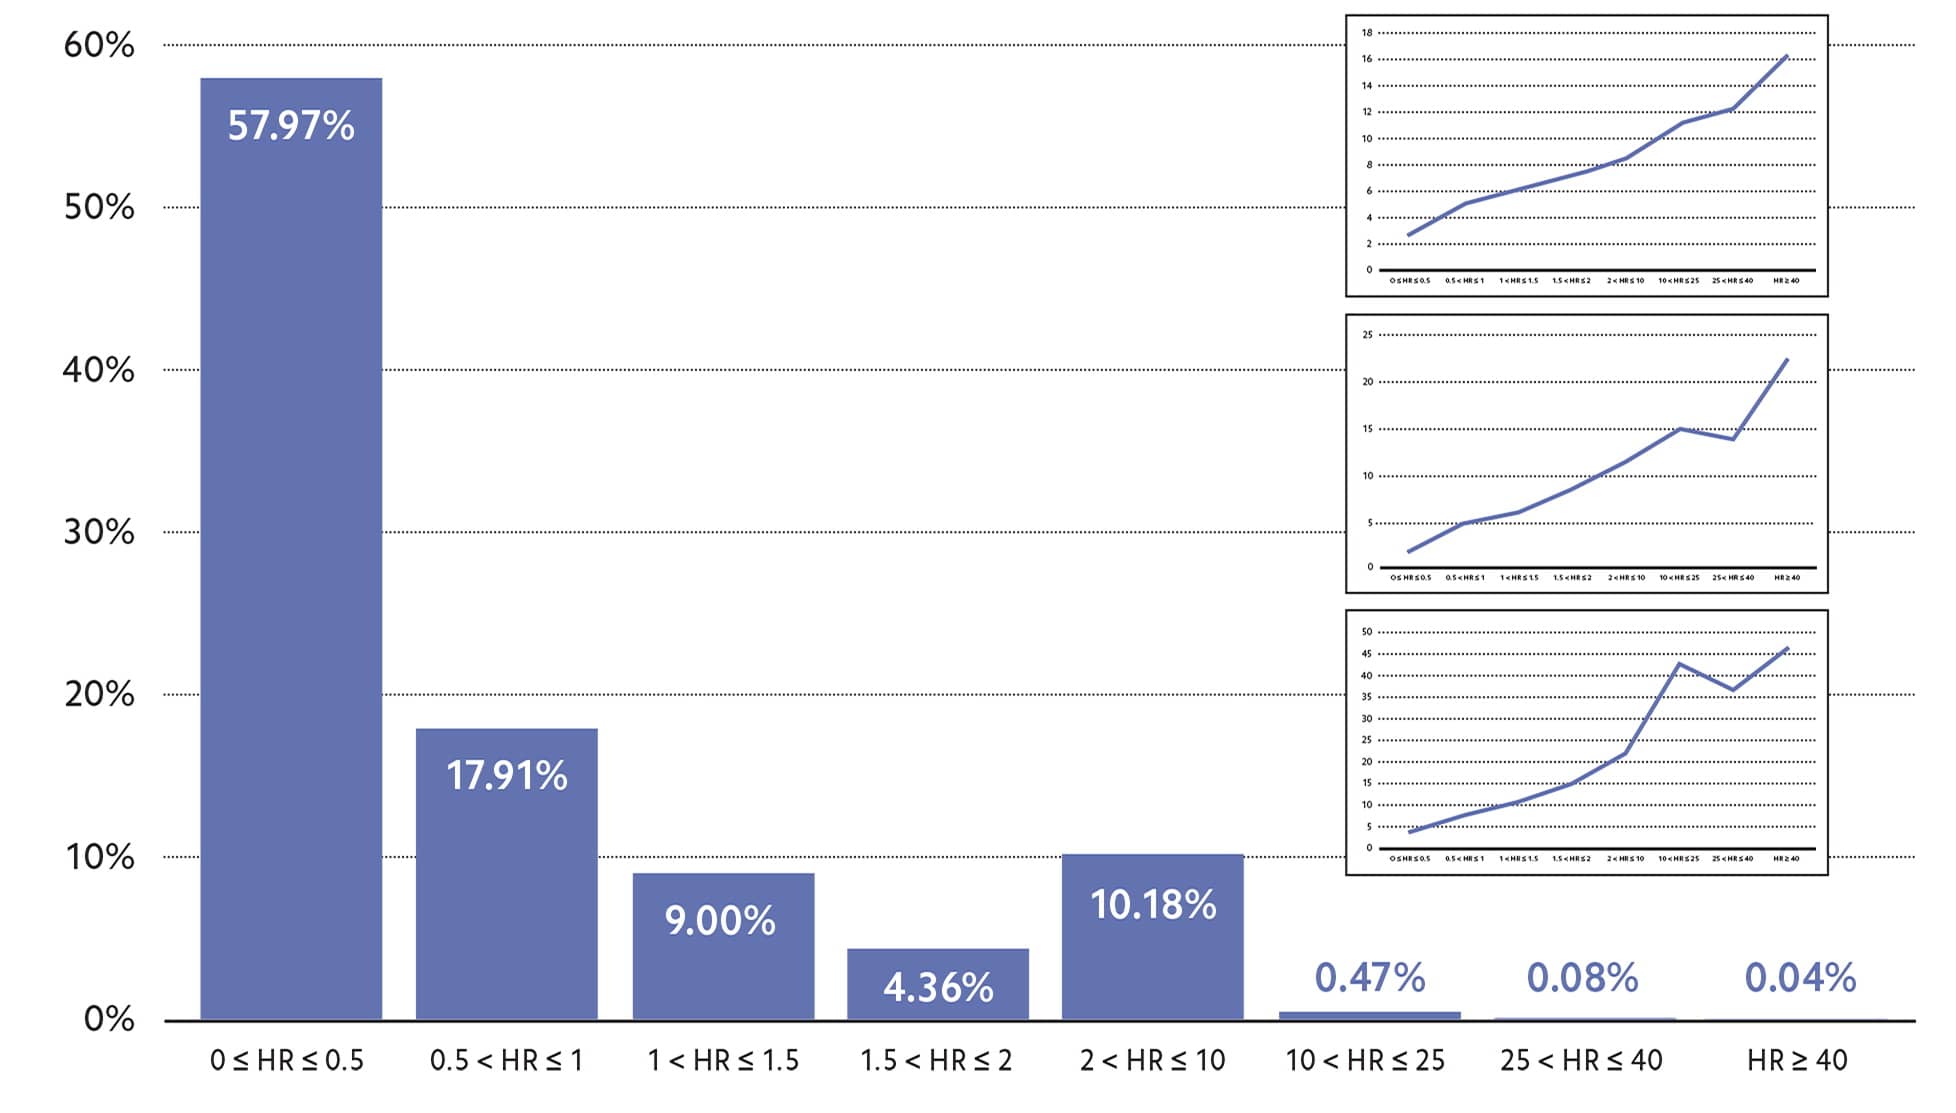
The large graph shows the distribution of our population by Health Risk Score grouping. More than half fall into the low-acuity group.
The smaller graphs show that higher risk scores correlate with higher utilization of primary care (top), specialty care (middle), and prescriptions (bottom).
LESSONS LEARNED
While this work was conducted in the MHS and based on its proprietary risk score methodology, physicians in other settings can apply the basic principles:
- Use of a risk scoring methodology is essential to providing personalized care that delivers on value,
- Each health system should evaluate the options for risk scoring methodologies and select the one that best fits their needs (use cases) for population health management,
- Clinics should reassess patient risk scores on a regular cadence as they will likely change over time,3
- Risk scores should be visible to your team in the EHR,3
- Acuity-based empanelment allows clinics to customize panels to achieve a target capacity and ensures clinicians get credit for the complexity of their patients’ needs,
- Using risk scores in combination with utilization rates can help clinics predict the demand of their patient population, ensure personalized, patient-centered access and care, and deploy appropriate resources.
While each health system’s primary care transformation journey will be unique, the MHS experience illustrates the power of risk scoring on the road to value-based primary care.
