

Chronic kidney disease (CKD) affects approximately 15% of the U.S. population, and many people are unaware of their diagnosis. Screening may be considered for patients with cardiovascular disease, diabetes mellitus, hypertension, age 60 years and older, family history of kidney disease, previous acute kidney injury, or preeclampsia. Diagnosis and staging of CKD are based on estimated glomerular filtration rate (eGFR), excessive urinary albumin excretion, or evidence of kidney parenchymal damage lasting more than three months. eGFR should be determined using the CKD-EPI creatinine equation without the race variable. Risk calculators are available to estimate the risk of progression to end-stage renal disease. When possible, serum cystatin C should be measured to confirm eGFR in patients with CKD. Blood pressure should be maintained at less than 140/90 mm Hg, with a systolic blood pressure target of 120 mm Hg or less for patients tolerant of therapy, using an angiotensin-converting enzyme inhibitor or angiotensin receptor blocker. Sodium-glucose cotransporter-2 inhibitors and metformin should be considered in patients with CKD and type 2 diabetes who have not reached their glycemic goal. Intravenous iodinated contrast media temporarily reduces eGFR and should be avoided in patients with advanced CKD. Interdisciplinary management of patients with CKD is important for reducing morbidity and mortality, and patients at high risk of progression to end-stage renal disease should be referred to a nephrologist.
Chronic kidney disease (CKD) affects about 15% of the U.S. population; however, 9 out of 10 people do not know they have impaired renal function.1 CKD is diagnosed in Black people three times as often as in White people.1,2 CKD is more common in women than men, but men are more likely to progress to end-stage renal disease (ESRD).1,2 CKD is more common in patients 60 years and older compared with younger patients, and more advanced disease is associated with an increased risk of cardiovascular disease and death.1,3
SORT: KEY RECOMMENDATIONS FOR PRACTICE
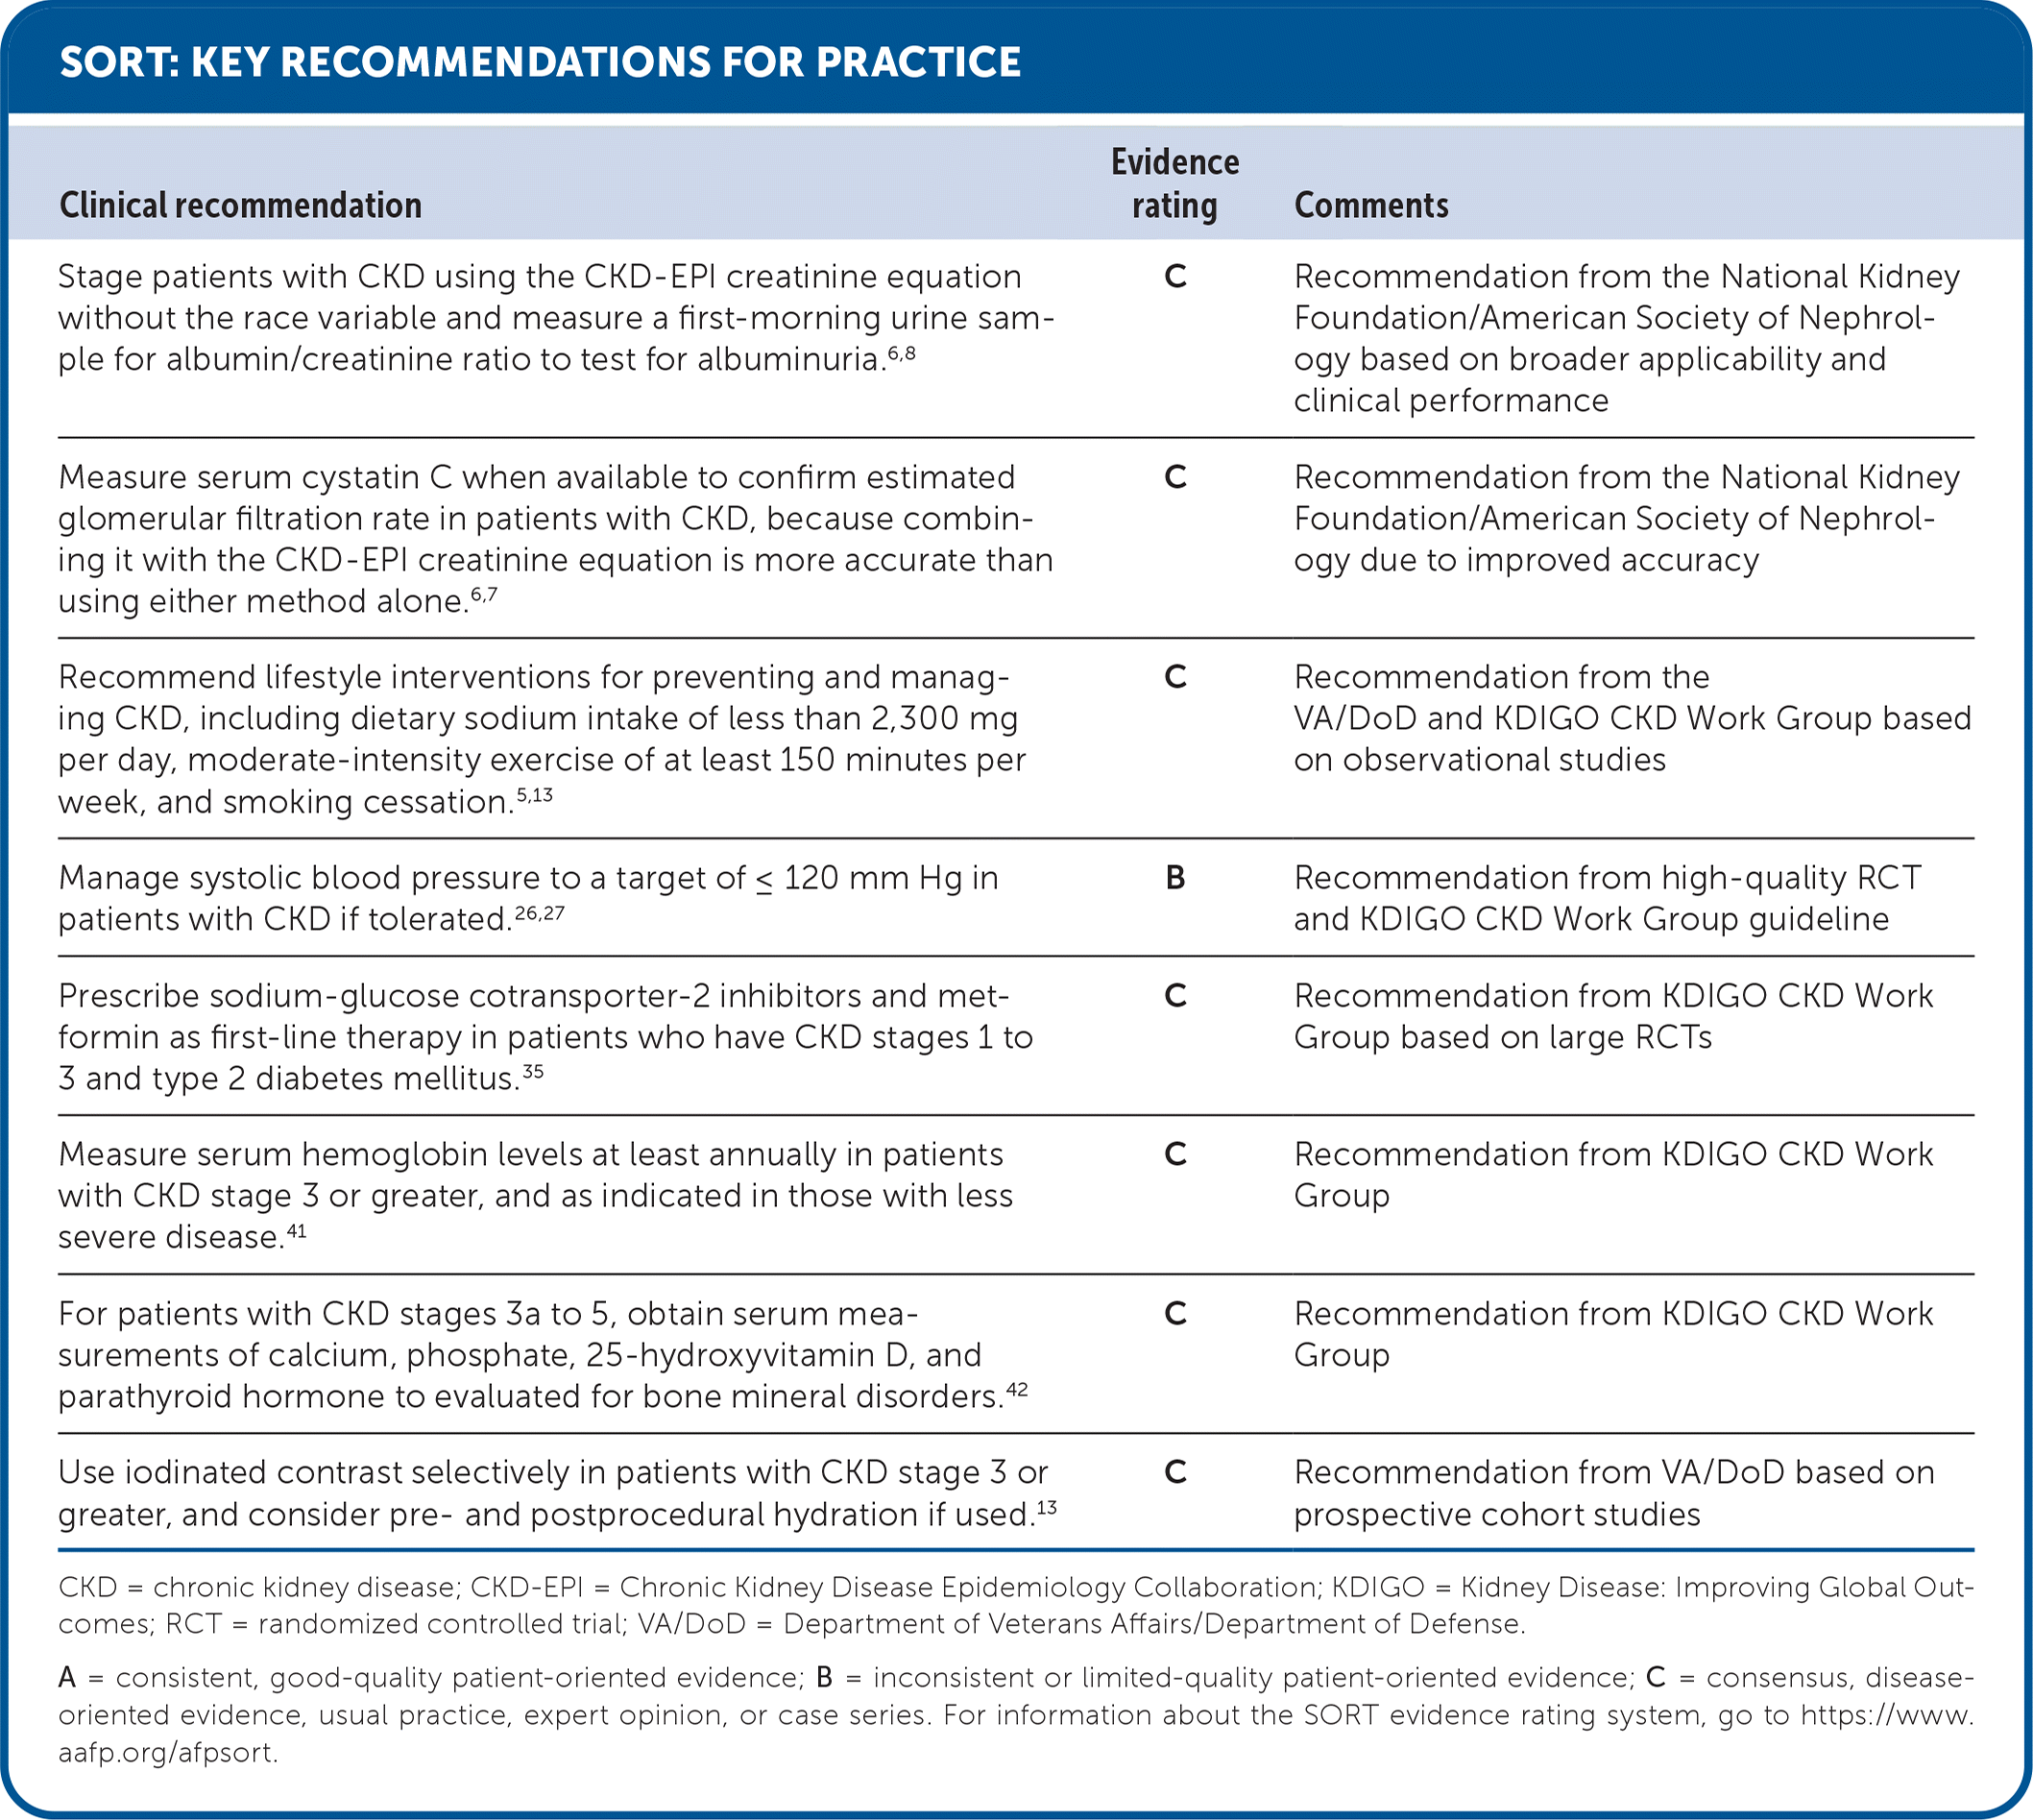
CKD = chronic kidney disease; CKD-EPI = Chronic Kidney Disease Epidemiology Collaboration; KDIGO = Kidney Disease: Improving Global Outcomes; RCT = randomized controlled trial; VA/DoD = Department of Veterans Affairs/Department of Defense.
A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
