

Hip and knee injections are useful diagnostic and therapeutic tools for family physicians. This article reviews anatomic landmark–guided and ultrasound-guided injections and aspiration techniques for greater trochanteric pain syndrome, the hip joint, the knee joint, the pes anserine bursa, and the iliotibial band. Indications for injections include acute and chronic inflammatory conditions, such as rheumatoid arthritis; osteoarthritis; overuse; and traumas. Joint aspirations may be performed to aid in the diagnosis of unexplained effusions and to relieve pain. Technique, injectant, and follow-up timing depend on the physician's comfort, experience, and preference. Infections of the skin or soft tissue are the primary contraindications to injections. The most common complications are local inflammatory reactions to the injectant. These reactions usually cause soreness for 24 to 48 hours, then spontaneously resolve. Follow-up after injections is usually scheduled within two to six weeks.
Family physicians often use joint injections for the diagnosis and treatment of common musculoskeletal conditions. This review discusses techniques using anatomic landmark–guided and ultrasound-guided injections and aspiration for the hip and knee; however, many other techniques are also available for injections. Family physicians are becoming more comfortable with the use of point-of-care ultrasonography (POCUS) for diagnosis and guided procedures; however, the terminology and techniques of POCUS are beyond the scope of this article. Intra-articular injections guided by POCUS are more accurate than anatomic landmark–guided injections of the hip and knee.1–10
SORT: KEY RECOMMENDATIONS FOR PRACTICE
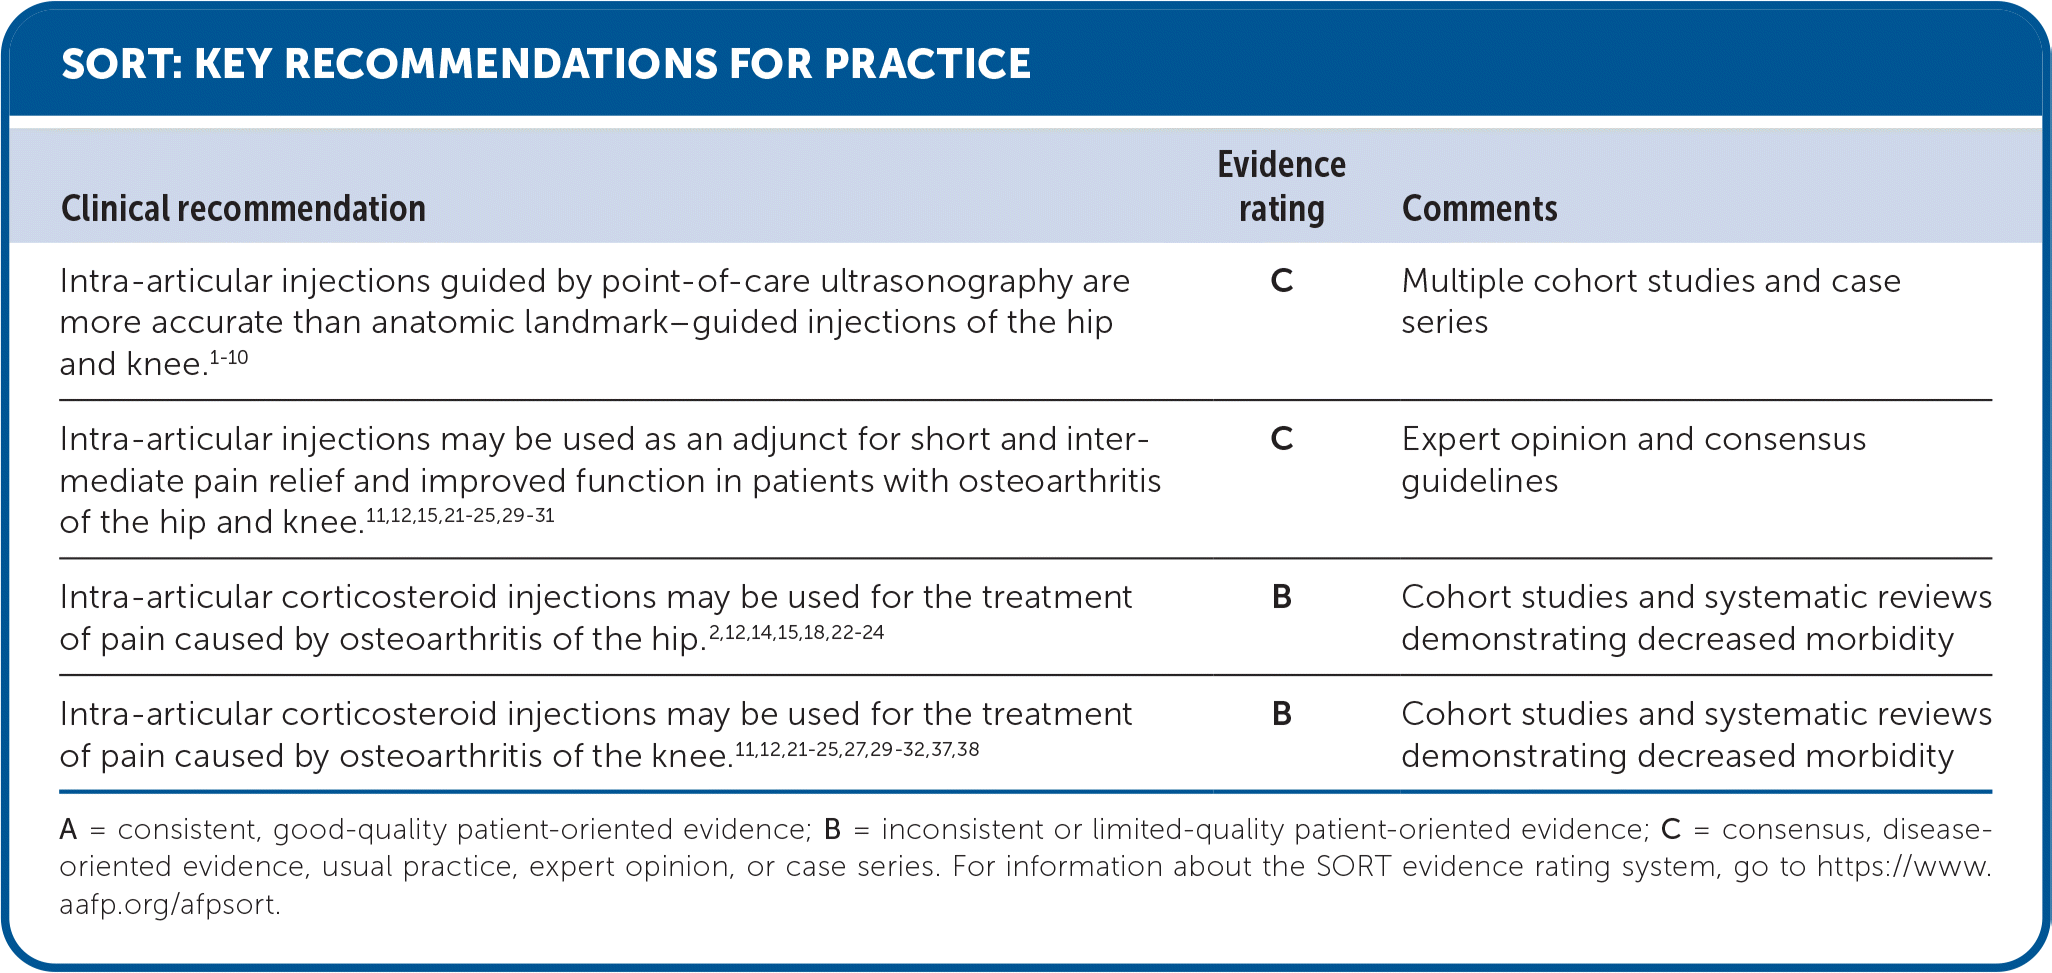
| Clinical recommendation | Evidence rating | Comments |
|---|---|---|
| Intra-articular injections guided by point-of-care ultrasonography are more accurate than anatomic landmark–guided injections of the hip and knee.1–10 | C | Multiple cohort studies and case series |
| Intra-articular injections may be used as an adjunct for short and intermediate pain relief and improved function in patients with osteoarthritis of the hip and knee.11,12,15,21–25,29–31 | C | Expert opinion and consensus guidelines |
| Intra-articular corticosteroid injections may be used for the treatment of pain caused by osteoarthritis of the hip.2,12,14,15,18,22–24 | B | Cohort studies and systematic reviews demonstrating decreased morbidity |
| Intra-articular corticosteroid injections may be used for the treatment of pain caused by osteoarthritis of the knee.11,12,21–25,27,29–32,37,38 | B | Cohort studies and systematic reviews demonstrating decreased morbidity |
A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.
Table 1 provides commonly reported needle, steroid, and anesthetic combinations.11,12 Table 2 identifies common steroids and the duration of action.12 Table 3 reviews the approximate duration of onset and action for anesthetics.12 eTable A compares the accuracy rates of hip and knee injection techniques using landmark and ultrasound guidance. eTable B provides resources for learning about POCUS.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
