
Narges Farahi, MD
Fareedat Oluyadi, MD
Andrea B. Dotson, MD, MSPH

American Family Physician. 2024;109(3):251-260.

Author disclosure: No relevant financial relationships.

Hypertensive disorders of pregnancy are a major contributor to maternal morbidity and mortality in the United States and include chronic and gestational hypertension, preeclampsia, HELLP (hemolysis, elevated liver enzymes, and low platelet count) syndrome, eclampsia, and chronic hypertension with superimposed preeclampsia. For patients with chronic hypertension, oral antihypertensive therapy should be initiated or titrated at a blood pressure threshold of 140/90 mm Hg or greater. Gestational hypertension and preeclampsia without severe features can be managed with blood pressure monitoring, laboratory testing for disease progression, antenatal testing for fetal well-being, and delivery at 37 weeks' gestation. The use of antihypertensive drugs to control nonsevere hypertension in the setting of gestational hypertension and preeclampsia does not improve outcomes and is not recommended. Antihypertensive therapy should be initiated expeditiously for acute-onset severe hypertension to prevent hemorrhagic stroke. Preeclampsia with severe features requires immediate stabilization and inpatient treatment with magnesium sulfate for seizure prophylaxis and antenatal corticosteroids (if preterm). Patients in the preterm period should receive antenatal corticosteroids without delaying delivery to complete courses. Hypertensive disorders of pregnancy can worsen or initially present after delivery and account for up to 44% of pregnancy-related deaths in the first six days postpartum. Patients should be monitored closely in the early postpartum period. Hypertensive disorders of pregnancy are linked to poor long-term maternal and fetal outcomes, including increased maternal lifetime risk of cardiovascular disease. Daily low-dose aspirin therapy starting at 12 to 16 weeks' gestation is safe and effective for reducing the risk of preeclampsia for patients with risk factors.

Hypertensive disorders of pregnancy affect 1 in 7 hospital deliveries in the United States, are strongly associated with maternal complications, and account for 7% of pregnancy-related deaths.1–3 Hypertensive disorders of pregnancy, which include chronic hypertension and pregnancy-associated hypertension (gestational hypertension, preeclampsia, HELLP [hemolysis, elevated liver enzymes, and low platelet count] syndrome, eclampsia, chronic hypertension with superimposed preeclampsia), increased in prevalence from 2017 to 2019.1,4 Pregnancy-associated hypertension more than doubles the risk of peripartum coronary disease, cardiomyopathy, and stroke, and accounts for 44% of maternal deaths in the first six days following delivery.4–6

SORT: KEY RECOMMENDATIONS FOR PRACTICE
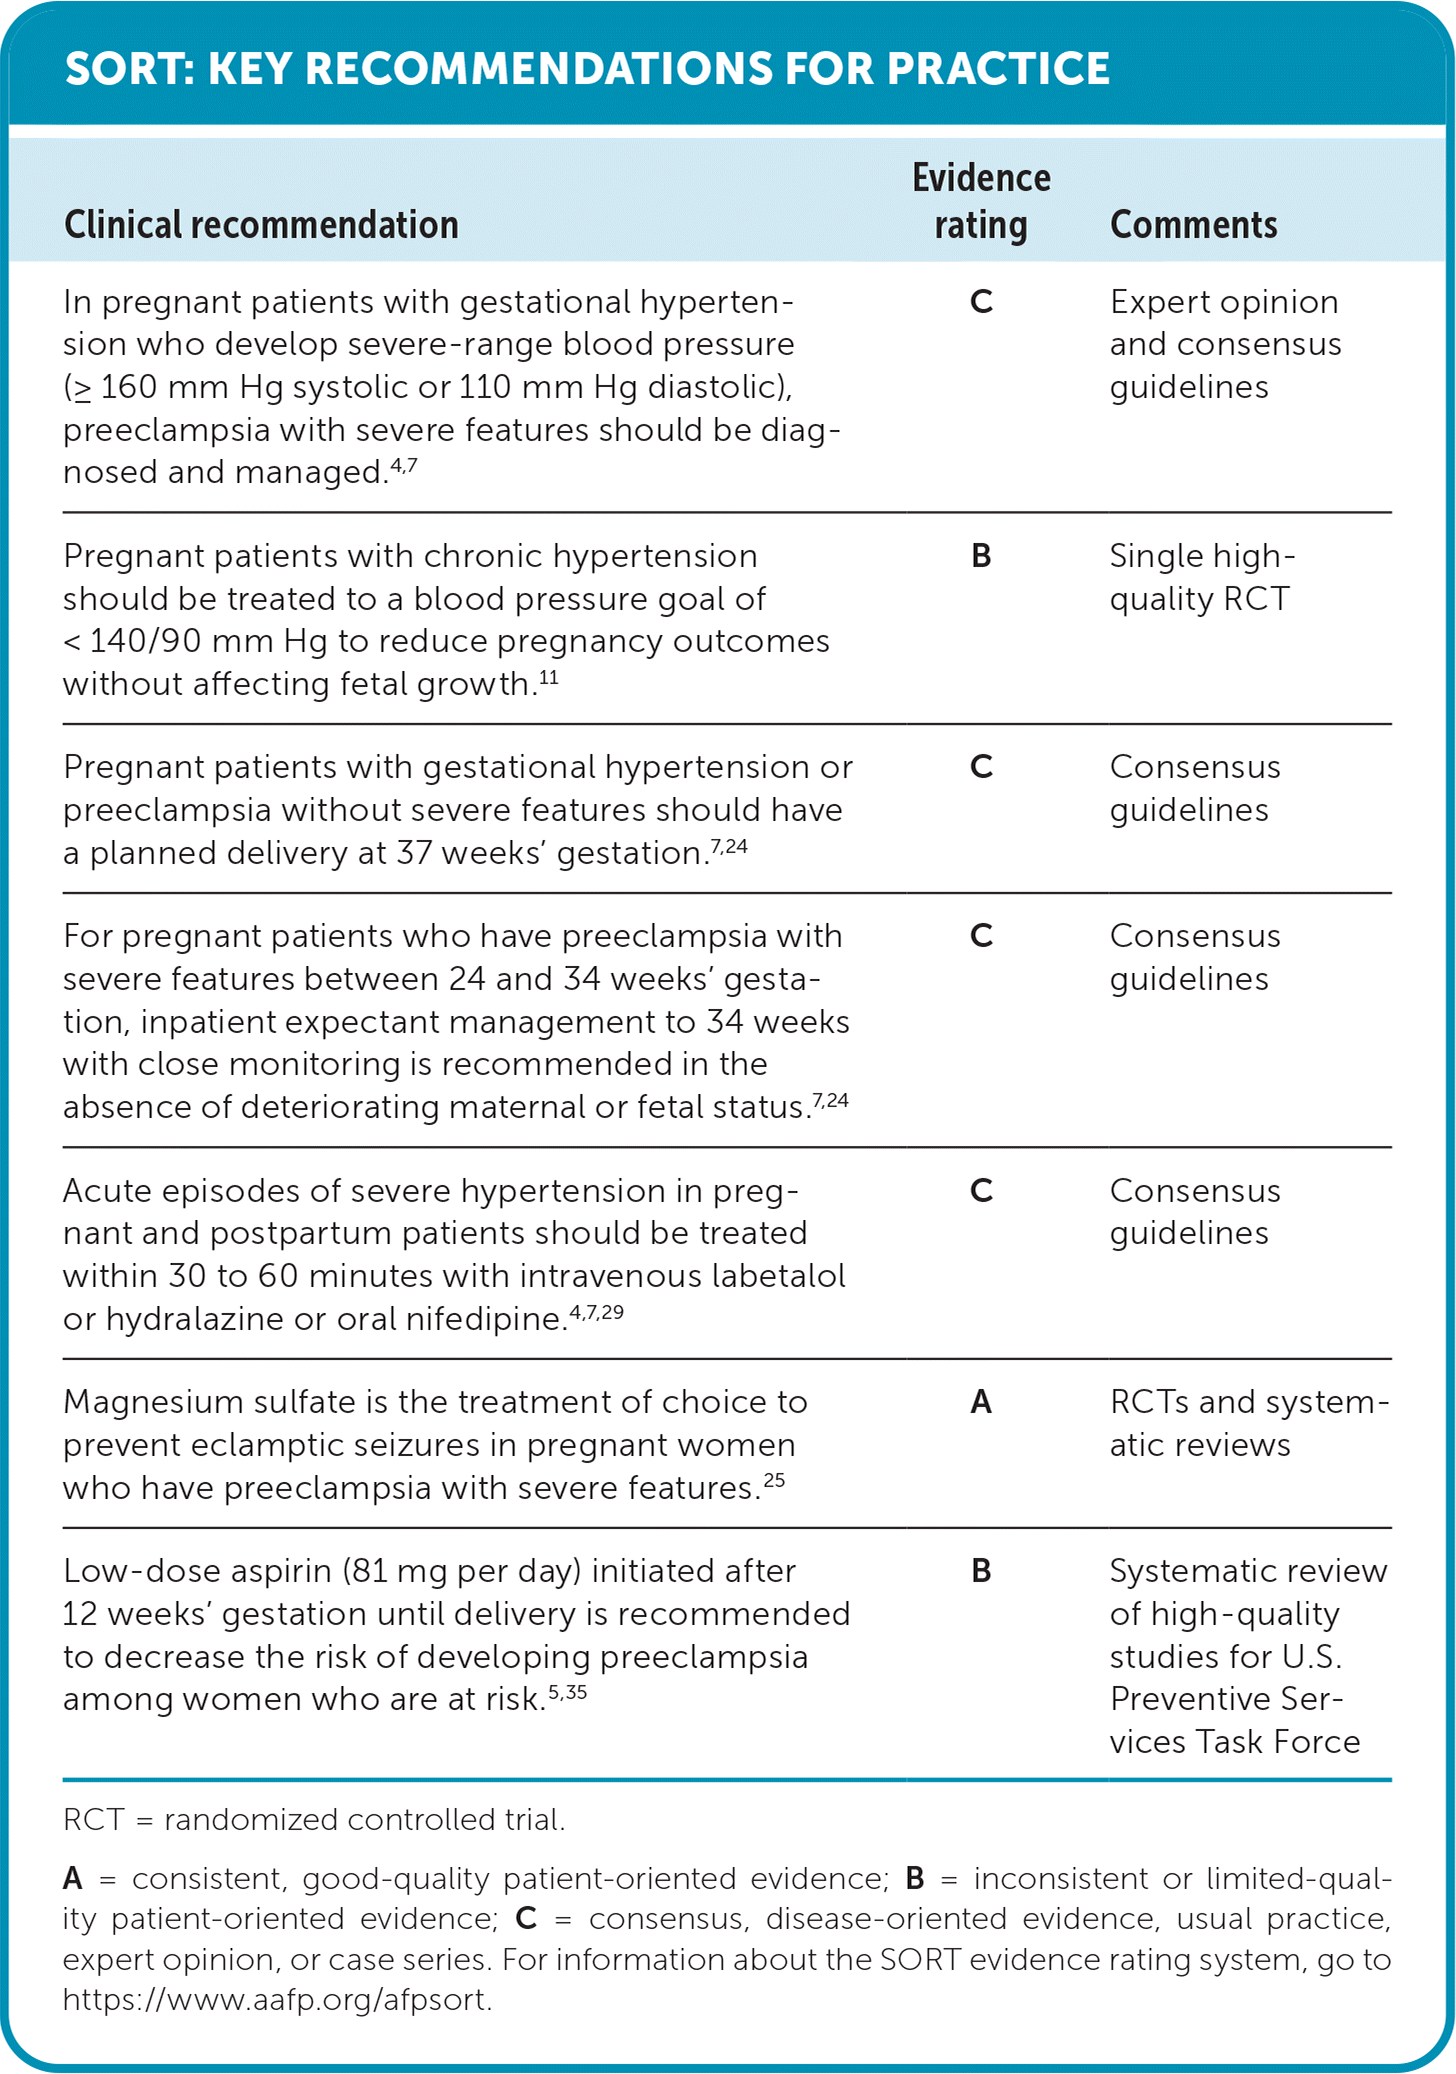
Clinical recommendation Evidence rating Comments
In pregnant patients with gestational hypertension who develop severe-range blood pressure (≥ 160 mm Hg systolic or 110 mm Hg diastolic), preeclampsia with severe features should be diagnosed and managed.4,7 C Expert opinion and consensus guidelines
Pregnant patients with chronic hypertension should be treated to a blood pressure goal of < 140/90 mm Hg to reduce pregnancy outcomes without affecting fetal growth.11 B Single high-quality RCT
Pregnant patients with gestational hypertension or preeclampsia without severe features should have a planned delivery at 37 weeks' gestation.7,24 C Consensus guidelines
For pregnant patients who have preeclampsia with severe features between 24 and 34 weeks' gestation, inpatient expectant management to 34 weeks with close monitoring is recommended in the absence of deteriorating maternal or fetal status.7,24 C Consensus guidelines
Acute episodes of severe hypertension in pregnant and postpartum patients should be treated within 30 to 60 minutes with intravenous labetalol or hydralazine or oral nifedipine.4,7,29 C Consensus guidelines
Magnesium sulfate is the treatment of choice to prevent eclamptic seizures in pregnant women who have preeclampsia with severe features.25 A RCTs and systematic reviews
Low-dose aspirin (81 mg per day) initiated after 12 weeks' gestation until delivery is recommended to decrease the risk of developing preeclampsia among women who are at risk.5,35 B Systematic review of high-quality studies for U.S. Preventive Services Task Force

RCT = randomized controlled trial.

A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.

NARGES FARAHI, MD, is an associate professor in the Department of Family Medicine at the University of North Carolina School of Medicine, Chapel Hill.

FAREEDAT OLUYADI, MD, IBCLC, is an assistant professor in the Department of Family Medicine at Charles R. Drew University of Medicine and Science, Los Angeles, Calif.

ANDREA B. DOTSON, MD, MSPH, IBCLC, is an assistant professor in the Department of Family Medicine and Community Health at Duke University School of Medicine, Durham, N.C.

Address correspondence to Narges Farahi, MD, University of North Carolina at Chapel Hill, 590 Manning Dr., Chapel Hill, NC 27599 (narges_farahi@med.unc.edu). Reprints are not available from the authors.

Author disclosure: No relevant financial relationships.

  1. 1.Ford ND, Cox S, Ko JY, et al. Hypertensive disorders in pregnancy and mortality at delivery hospitalization - United States, 2017–2019. MMWR Morb Mortal Wkly Rep. 2022;71(17):585-591.
  2. 2.Garovic VD, Dechend R, Easterling T, et al. Hypertension in pregnancy: diagnosis, blood pressure goals, and pharmacotherapy: a scientific statement from the American Heart Association [published correction appears in Hypertension. 2022; 79(3): e70]. Hypertension. 2022;79(2):e21-e41.
  3. 3.Creanga AA, Syverson C, Seed K, et al. Pregnancy-related mortality in the United States, 2011–2013. Obstet Gynecol. 2017;130(2):366-373.
  4. 4.American College of Obstetricians and Gynecologists’ Committee on Practice Bulletins—Obstetrics. ACOG practice bulletin no. 203: chronic hypertension in pregnancy. Obstet Gynecol. 2019;133(1):e26-e50.
  5. 5.Henderson JT, Vesco KK, Senger CA, et al. Aspirin use to prevent preeclampsia and related morbidity and mortality: updated evidence report and systematic review for the U.S. Preventive Services Task Force. JAMA. 2021;326(12):1192-1206.
  6. 6.Cameron NA, Everitt I, Seegmiller LE, et al. Trends in the incidence of new-onset hypertensive disorders of pregnancy in the United States, 2007 to 2019. J Am Heart Assoc. 2022;11(2):e023791.
  7. 7.Gestational hypertension and preeclampsia. ACOG practice bulletin no. 222. Obstet Gynecol. 2020;135(6):e237-e260.
  8. 8.Bartsch E, Medcalf KE, Park AL, et al.; High Risk of Pre-eclampsia Identification Group. Clinical risk factors for pre-eclampsia determined in early pregnancy. BMJ. 2016;353:i1753.
  9. 9.Hofmeyr GJ, Manyame S, Medley N, et al. Calcium supplementation commencing before or early in pregnancy, for preventing hypertensive disorders of pregnancy. Cochrane Database Syst Rev. 2019(9):CD011192.
  10. 10.Ives CW, Sinkey R, Rajapreyar I, et al. Preeclampsia-pathophysiology and clinical presentations. J Am Coll Cardiol. 2020;76(14):1690-1702.
  11. 11.Tita AT, Szychowski JM, Boggess K, et al.; Chronic Hypertension and Pregnancy Trial Consortium. Treatment for mild chronic hypertension during pregnancy. N Engl J Med. 2022;386(19):1781-1792.
  12. 12.Shahul S, Tung A, Minhaj M, et al. Racial disparities in comorbidities, complications, and maternal and fetal outcomes in women with preeclampsia/eclampsia. Hypertens Pregnancy. 2015;34(4):506-515.
  13. 13.Howell EA. Reducing disparities in severe maternal morbidity and mortality. Clin Obstet Gynecol. 2018;61(2):387-399.
  14. 14.Petersen EE, Davis NL, Goodman D, et al. Vital signs: pregnancy-related deaths, United States, 2011–2015, and strategies for prevention, 13 states, 2013–2017. MMWR Morb Mortal Wkly Rep. 2019;68(18):423-429.
  15. 15.Puia-Dumitrescu M, Greenberg RG, Younge N, et al. Disparities in the use of antenatal corticosteroids among women with hypertension in North Carolina. J Perinatol. 2020;40(3):456-462.
  16. 16.Battarbee AN, Sinkey RG, Harper LM, et al. Chronic hypertension in pregnancy. Am J Obstet Gynecol. 2020;222(6):532-541.
  17. 17.Hauspurg A, Jeyabalan A. Postpartum preeclampsia or eclampsia: defining its place and management among the hypertensive disorders of pregnancy. Am J Obstet Gynecol. 2022;226(2S):S1211-S1221.
  18. 18.Greenberg VR, Silasi M, Lundsberg LS, et al. Perinatal outcomes in women with elevated blood pressure and stage 1 hypertension. Am J Obstet Gynecol. 2021;224(5):521.e1-521.e11.
  19. 19.Whelton PK, Carey RM, Aronow WS, et al. 2017 ACC/AHA/AAPA/ABC/ACPM/AGS/APhA/ASH/ASPC/NMA/PCNA guideline for the prevention, detection, evaluation, and management of high blood pressure in adults: a report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines [published correction appears in Hypertension. 2018; 71(6): e140–e144]. Hypertension. 2018;71(6):e13-e115.
  20. 20.Barry MJ, Nicholson WK, Silverstein M, et al. Screening for hypertensive disorders of pregnancy: U.S. Preventive Services Task Force final recommendation statement. JAMA. 2023;330(11):1074-1082.
  21. 21.Sibai BM. Diagnosis, controversies, and management of the syndrome of hemolysis, elevated liver enzymes, and low platelet count. Obstet Gynecol. 2004;103(5 pt 1):981-991.
  22. 22.Mattar F, Sibai BM. Eclampsia. VIII. Risk factors for maternal morbidity. Am J Obstet Gynecol. 2000;182(2):307-312.
  23. 23.Indications for outpatient antenatal fetal surveillance: ACOG Committee Opinion Summary no. 828. Obstet Gynecol. 2021;137(6):1148-1151.
  24. 24.Hypertension in pregnancy: diagnosis and management. NICE guideline no. 133. National Institute for Health and Care Excellence. 2019.
  25. 25.Duley L, Gülmezoglu AM, Henderson-Smart DJ, et al. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane Database Syst Rev. 2010(11):CD000025.
  26. 26.Committee on Obstetric Practice. Committee opinion no. 713: antenatal corticosteroid therapy for fetal maturation. Obstet Gynecol. 2017;130(2):e102-e109.
  27. 27.Gyamfi-Bannerman C, Thom EA, Blackwell SC, et al.; NICHD Maternal–Fetal Medicine Units Network. Antenatal betamethasone for women at risk for late preterm delivery [published correction appears in N Engl J Med. 2023; 388(18): 1728]. N Engl J Med. 2016;374(14):1311-1320.
  28. 28.Woudstra DM, Chandra S, Hofmeyr GJ, et al. Corticosteroids for HELLP (hemolysis, elevated liver enzymes, low platelets) syndrome in pregnancy. Cochrane Database Syst Rev. 2010(9):CD008148.
  29. 29.Bernstein PS, Martin JN, Barton JR, et al. National Partnership for Maternal Safety: consensus bundle on severe hypertension during pregnancy and the postpartum period [published correction appears in Obstet Gynecol. 2019; 133(6): 1288]. Obstet Gynecol. 2017;130(2):347-357.
  30. 30.Steele DW, Adam GP, Saldanha IJ, et al. Management of Postpartum Hypertensive Disorders of Pregnancy. Agency for Healthcare Research and Quality; May 2023.
  31. 31.Hypertension in pregnancy. Report of the American College of Obstetricians and Gynecologists’ Task Force on hypertension in pregnancy. Obstet Gynecol. 2013;122(5):1122-1131.
  32. 32.Richards EMF, Giorgione V, Stevens O, et al. Low-dose aspirin for the prevention of superimposed preeclampsia in women with chronic hypertension. Am J Obstet Gynecol. 2023;228(4):395-408.
  33. 33.Liu YH, Zhang YS, Chen JY, et al. Comparative effectiveness of prophylactic strategies for preeclampsia: a network meta-analysis of randomized controlled trials. Am J Obstet Gynecol. 2023;228(5):535-546.
  34. 34.U.S. Preventive Services Task Force. Aspirin use to prevent preeclampsia and related morbidity and mortality: preventive medication. September 28, 2021. Accessed January 8, 2024. https://www.uspreventiveservicestaskforce.org/uspstf/recommendation/low-dose-aspirin-use-for-the-prevention-of-morbidity-and-mortality-from-preeclampsia-preventive-medication
  35. 35.Davidson KW, Barry MJ, Mangione CM, et al. Aspirin use to prevent preeclampsia and related morbidity and mortality: US Preventive Services Task Force Recommendation statement. JAMA. 2021;326(12):1186-1191.
  36. 36.Brouwers L, van der Meiden-van Roest AJ, Savelkoul C, et al. Recurrence of pre-eclampsia and the risk of future hypertension and cardiovascular disease. BJOG. 2018;125(13):1642-1654.
  37. 37.Brown MA, Magee LA, Kenny LC, et al.; International Society for the Study of Hypertension in Pregnancy (ISSHP). Hypertensive disorders of pregnancy: ISSHP classification, diagnosis, and management recommendations for international practice. Hypertension. 2018;72(1):24-43.
  38. 38.Magee LA, Brown MA, Hall DR, et al. The 2021 International Society for the Study of Hypertension in Pregnancy classification, diagnosis & management recommendations for international practice. Pregnancy Hypertens. 2022;27:148-169.
  39. 39.Behrens I, Basit S, Melbye M, et al. Risk of post-pregnancy hypertension in women with a history of hypertensive disorders of pregnancy: nationwide cohort study. BMJ. 2017;358:j3078.
  40. 40.Leeman L, Dresang LT, Fontaine P. Hypertensive disorders of pregnancy. Am Fam Physician. 2016;93(2):121-127.
  41. 41.Leeman L, Fontaine P. Hypertensive disorders of pregnancy. Am Fam Physician. 2008;78(1):93-100.
  42. 42.Wagner LK. Diagnosis and management of preeclampsia. Am Fam Physician. 2004;70(12):2317-2324.
  43. 43.Padden MO. HELLP syndrome: recognition and perinatal management. Am Fam Physician. 1999;60(3):829-839.

Copyright © 2026 by the American Academy of Family Physicians.

This content is owned by the AAFP. A person viewing it online may make one printout of the material and may use that printout only for his or her personal, non-commercial reference. This material may not otherwise be downloaded, copied, printed, stored, transmitted or reproduced in any medium, whether now known or later invented, except as authorized in writing by the AAFP. See permissions for copyright questions and/or permission requests.
