

A 35-year-old man presented with discomfort in his left eye. He had experienced eye discomfort for one day and noticed a bump on his lower eyelid when he woke the next day. The bump then enlarged and developed discharge. The patient had no vision changes. He had a history of seasonal allergic rhinitis.
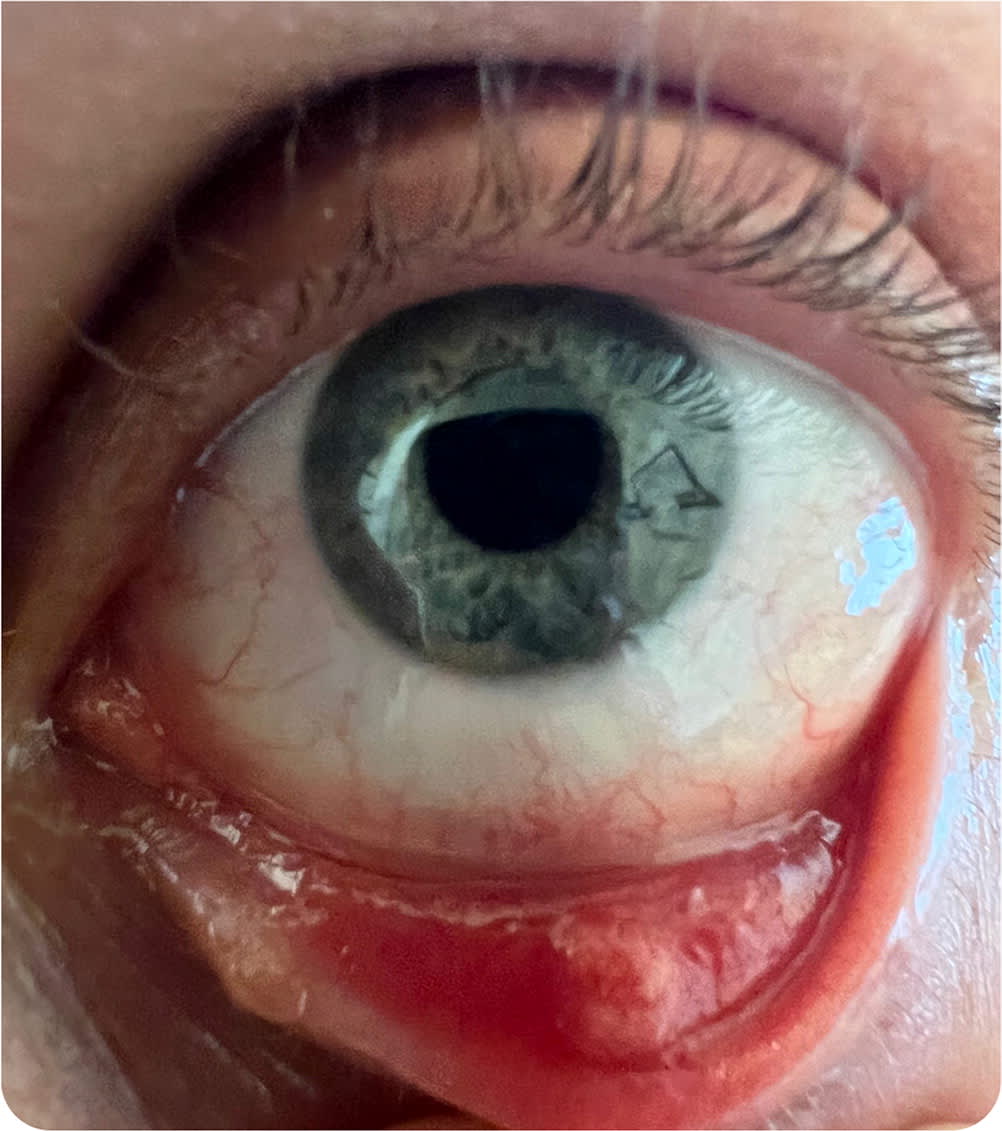
Physical examination revealed a single slightly firm, erythematous lesion on the lower eyelid (Figure 1). The patient's vital signs were normal.
FIGURE 1
Question
Based on the patient's history and physical examination, which one of the following is the most likely diagnosis?
- A. Chalazion.
- B. Hordeolum.
- C. Milia.
- D. Seborrheic keratosis.
- E. Xanthelasma.
Discussion
The answer is B: hordeolum, also known as a stye. A hordeolum develops rapidly (within 12 to 24 hours) and is characterized by local pain, swelling, and erythema. Hordeola are inflammatory lesions of the eyelids that can be external or internal. External hordeola are caused by clogging of the eyelash follicles or Zeis and Moll glands. Internal hordeola are caused by infection or inflammation of the meibomian glands. Staphylococcus aureus is the most common pathogen, but other bacteria can cause hordeola. They can also form without a bacterial source and may be sterile. Hordeola are more common in people with underlying skin conditions of the eyelids, such as rosacea and seborrheic dermatitis. Use of eye makeup, which can be contaminated with bacteria, may also increase the risk of hordeola.
Most hordeola will resolve without intervention within one to two weeks. Clinical trial data to support specific management recommendations are limited; most recommendations are based on data from case reports and clinical practices from more than 20 years ago.1 Drainage can be improved with frequent application of a warm, wet compress four or more times per day for about five to 10 minutes at a time. Physicians should emphasize that any massage or wiping should be gentle, and patients should be cautioned to avoid harsh rubbing and to never try to pop the hordeolum. Eye makeup should not be used until the hordeolum resolves. If the makeup could be contaminated, it should be replaced. If a hordeolum does not improve after two weeks of applying warm compresses, the patient should be referred to an ophthalmologist for further management, potentially including incision and drainage.
Patients with rosacea-associated blepharitis and frequent hordeola should be referred to an ophthalmologist for possible removal of lid margin debris. A combination of antibiotic and steroid ointment may be required, but ocular complications can occur with steroid use. Because hordeola can cause preseptal cellulitis in rare cases, antibiotics covering both S. aureus and streptococci should be used.2
A chalazion is a painless, slow-growing lump on the eyelid caused by a blocked oil gland. It is often located on the upper eyelid but can occur on the lower eyelid. Chalazions are not usually red or swollen, and they do not cause discomfort. Diagnosis is based on the appearance, which is typically a nonfluctuant, nonerythematous nodule that is smaller than 1 cm. Chalazions grow more slowly than hordeola, developing over days to weeks. They do not require treatment and usually resolve spontaneously within a few weeks. However, if a chalazion is large or bothersome, it can be removed by an ophthalmologist.3
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
