

A 20-year-old man presented five days after developing odynophagia, rhinorrhea, and cough. His cough and rhinorrhea had improved without intervention, but the odynophagia had worsened. He also had dysuria and painful lesions on his lips. The patient did not have a history of similar episodes. He had not used any medications recently, including over-the-counter medications, and did not have a history of allergies.
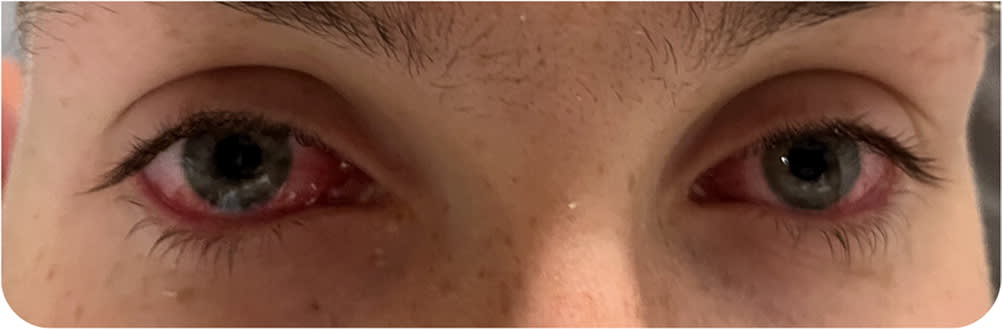
There were superficial white plaques on his tongue that could be scraped off and superficial erosions and ulcerations on his lips and buccal surface (Figure 1). Physical examination also revealed bilateral conjunctival injection (Figure 2). A small erosion was present on his urethra. There was no other skin involvement.
FIGURE 1
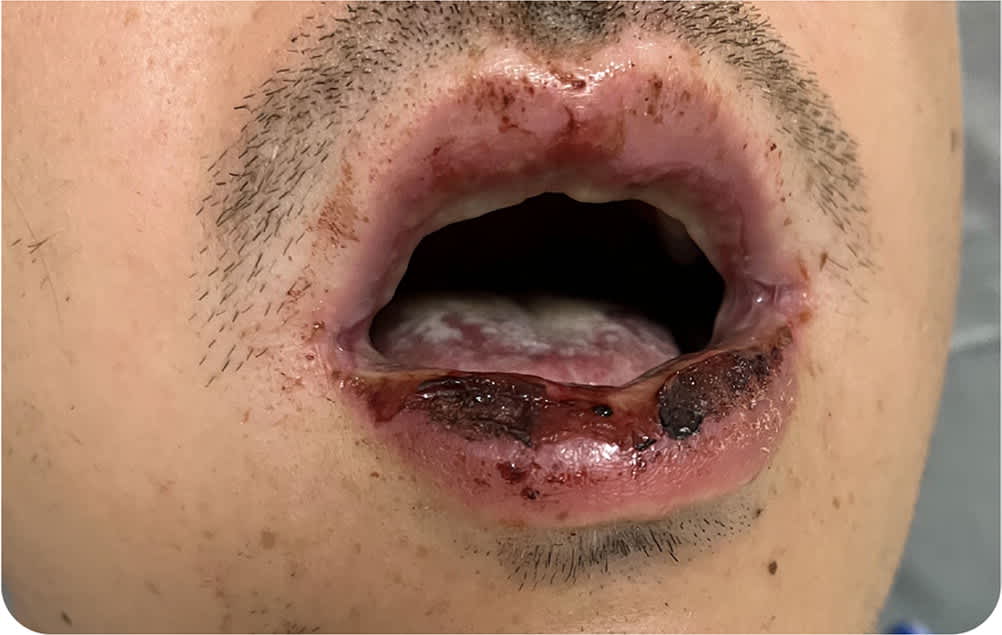
FIGURE 2
Question
Based on the patient's history and physical examination findings, which one of the following is the most likely diagnosis?
- A. Behçet syndrome.
- B. Erythema multiforme.
- C. Reactive infectious mucocutaneous eruption.
- D. Stevens-Johnson syndrome.
Discussion
The answer is C: reactive infectious mucocutaneous eruption (RIME). RIME is an emerging diagnostic term used to describe mucocutaneous eruptions following a viral or bacterial respiratory tract infection. The syndrome was originally described following Mycoplasma pneumoniae infections in children.1 The condition is now being described following infections with a range of respiratory pathogens, including adenovirus, Chlamydia pneumoniae, and influenza, and can occur at any age.1–3 The syndrome typically presents in children or adolescents following a respiratory tract infection with the development of mucosal lesions but minimal cutaneous involvement.4
RIME is diagnosed based on history and physical examination findings, with the exclusion of other disorders. Diagnosis requires the involvement of two or more mucosal sites, involvement of less than 10% of skin surface area, and a recent prodromal infection. When cutaneous lesions are present, they are usually macules and papules as opposed to targetoid or bullous lesions. If the patient has persistent upper respiratory symptoms, testing to rule out M. pneumoniae or other potential causes of the inciting infection may be indicated. RIME is typically mild and self-limiting.
Treatment of RIME is supportive, with little evidence backing the use of corticosteroids and other anti-inflammatory medications.1 Additional treatment of the underlying infection may be indicated, depending on the causative pathogen.
Behçet syndrome presents as recurrent aphthous ulcers of the mouth and other mucous membranes. It also has systemic presentations, including ocular and cardiovascular complications. Uveitis is the typical ocular finding, whereas conjunctivitis is uncommon. The diagnosis requires the patient to have recurrent episodes without other causes for the lesions.5
Erythema multiforme may present as mucocutaneous eruptions affecting less than 10% of the skin surface area, similar to those seen in this patient. However, the disease more often presents on distal extremities as classic targetoid lesions. The condition is associated with various conditions, including medication use and infection.
Stevens-Johnson syndrome can present as mucosal findings similar to RIME but typically features widespread purpuric macules and patches involving the skin and mucous membranes. The associated illness is more severe than RIME and usually leads to hospitalization. Medication use is typically the underlying cause; implicated medications include sulfonamides, anticonvulsants, and gout therapies.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
