
Gallstone Disease: Common Questions and Answers

Hiten Patel, MD, MPH
Jacqueline Jepsen, MD

American Family Physician. 2024;109(6):518-524.

Author disclosure: No relevant financial relationships.

In the United States, 10% to 15% of adults are affected by gallstones, and cholesterol gallstones are the most prevalent subtype. Risk factors for developing gallstone disease include female sex; older age; certain medications; and having type 2 diabetes mellitus, nonalcoholic fatty liver disease, obesity, rapid weight loss, or hemolytic anemia. Nearly 80% of gallstones are found incidentally and remain asymptomatic. When symptomatic, gallstone disease usually presents as sudden onset right upper quadrant or epigastric abdominal pain. Common complications of gallstones include cholecystitis, choledocholithiasis, gallstone pancreatitis, and ascending cholangitis. The Murphy sign is a specific physical examination finding for acute cholecystitis. Ultrasonography is the initial imaging choice for detecting gallstones and acute cholecystitis. A hepatobiliary iminodiacetic acid (HIDA) scan can be used to evaluate for cholecystitis in patients with negative or equivocal ultrasound findings. Magnetic resonance cholangiopancreatography (MRCP) is an accurate, noninvasive diagnostic test to identify choledocholithiasis, certain malignancies, and biliary obstruction. Nonsteroidal anti-inflammatory drugs are safe and effective in treating pain from acute cholecystitis and biliary colic. Laparoscopic cholecystectomy is the treatment of choice for most patients with biliary colic or acute cholecystitis. Ursodeoxycholic acid and chenodeoxycholic acid should not routinely be used to treat gallstone disease, but they can be used as a nonsurgical alternative for certain patients. Postcholecystectomy syndrome is a potential postoperative complication that presents with abdominal pain, bloating, and diarrhea. (Am Fam Physician. 2024;109(6):518-524. Copyright © 2024 American Academy of Family Physicians.)

Gallstones, or cholelithiasis, are highly prevalent, affecting an estimated 10% to 15% of U.S. adults.1,2 Approximately 80% of all gallstones are cholesterol gallstones, which form because of precipitation of cholesterol.1,3 Black pigment gallstones (10% to 15%) comprise calcium bilirubinate, formed from unconjugated bilirubin deposition, often secondary to chronic hemolysis.2,3 Brown pigment stones (5%) are usually associated with biliary infections.3 Evidence-based answers to common questions about gallstone disease are discussed in this article.

WHAT'S NEW ON THIS TOPIC

Gallstones
Recent meta-analyses have shown that dipeptidyl-peptidase-4 inhibitors (odds ratio = 1.22) and glucagon-like peptide-1 receptor agonists (relative risk = 1.27) increase the risk of gallstone disease, with greater risk in patients with longer duration of use (longer than 26 weeks).
A 2016 Cochrane review showed that nonsteroidal anti-inflammatory drugs provide greater relief from biliary pain compared with placebo (number needed to treat = 3) and antispasmodics (number needed to treat = 3) and no difference in pain control compared with opiates.
A systematic review of patients who underwent cholecystectomy found that 13% developed postcholecystectomy diarrhea.

SORT: KEY RECOMMENDATIONS FOR PRACTICE
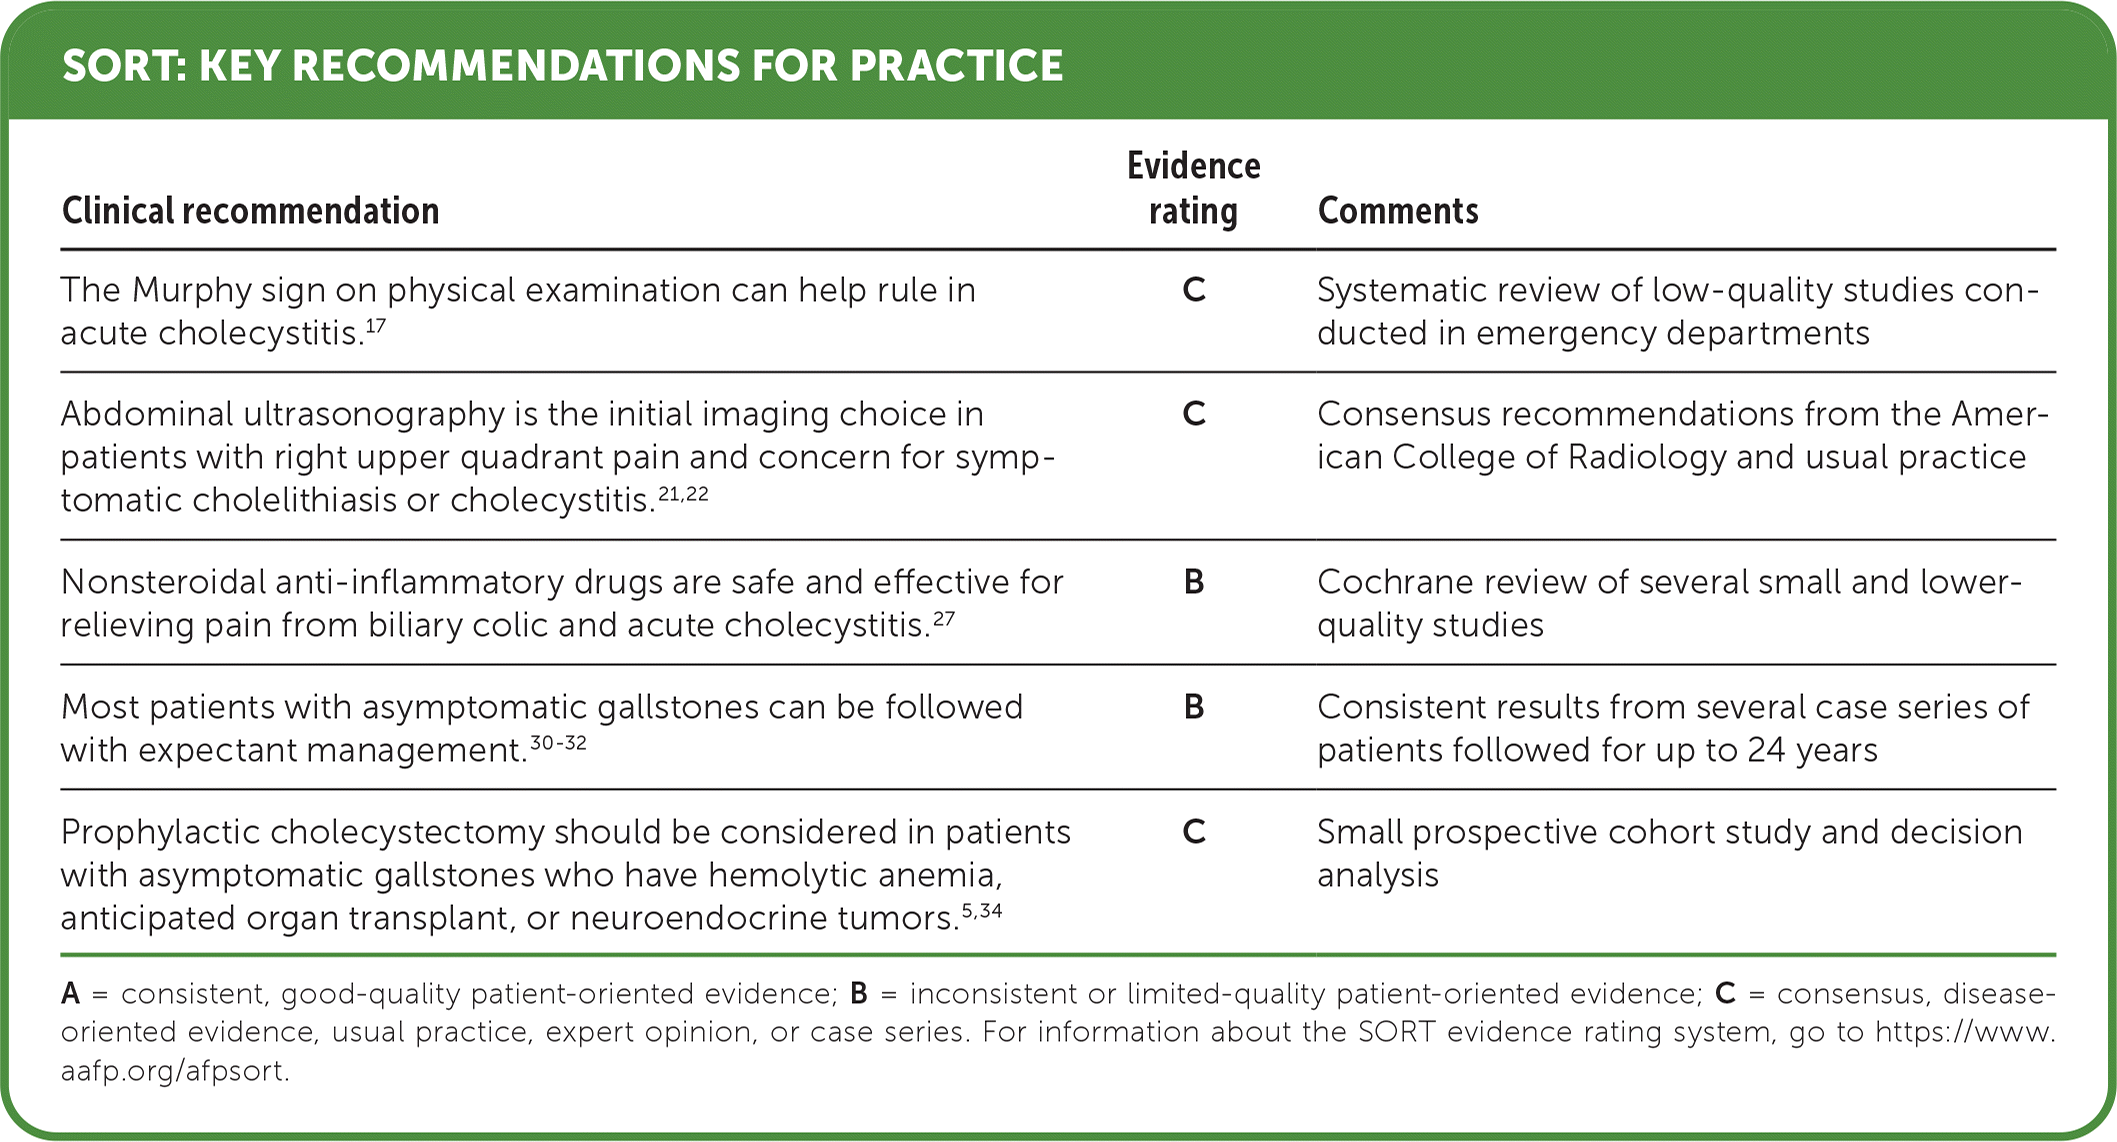
Clinical recommendation Evidence rating Comments
The Murphy sign on physical examination can help rule in acute cholecystitis.17 C Systematic review of low-quality studies conducted in emergency departments
Abdominal ultrasonography is the initial imaging choice in patients with right upper quadrant pain and concern for symptomatic cholelithiasis or cholecystitis.21,22 C Consensus recommendations from the American College of Radiology and usual practice
Nonsteroidal anti-inflammatory drugs are safe and effective for relieving pain from biliary colic and acute cholecystitis.27 B Cochrane review of several small and lower-quality studies
Most patients with asymptomatic gallstones can be followed with expectant management.30–32 B Consistent results from several case series of patients followed for up to 24 years
Prophylactic cholecystectomy should be considered in patients with asymptomatic gallstones who have hemolytic anemia, anticipated organ transplant, or neuroendocrine tumors.5,34 C Small prospective cohort study and decision analysis

A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease- oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.

HITEN PATEL, MD, MPH, is an assistant professor and associate program director in the Department of Family and Community Medicine at The Ohio State University Wexner Medical Center, Columbus.

JACQUELINE JEPSEN, MD, is a resident physician in the Department of Family and Community Medicine at The Ohio State University Wexner Medical Center.

Address correspondence to Hiten Patel, MD, MPH, The Ohio State University College of Medicine, 2231 N High St., Columbus, OH 43201 (hiten.patel@osumc.edu). Reprints are not available from the authors.

Author disclosure: No relevant financial relationships.

  1. 1.Abraham S, Rivero HG, Erlikh IV, et al. Surgical and nonsurgical management of gallstones. Am Fam Physician. 2014;89(10):795-802.
  2. 2.Portincasa P, Moschetta A, Palasciano G. Cholesterol gallstone disease. Lancet. 2006;368(9531):230-239.
  3. 3.Cariati A. Gallstone classification in western countries. Indian J Surg. 2015;77(suppl 2):376-380.
  4. 4.Pak M, Lindseth G. Risk factors for cholelithiasis. Gastroenterol Nurs. 2016;39(4):297-309.
  5. 5.Muroni M, Loi V, Lionnet F, et al. Prophylactic laparoscopic cholecystectomy in adult sickle cell disease patients with cholelithiasis: a prospective cohort study. Int J Surg. 2015;22:62-66.
  6. 6.Jaruvongvanich V, Sanguankeo A, Upala S. Significant association between gallstone disease and nonalcoholic fatty liver disease: a systematic review and meta-analysis. Dig Dis Sci. 2016;61(8):2389-2396.
  7. 7.He L, Wang J, Ping F, et al. Dipeptidyl peptidase-4 inhibitors and gall-bladder or biliary disease in type 2 diabetes: systematic review and pairwise and network meta-analysis of randomised controlled trials. BMJ. 2022;377:e068882.
  8. 8.He L, Wang J, Ping F, et al. Association of glucagon-like peptide-1 receptor agonist use with risk of gallbladder and biliary diseases: a systematic review and meta-analysis of randomized clinical trials. JAMA Intern Med. 2022;182(5):513-519.
  9. 9.Talha A, Abdelbaki T, Farouk A, et al. Cholelithiasis after bariatric surgery, incidence, and prophylaxis: randomized controlled trial. Surg Endosc. 2020;34(12):5331-5337.
  10. 10.Aune D, Vatten LJ. Diabetes mellitus and the risk of gallbladder disease: a systematic review and meta-analysis of prospective studies. J Diabetes Complications. 2016;30(2):368-373.
  11. 11.Lim J, Wirth J, Wu K, et al. Obesity, adiposity, and risk of symptomatic gallstone disease according to genetic susceptibility. Clin Gastroenterol Hepatol. 2022;20(5):e1083-e1120.
  12. 12.Hess E, Thumbadoo RP, Thorne E, et al. Gallstones in pregnancy. Br J Hosp Med (Lond). 2021;82(2):1-8.
  13. 13.Cirillo DJ, Wallace RB, Rodabough RJ, et al. Effect of estrogen therapy on gallbladder disease. JAMA. 2005;293(3):330-339.
  14. 14.Haley K. Congenital hemolytic anemia. Med Clin North Am. 2017;101(2):361-374.
  15. 15.Gallaher JR, Charles A. Acute cholecystitis: a review. JAMA. 2022;327(10):965-975.
  16. 16.Wilkins T, Agabin E, Varghese J, et al. Gallbladder dysfunction: cholecystitis, choledocholithiasis, cholangitis, and biliary dyskinesia. Prim Care. 2017;44(4):575-597.
  17. 17.Jain A, Mehta N, Secko M, et al. History, physical examination, laboratory testing, and emergency department ultrasonography for the diagnosis of acute cholecystitis. Acad Emerg Med. 2017;24(3):281-297.
  18. 18.Trowbridge RL, Rutkowski NK, Shojania KG. Does this patient have acute cholecystitis [published correction appears in JAMA. 2009; 302(7): 739]?. JAMA. 2003;289(1):80-86.
  19. 19.Gillaspie DB, Davis KA, Schuster KM. Total bilirubin trend as a predictor of common bile duct stones in acute cholecystitis and symptomatic cholelithiasis. Am J Surg. 2019;217(1):98-102.
  20. 20.Vaynshtein J, Sabbag G, Pinsk I, et al. Predictors for choledocholitiasis in patients undergoing endoscopic ultrasound. Scand J Gastroenterol. 2018;53(3):335-339.
  21. 21.Russo GK, Zaheer A, Kamel IR, et al.; American College of Radiology. ACR Appropriateness Criteria.© Right upper quadrant pain. Updated 2022. Accessed July 2023. https://acsearch.acr.org/docs/69474/Narrative/
  22. 22.Ross M, Brown M, McLaughlin K, et al. Emergency physician–performed ultrasound to diagnose cholelithiasis: a systematic review. Acad Emerg Med. 2011;18(3):227-235.
  23. 23.Kiewiet JJS, Leeuwenburgh MMN, Bipat S, et al. A systematic review and meta-analysis of diagnostic performance of imaging in acute cholecystitis. Radiology. 2012;264(3):708-720.
  24. 24.Fernández-Esparrach G, Ginès A, Sánchez M, et al. Comparison of endoscopic ultrasonography and magnetic resonance cholangiopancreatography in the diagnosis of pancreatobiliary diseases: a prospective study. Am J Gastroenterol. 2007;102(8):1632-1639.
  25. 25.Gurusamy KS, Giljaca V, Takwoingi Y, et al. Ultrasound versus liver function tests for diagnosis of common bile duct stones. Cochrane Database Syst Rev. 2015(2):CD011548.
  26. 26.De Castro VL, Moura EG, Chaves DM, et al. Endoscopic ultrasound versus magnetic resonance cholangiopancreatography in suspected choledocholithiasis: a systematic review. Endosc Ultrasound. 2016;5(2):118-128.
  27. 27.Fraquelli M, Casazza G, Conte D, et al. Non-steroid anti-inflammatory drugs for biliary colic. Cochrane Database Syst Rev. 2016(9):CD006390.
  28. 28.Olsen JC, McGrath NA, Schwarz DG, et al. A double-blind randomized clinical trial evaluating the analgesic efficacy of ketorolac versus butorphanol for patients with suspected biliary colic in the emergency department. Acad Emerg Med. 2008;15(8):718-722.
  29. 29.Akhgar A, Pouryousefi T, Nejati A, et al. The efficacy of intravenous lidocaine and its side effects in comparison with intravenous morphine sulfate in patients admitted to the ED with right upper abdominal pain suspected of biliary colic. Am J Emerg Med. 2021;44:300-305.
  30. 30.McSherry CK, Ferstenberg H, Calhoun WF, et al. The natural history of diagnosed gallstone disease in symptomatic and asymptomatic patients. Ann Surg. 1985;202(1):59-63.
  31. 31.Schmidt M, Hausken T, Glambek I, et al. A 24-year controlled follow-up of patients with silent gallstones showed no long-term risk of symptoms or adverse events leading to cholecystectomy. Scand J Gastroenterol. 2011;46(7–8):949-954.
  32. 32.Friedman GD. Natural history of asymptomatic and symptomatic gallstones. Am J Surg. 1993;165(4):399-404.
  33. 33.Murshid KR. Asymptomatic gallstones: should we operate?. Saudi J Gastroenterol. 2007;13(2):57-69.
  34. 34.Lee BJH, Yap QV, Low JK, et al. Cholecystectomy for asymptomatic gallstones: Markov decision tree analysis. World J Clin Cases. 2022;10(29):10399-10412.
  35. 35.Graham SM, Flowers JL, Schweitzer E, et al. The utility of prophylactic laparoscopic cholecystectomy in transplant candidates. Am J Surg. 1995;169(1):44-48 , discussion 48–49.
  36. 36.Bond LR, Hatty SR, Horn ME, et al. Gall stones in sickle cell disease in the United Kingdom. Br Med J (Clin Res Ed). 1987;295(6592):234-236.
  37. 37.Hofmann AF. Medical dissolution of gallstones by oral bile acid therapy. Am J Surg. 1989;158(3):198-204.
  38. 38.Petroni ML, Jazrawi RP, Pazzi P, et al.; British-Italian gallstone study group. Ursodeoxycholic acid alone or with chenodeoxycholic acid for dissolution of cholesterol gallstones: a randomized multicentre trial. Aliment Pharmacol Ther. 2001;15(1):123-128.
  39. 39.May GR, Sutherland LR, Shaffer EA. Efficacy of bile acid therapy for gallstone dissolution: a meta-analysis of randomized trials. Aliment Pharmacol Ther. 1993;7(2):139-148.
  40. 40.Hyun JJ, Lee HS, Kim CD, et al. Efficacy of magnesium trihydrate of ursodeoxycholic acid and chenodeoxycholic acid for gallstone dissolution: a prospective multicenter trial. Gut Liver. 2015;9(4):547-555.
  41. 41.O'Donnell LD, Heaton KW. Recurrence and re-recurrence of gall stones after medical dissolution: a longterm follow up. Gut. 1988;29(5):655-658.
  42. 42.Uy MC, Talingdan-Te MC, Espinosa WZ, et al. Ursodeoxycholic acid in the prevention of gallstone formation after bariatric surgery: a meta-analysis. Obes Surg. 2008;18(12):1532-1538.
  43. 43.Mulliri A, Menahem B, Alves A, et al. Ursodeoxycholic acid for the prevention of gallstones and subsequent cholecystectomy after bariatric surgery: a meta-analysis of randomized controlled trials. J Gastroenterol. 2022;57(8):529-539.
  44. 44.Ahmad DS, Faulx A. Management of postcholecystectomy biliary complications: a narrative review. Am J Gastroenterol. 2020;115(8):1191-1198.
  45. 45.Radunovic M, Lazovic R, Popovic N, et al. Complications of laparoscopic cholecystectomy: our experience from a retrospective analysis. Open Access Maced J Med Sci. 2016;4(4):641-646.
  46. 46.Schofer JM. Biliary causes of postcholecystectomy syndrome. J Emerg Med. 2010;39(4):406-410.
  47. 47.Farrugia A, Attard JA, Khan S, et al. Postcholecystectomy diarrhoea rate and predictive factors: a systematic review of the literature. BMJ Open. 2022;12(2):e046172.
  48. 48.Sadowski DC, Camilleri M, Chey WD, et al. Canadian Association of Gastroenterology clinical practice guideline on the management of bile acid diarrhea. Clin Gastroenterol Hepatol. 2020;18(1):24.e1-41.e1.
  49. 49.Bellows CF, Berger DH, Crass RA. Management of gallstones. Am Fam Physician. 2005;72(4):637-642.
  50. 50.Ahmed A, Cheung RC, Keeffe EB. Management of gallstones and their complications. Am Fam Physician. 2000;61(6):1673-1680.

Copyright © 2026 by the American Academy of Family Physicians.

This content is owned by the AAFP. A person viewing it online may make one printout of the material and may use that printout only for his or her personal, non-commercial reference. This material may not otherwise be downloaded, copied, printed, stored, transmitted or reproduced in any medium, whether now known or later invented, except as authorized in writing by the AAFP. See permissions for copyright questions and/or permission requests.
