

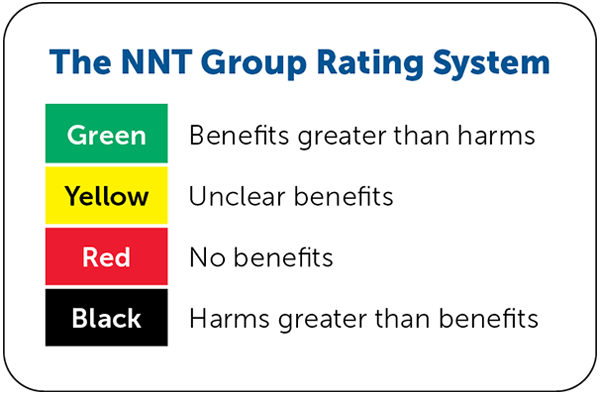
Details for This Review
Study Population: Nine randomized controlled trials from 16 high-income countries, including 3,424 adults with treatment-resistant depression (lack of response after at least two trials of antidepressant monotherapy) who met the Diagnostic and Statistical Manual of Mental Disorders, 4th and 5th eds., criteria for major depressive disorder and were having a current depressive episode
Efficacy End Points: Primary outcome: response to treatment (greater than 50% improvement in depressive symptoms on validated depression score) at eight weeks; secondary outcomes: response to treatment after two and 18 weeks, remission after eight weeks, social functioning or adjustment, health-related quality of life
Harm End Points: Primary outcomes: dropouts due to any cause or adverse effects at eight weeks; secondary outcomes: any adverse effects, specific adverse effects (e.g., akathisia [restlessness], weight gain)
THE NUMBERS

| Benefits |
| 1 in 16 had positive response to treatment at eight weeks |
| 1 in 22 had remission of depression at eight weeks |
| Harms |
| 1 in 38 withdrew from the study due to any cause |
| 1 in 58 withdrew from the study due to adverse effects |
| 1 in 20 experienced akathisia or weight gain |
Narrative: Major depressive disorder affects more than 300 million people of all ages worldwide.1 Depression is a leading cause of disability, impairs quality of life and psychosocial development, and increases morbidity and mortality.1,2 Major depressive disorder is severe and episodic, with episodes lasting six to 12 months on average.3 Approximately 50% of patients do not achieve remission with first-line treatments, including selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors, and about two-thirds of patients require further trials of antidepressant therapies to achieve remission.2,4
Treatment-resistant depression is defined by chronic and persistent symptoms of low mood and repeated major depressive disorder episodes after at least two adequate antidepressant treatment trials.2,4 Treatment-resistant depression occurs in up to 60% of patients with a major depressive disorder.2 Differentiating treatment-resistant depression from persistent depressive disorder (low mood occurring for at least two years without repeated major depressive disorder episodes) is essential because up to 40% of dysthymic symptoms are considered treatment resistant. This is key because studies have shown that antidepressants and psychotherapy are less effective for persistent depressive disorder than for nonchronic major depressive disorder, including treatment-resistant depression.3
This Cochrane review focused on the effectiveness of brexpiprazole (Rexulti) as an adjunctive therapy for treatment of treatment-resistant depression.4 Brexpiprazole is a second-generation antipsychotic that functions as a partial agonist of dopamine and serotonin receptors. Second-generation antipsychotics are often preferred over first-generation medications because they have a lower risk of extrapyramidal symptoms. However, adverse effects can include metabolic disturbances such as weight gain, hyper-lipidemia, and hyperglycemia.5
The Cochrane review included patients with a history of nonresponse to one or more antidepressant monotherapies and compared brexpiprazole as adjunct treatment with placebo or another antidepressant (e.g., duloxetine [Cymbalta], escitalopram, fluoxetine, paroxetine, sertraline, extended-release venlafaxine). Inclusion criteria for all studies required a diagnosis of major depressive disorder with a current episode. Primary outcomes were response to treatment (defined as greater than 50% improvement in depressive symptoms on a validated depression score), number of dropouts due to any cause, and number of dropouts due to adverse effects—all measured at eight weeks. Secondary outcomes included response to treatment after two and 18 weeks, remission after eight weeks, social functioning or adjustment, and health-related quality of life.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
