

Clinical Question
Does melatonin prevent hospital-acquired delirium?
Evidence-Based Answer
Melatonin should not be used to prevent hospital-acquired delirium because it does not reduce the incidence, duration, or complications of delirium, including increased length of stay or mortality. (Strength of Recommendation [SOR]: A, meta-analysis of randomized controlled trials [RCTs].) Melatonin does not decrease the incidence of intensive care unit (ICU) delirium (SOR: B, conflicting meta-analyses of RCTs) or postoperative delirium (SOR: A, meta-analysis of RCTs). Melatonin is not currently recommended for the prevention of delirium in patients admitted to the hospital. (SOR: C, expert opinion.) However, ramelteon (Rozerem), a melatonin receptor agonist, may lower the incidence of delirium in hospitalized patients. (SOR: A, meta-analysis of RCTs.)
Evidence Summary
A 2021 systematic review and meta-analysis evaluated 14 RCTs (n = 1,712) to determine whether melatonin and melatonin receptor agonists would prevent delirium in hospitalized adults.1 The trials randomized patients (mean age = 34 to 84 years) to melatonin (0.5 to 50 mg per kg from one to 14 days), ramelteon (8 mg per day from one day up to the length of stay), placebo, or usual care. The primary outcome was the incidence of delirium; secondary outcomes included duration of delirium, length of hospitalization, and mortality. Treatment with melatonergics decreased the risk of delirium (relative risk [RR] = 0.61; 95% CI, 0.42 to 0.89; P = .009; I2 = 66%; number needed to treat [NNT] = 13). However, subgroup analysis by treatment drug showed that ramelteon, but not melatonin, lowered the risk of delirium (Table 1).1 Additional subanalyses by care setting found that melatonergics reduced delirium in patients admitted to the ICU but not in surgical (postoperative) or medical patients. Neither of the melatonergics decreased the duration of delirium, length of hospital stay, or mortality. Results in the meta-analysis were limited by high heterogeneity in dose, duration, and formulation of medications; small sample size of included RCTs; and evidence of publication bias.
TABLE 1. Meta-analysis Results of the Effect of Melatonin Receptor Agonists on the Incidence of Delirium in Hospitalized Patients
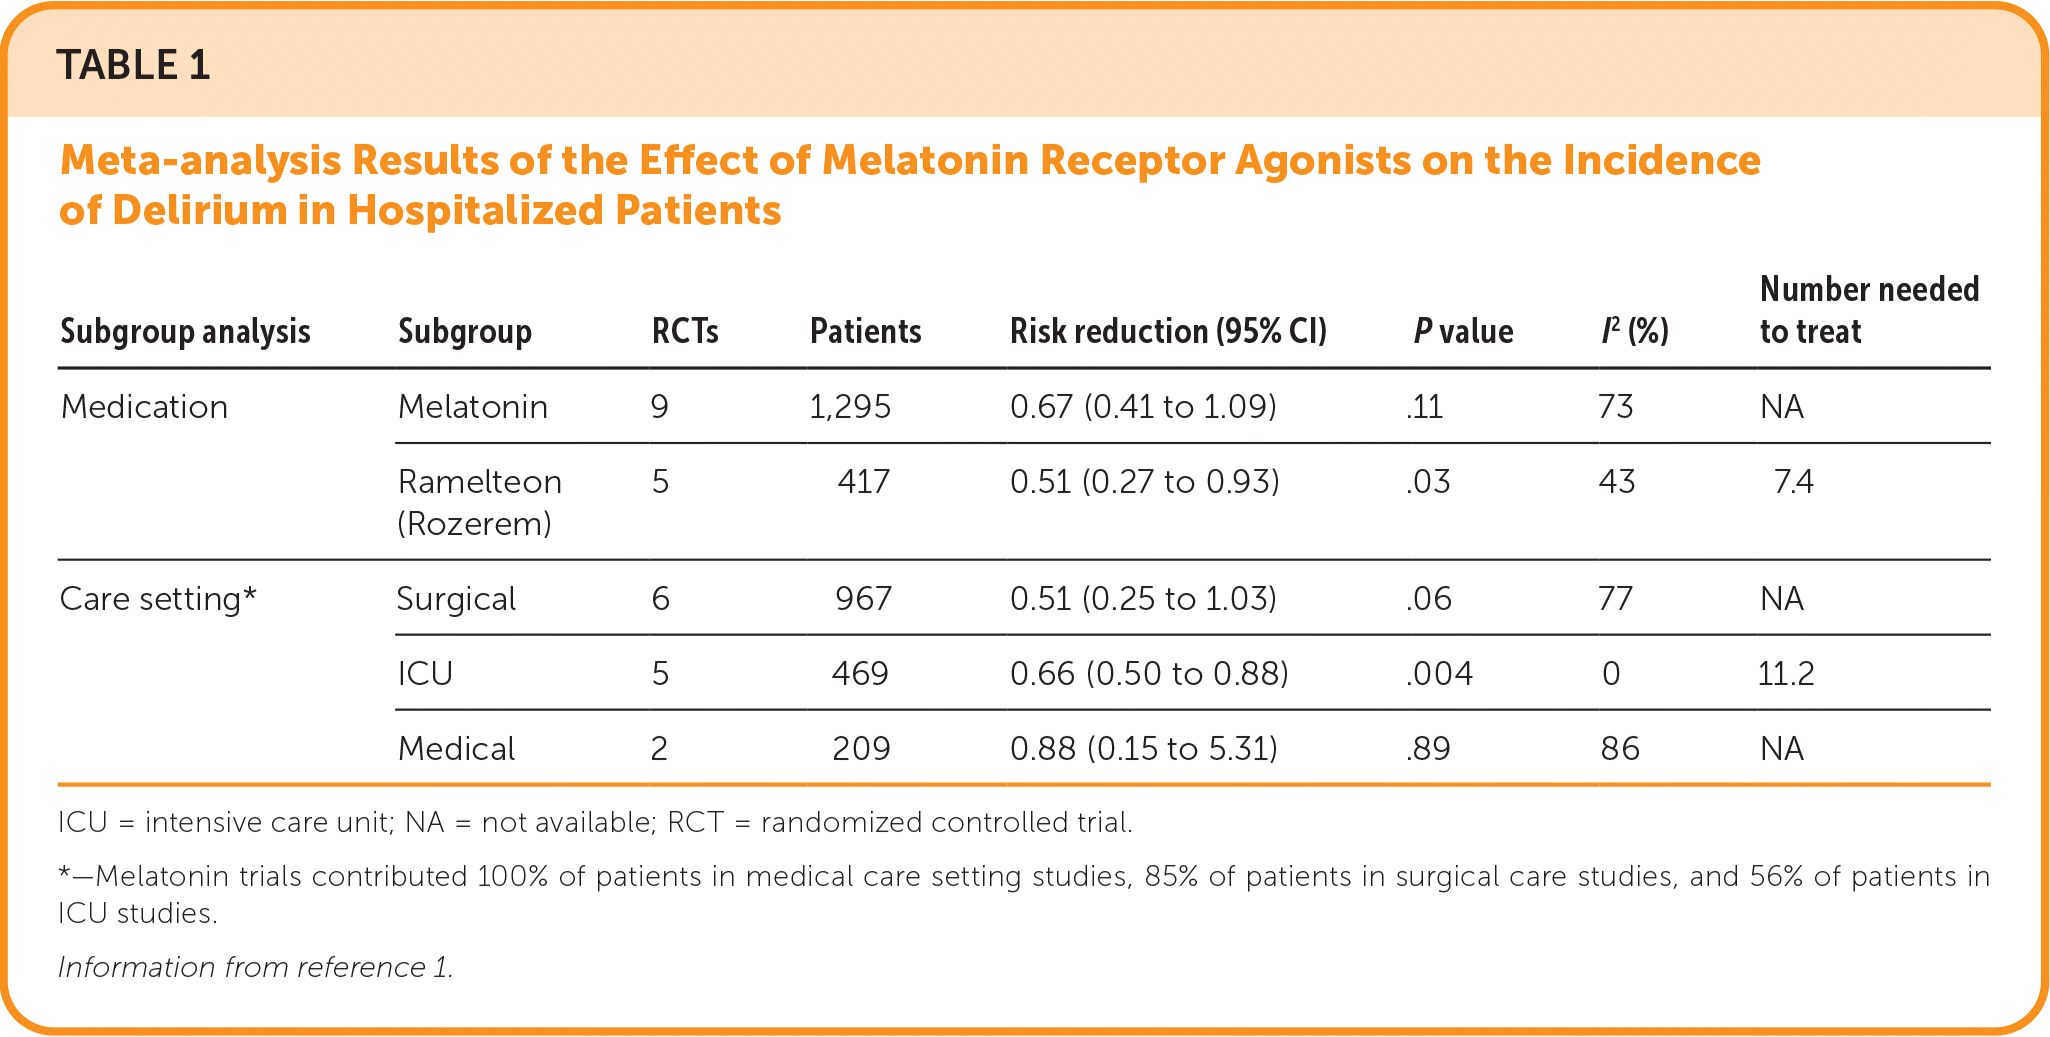
| Subgroup analysis | Subgroup | RCTs | Patients | Risk reduction (95% CI) | P value | I2 (%) | Number needed to treat |
|---|---|---|---|---|---|---|---|
| Medication | Melatonin | 9 | 1,295 | 0.67 (0.41 to 1.09) | .11 | 73 | NA |
| Ramelteon (Rozerem) | 5 | 417 | 0.51 (0.27 to 0.93) | .03 | 43 | 7.4 | |
| Care setting* | Surgical | 6 | 967 | 0.51 (0.25 to 1.03) | .06 | 77 | NA |
| ICU | 5 | 469 | 0.66 (0.50 to 0.88) | .004 | 0 | 11.2 | |
| Medical | 2 | 209 | 0.88 (0.15 to 5.31) | .89 | 86 | NA |
ICU = intensive care unit; NA = not available; RCT = randomized controlled trial.
*—Melatonin trials contributed 100% of patients in medical care setting studies, 85% of patients in surgical care studies, and 56% of patients in ICU studies.
Information from reference 1.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
