Family physicians often treat patients who require urinary management with the use of external urinary devices, clean intermittent catheterization, or indwelling urinary catheterization. External urinary devices are indicated for urinary incontinence (postvoid residual less than 300 mL), urine volume measurement for hospitalized patients, nonsterile urine diagnostic testing, improved comfort for patients in hospice or palliative care, and fall prevention for high-risk patients. Indwelling urinary catheterization is indicated for severe urinary retention or bladder outlet obstruction; wound healing in the sacrum, buttocks, or perineal area; prolonged immobilization; and as a palliative measure for patients who are terminally ill. Clean intermittent catheterization is an alternative to indwelling urinary catheterization for acute or chronic urinary retention (postvoid residual greater than 300 mL) without bladder outlet obstruction, sterile urine testing, postvoid residual volume assessment, and wound healing. Suprapubic catheter placement is considered when long-term catheterization is needed or urethral catheterization is not feasible. Urinary catheters should not be used solely for staff or caregiver convenience, incontinence-related dermatitis, urine culture procurement from a voiding patient, or initial incontinence management. Common complications of urinary catheter use include obstruction, bladder spasm, urine leakage, and skin breakdown of the sacrum, buttocks, or perineum. The risk of catheter-associated urinary tract infections increases with the duration of catheter use. Urologist referral is indicated for patients requiring urinary management who have recurrent urinary tract infections, acute infectious urinary retention, suspected urethral injury, or substantial urethral discomfort or if long-term catheterization is being considered.
Nearly 1 in 14 patients, mostly men 18 to 70 years of age in the community setting, has an indwelling urethral catheter at any point in time.1 In skilled nursing facilities, up to 36% of patients have indwelling catheters.2 The most common reasons for catheter use are spinal cord injuries and progressive multiple sclerosis.3 Common complications of urinary catheter use include urinary tract infection (UTI; 31% of patients), catheter blockage (24%), and accidental catheter dislodgement (12%).3 Family physicians often aid in initial catheter choice, provide routine care, and address complications for patients requiring urinary catheterization.4
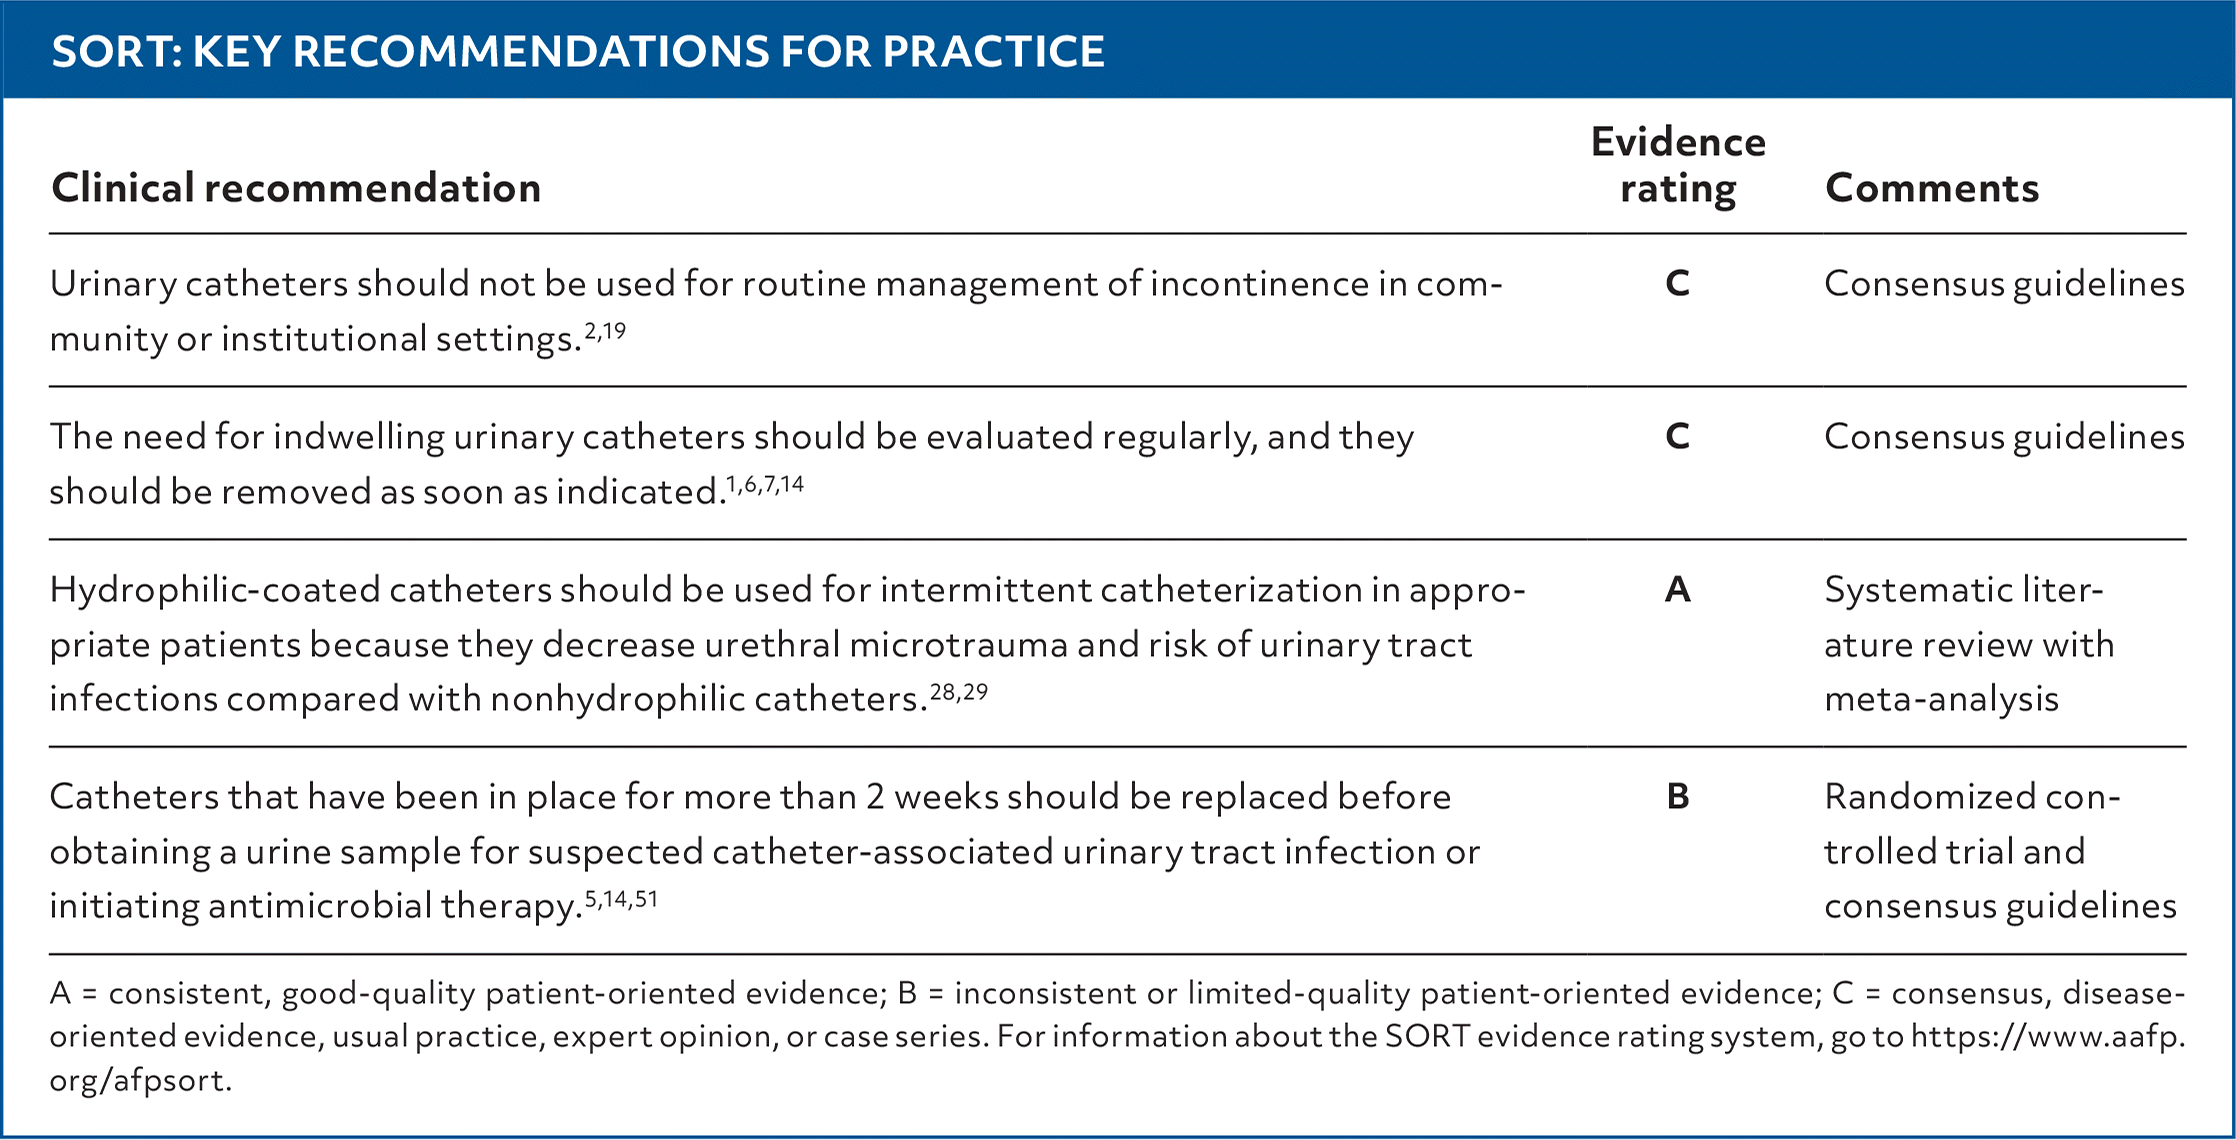
SORT: KEY RECOMMENDATIONS FOR PRACTICE
| Clinical recommendation | Evidence rating | Comments |
|---|---|---|
| Urinary catheters should not be used for routine management of incontinence in community or institutional settings.2,19 | C | Consensus guidelines |
| The need for indwelling urinary catheters should be evaluated regularly, and they should be removed as soon as indicated.1,6,7,14 | C | Consensus guidelines |
| Hydrophilic-coated catheters should be used for intermittent catheterization in appropriate patients because they decrease urethral microtrauma and risk of urinary tract infections compared with nonhydrophilic catheters.28,29 | A | Systematic literature review with meta-analysis |
| Catheters that have been in place for more than 2 weeks should be replaced before obtaining a urine sample for suspected catheter-associated urinary tract infection or initiating antimicrobial therapy.5,14,51 | B | Randomized controlled trial and consensus guidelines |
A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.
CATHETER TYPES AND CLINICAL INDICATIONS
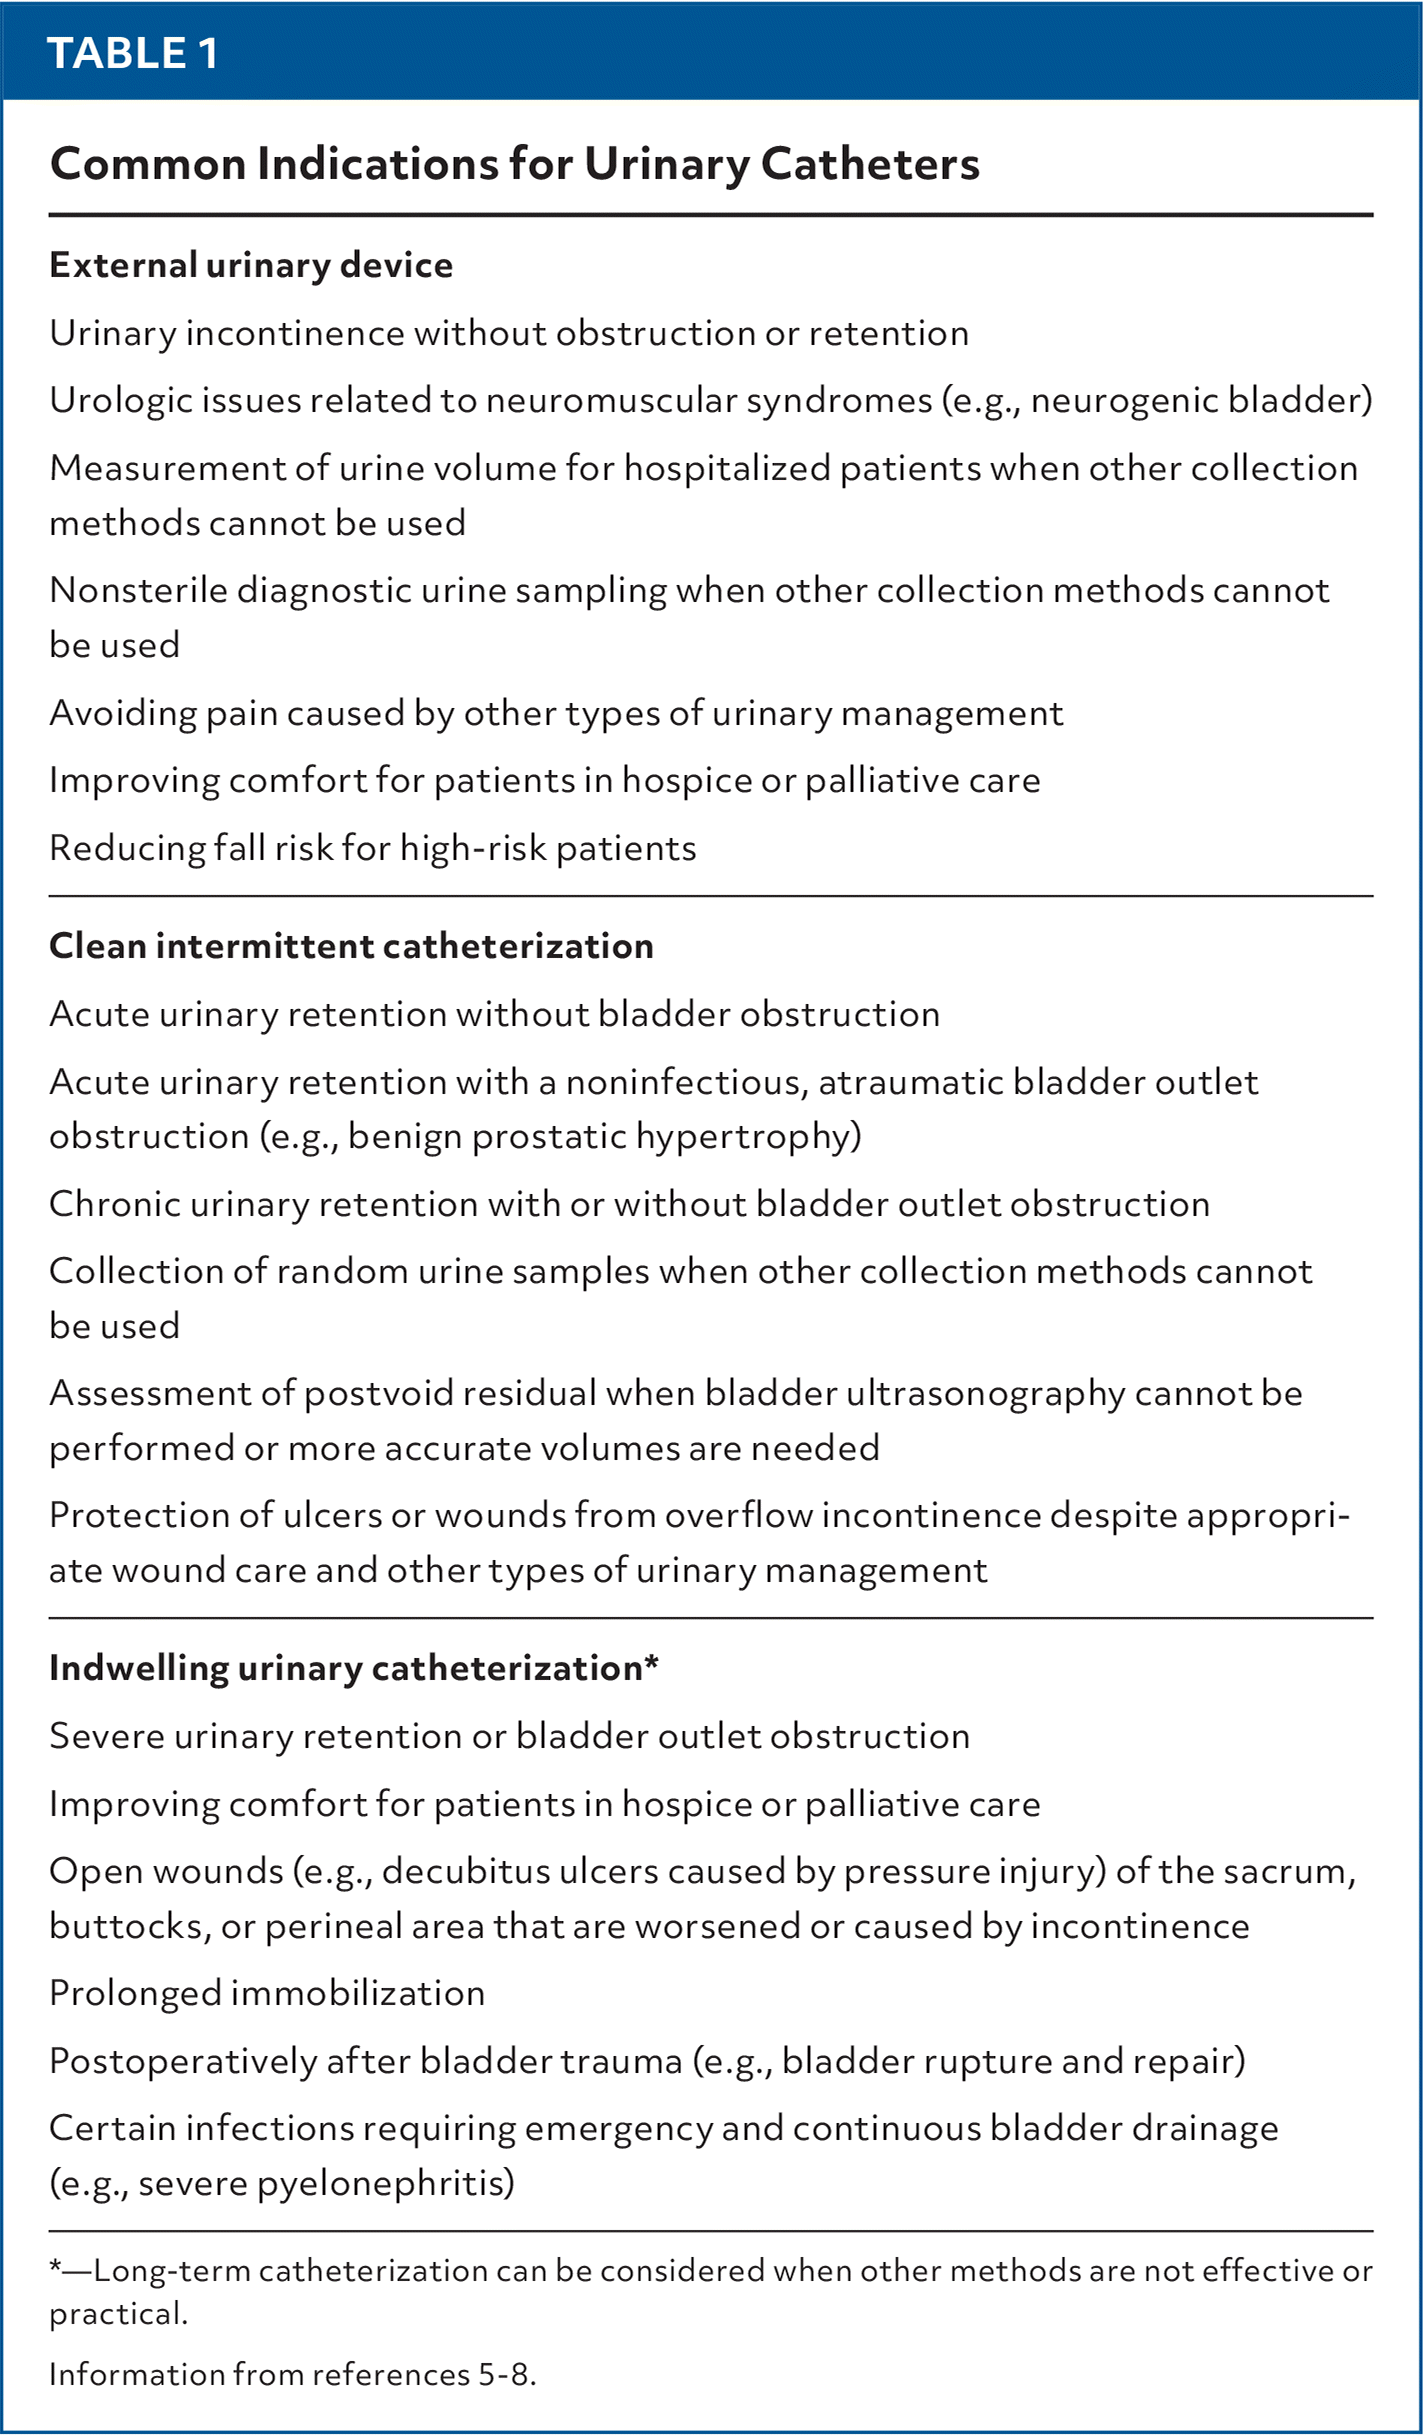
The three main options for urinary management are external urinary devices, clean intermittent catheterization, and indwelling urinary catheterization. The choice of catheter and duration of use depend on patient preference and clinical indications (Table 1).5–8
TABLE 1. Common Indications for Urinary Catheters
| External urinary device |
| Urinary incontinence without obstruction or retention |
| Urologic issues related to neuromuscular syndromes (e.g., neurogenic bladder) |
| Measurement of urine volume for hospitalized patients when other collection methods cannot be used |
| Nonsterile diagnostic urine sampling when other collection methods cannot be used |
| Avoiding pain caused by other types of urinary management |
| Improving comfort for patients in hospice or palliative care |
| Reducing fall risk for high-risk patients |
| Clean intermittent catheterization |
| Acute urinary retention without bladder obstruction |
| Acute urinary retention with a noninfectious, atraumatic bladder outlet obstruction (e.g., benign prostatic hypertrophy) |
| Chronic urinary retention with or without bladder outlet obstruction |
| Collection of random urine samples when other collection methods cannot be used |
| Assessment of postvoid residual when bladder ultrasonography cannot be performed or more accurate volumes are needed |
| Protection of ulcers or wounds from overflow incontinence despite appropriate wound care and other types of urinary management |
| Indwelling urinary catheterization* |
| Severe urinary retention or bladder outlet obstruction |
| Improving comfort for patients in hospice or palliative care |
| Open wounds (e.g., decubitus ulcers caused by pressure injury) of the sacrum, buttocks, or perineal area that are worsened or caused by incontinence |
| Prolonged immobilization |
| Postoperatively after bladder trauma (e.g., bladder rupture and repair) |
| Certain infections requiring emergency and continuous bladder drainage (e.g., severe pyelonephritis) |
*—Long-term catheterization can be considered when other methods are not effective or practical.
External Urinary Devices
External urinary devices are noninvasive and overlie the urinary meatus, protecting the skin from urine leakage. Patients with penises use a penile sheath drainage system (i.e., condom catheter), with drainage of urine from the distal end of the sheath into an attached bag. For patients with vaginas, the device is placed in the perineal area and diverts urine via a wicking process involving low suction. Patients with external urinary devices must be able to effectively empty their bladder during urination.
External urinary devices are best used for urinary incontinence without obstruction or substantial postvoid residual6 (less than 300 mL9,10). Contraindications for use of external urinary devices include substantial postvoid residual (greater than 300 mL), obstructive urologic disease, allergy to the catheter materials, anatomic abnormalities, and sensitivity to adhesive.8 Whereas external urinary devices have greater patient satisfaction than indwelling urinary catheterization or clean intermittent catheterization, complications can include skin irritation and pressure injury from device attachment mechanisms.8,11,12
Clean Intermittent Catheterization
Clean intermittent catheterization drains the bladder under clean, nonsterile conditions via urethral catheterization at the time of intended voiding (e.g., straight catheterization). This type of catheterization is indicated for patients with acute urinary retention (postvoid residual greater than 300 mL) without bladder outlet obstruction.9,13 It also can be used with bladder outlet obstruction for noninfectious or atraumatic acute urinary retention or overflow incontinence (e.g., benign prostatic hypertrophy). Clean intermittent catheterization is an alternative to indwelling urinary catheterization for chronic urinary retention to minimize the risk of catheter-associated UTI.6,14
Clean intermittent catheterization enables patients to manage their urinary health independently, which can enhance quality of life.5,14–17 However, hand dexterity, coordination, and a hygienic environment are required.16 Because of potential physical discomfort, this method might be less desired in the palliative care setting. Clean intermittent catheterization is contraindicated for patients with high internal bladder pressure, in whom continuous drainage minimizes renal damage.5
Indwelling Urinary Catheterization
Indwelling urinary catheters (e.g., Foley catheters, suprapubic catheters) allow for the continuous flow of urine. The collecting systems are held in place within the bladder by an inflatable balloon (usually 5 to 10 mL). Typical catheter size for adults ranges from 12 to 16 Fr.5,18
The need for indwelling urinary catheters should be evaluated regularly, and they should be removed as soon as indicated.6,7,14 Any urethral catheterization is contraindicated if the patient does not want it or in the setting of undiagnosed hematuria, urethral infection, priapism, urethral trauma, urethral discomfort, low bladder compliance, or untreated bladder cancer.5
Suprapubic catheters are indwelling urinary catheters that pass percutaneously through the anterior abdominal wall directly into the bladder. They involve less ongoing physical discomfort than other catheters and are often considered when long-term catheterization is necessary and urethral catheterization is not feasible or is undesired (Table 2).5,15,19,20 Contraindications for suprapubic catheters include a nondistended or nonpalpable bladder, bladder cancer, abdominal wall sepsis, pregnancy, intrinsic sphincter deficiency, detrusor hyperreflexia or instability, and history of pelvic irradiation.5,6,15,18
TABLE 2. Advantages and Disadvantages of Suprapubic Catheters

| Advantages |
| Avoids urinary meatus penile pressure injury or discomfort |
| Avoids urethral trauma or stricture |
| Can attempt normal void without need for removal and potential recatheterization |
| Increased comfort |
| Less interference with sexual activity |
| A long-term suprapubic catheter is recommended as an alternative to indwelling urinary catheterization for women with urinary incontinence and pelvic organ prolapse |
| Can decrease risk of catheter-associated bacteriuria and catheter-associated urinary tract infection compared with indwelling urethral catheterization |
| Disadvantages |
| Altered body image |
| Cystostomy site can form hypergranulation and lead to stricture formation |
| Greater occurrence of bladder stone formation (due to catheter encrustation over time) compared with external urinary devices |
| Leakage from urethra can still occur |
| Most invasive method of catheterization with inherent surgical risks (e.g., bleeding, failure of drainage, infection, visceral injury, bowel perforation) |
Duration of Use and General Contraindications
The Centers for Disease Control and Prevention uses 30 days as the cutoff time for short- vs. long-term catheterization, whereas the World Health Organization uses a 10-day cutoff.6,21 Benign prostatic hyperplasia, pelvic organ prolapse, or pelvic masses (e.g., fibroids) can cause urinary retention and may require short-term catheterization. Irreversible causes of urinary retention that may require long-term catheterization include progressive multiple sclerosis, Parkinson disease, stroke, and spinal cord injury.
For long-term catheterization, external urinary devices and clean intermittent catheterization should be considered before indwelling urinary catheterization because of the lower risk of UTI.14,22–25 Urinary catheters should not be used for routine management of incontinence in community or institutional settings.2,19 Urinary catheters should not be used solely for staff or caregiver convenience, incontinence-related dermatitis, urine culture procurement from a voiding patient, or initial incontinence management.5,6,14
ROUTINE MANAGEMENT OF CATHETERS
Lubrication and Catheter Material
Water-soluble lubrication, ideally with local anesthetic, is recommended to minimize patient discomfort and risk of infection during insertion.5,6,15 Water-soluble sterile lubricating jelly without lidocaine is available over the counter, whereas water-soluble sterile lidocaine gel in a syringe (20 mg per 5 mL) is available by prescription.26
Petroleum-based lubricants (e.g., white petrolatum jelly) should be avoided because they can degrade latex and silicone catheters.27 When available, hydrophilic-coated catheters decrease urethral microtrauma and strictures, have a lower risk of UTI, and improve patient comfort and satisfaction compared with nonhydrophilic catheters.28,29
Proper Insertion
Catheters are often placed by nursing staff; however, family physicians may need to assist with difficult urethral catheter placement. Proper clinician training for catheter insertion and adherence to best practices can help ensure successful placement, minimize discomfort, and decrease the risk of infection.6,17
The American Urological Association provides guidance on proper Foley catheter placement.
Balloon Inflation and Indwelling Urinary Catheter Securement
Proper inflation of the catheter balloon (usually 5 to 10 mL) with sterile water or saline prevents dislodgement, ensures stability, and minimizes complications. Overinflation can lead to bladder irritation, whereas underinflation can cause catheter migration or urine leakage.5,15,18,30,31 Proper positioning of the catheter is maintained with securement devices, such as adhesive tape, leg straps, and adhesive anchors, to prevent urethral traction, ensure patient comfort, and minimize trauma.5,18,30,31
Catheter Maintenance
Daily cleaning of the catheter and urethral meatus with soap and water helps prevent infection.5,6,32 However, the incidence of UTI in catheterized patients is not affected by use of aseptic vs. clean insertion techniques, coated vs. uncoated catheters, or single- vs. multiuse catheters.16 The catheter tubing should be monitored to prevent kinking and obstruction.5,6 Catheter bags should be kept below the level of the bladder to aid in drainage and decrease the risk of urinary reflux, which can lead to infection.5,6,14,20 Maintaining hydration ensures a continuous flow of urine, decreasing the chance of catheter blockage and UTI. Constipation should be treated appropriately because stool burden can put pressure on the bladder and directly affect catheter function.5,32
Replacement Schedule for Long-term Indwelling Catheters in Adults
Long-term catheters must be replaced immediately if any catheter-related damage or problems (e.g., obstruction) are identified.31,32 Whereas most urologic organizations recommend replacement of long-term catheters every four weeks (the maximum recommended duration is 12 weeks), replacement should ideally be based on clinical and individual needs rather than on a fixed schedule.5,18,20,32,33 An individualized approach can minimize discomfort, decrease the risk of infection, and decrease meatal or urethral trauma during replacement.30,34 Although empiric antibiotic prophylaxis is not recommended, culture-guided antibiotic prophylaxis can be considered for patients with a history of symptomatic UTI after catheter replacement or who experience trauma during catheterization.20,31,34 Screening urine cultures are not recommended during long-term catheter use.6,32
Catheter Removal and Postcatheter Care and Monitoring
Complete deflation of the catheter balloon and strict aseptic methods are essential to prevent complications during catheter removal.6,7 During removal, passive deflation of the catheter balloon is recommended to avoid creating painful ridging of the balloon.32 Performing a voiding trial, which involves monitoring for spontaneous urination within a 6-hour period after catheter removal, and checking a postvoid residual via ultrasonography can identify urinary retention and influence decisions regarding catheter reinsertion or other interventions. 5,19,35
Patients should receive detailed education on postremoval care, focusing on hygiene and monitoring of symptoms to enhance recovery outcomes and comfort.18,36 Mild to moderate postremoval pain or discomfort that worsens or fails to improve or signs of infection require follow-up.5,14 Symptoms of severe pain, substantial urethral bleeding, or sudden inability to urinate should prompt emergency evaluation.
Bladder training with catheter clamping before removal is not recommended because it can lead to a greater incidence of UTI and a longer time to first void, particularly for patients with catheters used for less than 7 days.37 [corrected] However, postremoval bladder training exercises, such as scheduled and delayed voiding, can help rebuild bladder capacity and improve urinary control, whereas pelvic floor exercises can help mitigate urinary retention for patients who used long-term catheters.16,20,38
COMPLICATIONS OF LONG-TERM CATHETER USE
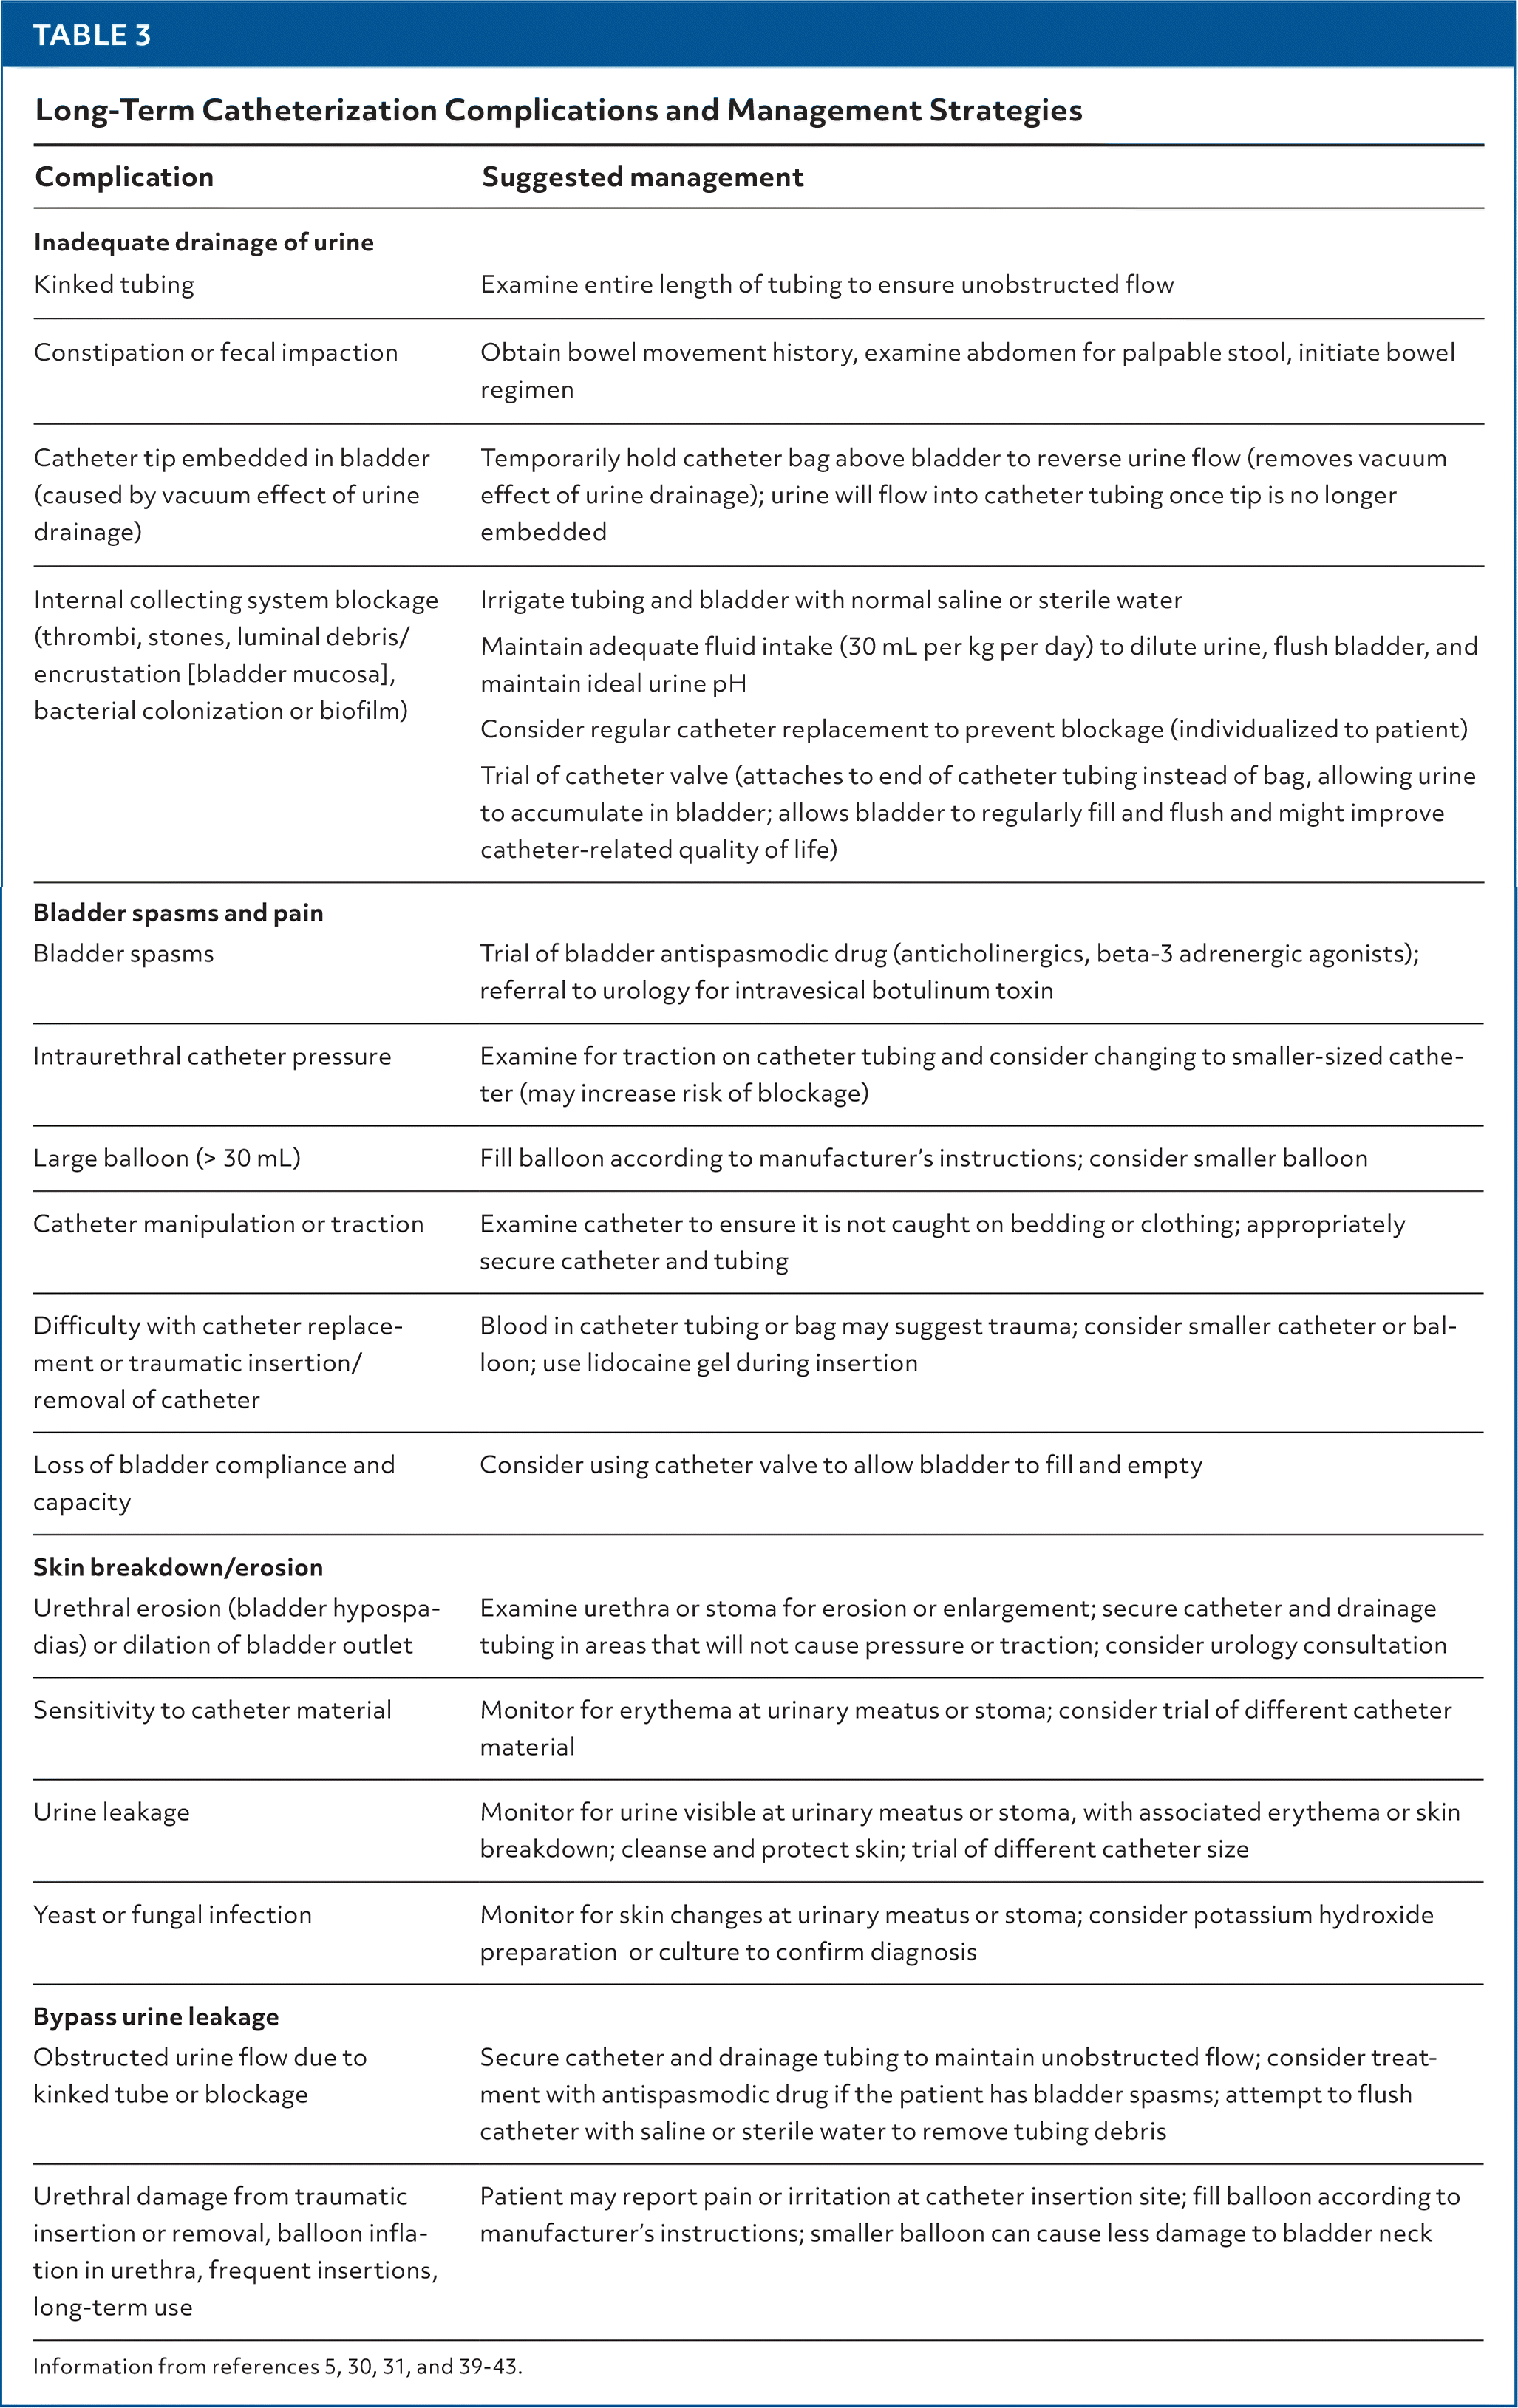
Long-term catheter use is associated with complications such as urinary obstruction, bladder spasms, skin breakdown, and urine leakage (Table 3).5,30,31,39–43 Up to 40% of patients with urinary catheters may experience restricted activities of daily living, and up to 43% may report restricted social activities.41 Sexual dysfunction after catheter removal occurs in 5% of patients.41
TABLE 3. Long-Term Catheterization Complications and Management Strategies
| Complication | Suggested management |
|---|---|
| Inadequate drainage of urine | |
| Kinked tubing | Examine entire length of tubing to ensure unobstructed flow |
| Constipation or fecal impaction | Obtain bowel movement history, examine abdomen for palpable stool, initiate bowel regimen |
| Catheter tip embedded in bladder (caused by vacuum effect of urine drainage) | Temporarily hold catheter bag above bladder to reverse urine flow (removes vacuum effect of urine drainage); urine will flow into catheter tubing once tip is no longer embedded |
| Internal collecting system blockage (thrombi, stones, luminal debris/encrustation [bladder mucosa], bacterial colonization or biofilm) | Irrigate tubing and bladder with normal saline or sterile water Maintain adequate fluid intake (30 mL per kg per day) to dilute urine, flush bladder, and maintain ideal urine pH Consider regular catheter replacement to prevent blockage (individualized to patient) Trial of catheter valve (attaches to end of catheter tubing instead of bag, allowing urine to accumulate in bladder; allows bladder to regularly fill and flush and might improve catheter-related quality of life) |
| Bladder spasms and pain | |
| Bladder spasms | Trial of bladder antispasmodic drug (anticholinergics, beta-3 adrenergic agonists); referral to urology for intravesical botulinum toxin |
| Intraurethral catheter pressure | Examine for traction on catheter tubing and consider changing to smaller-sized catheter (may increase risk of blockage) |
| Large balloon (> 30 mL) | Fill balloon according to manufacturer's instructions; consider smaller balloon |
| Catheter manipulation or traction | Examine catheter to ensure it is not caught on bedding or clothing; appropriately secure catheter and tubing |
| Difficulty with catheter replacement or traumatic insertion/removal of catheter | Blood in catheter tubing or bag may suggest trauma; consider smaller catheter or balloon; use lidocaine gel during insertion |
| Loss of bladder compliance and capacity | Consider using catheter valve to allow bladder to fill and empty |
| Skin breakdown/erosion | |
| Urethral erosion (bladder hypospadias) or dilation of bladder outlet | Examine urethra or stoma for erosion or enlargement; secure catheter and drainage tubing in areas that will not cause pressure or traction; consider urology consultation |
| Sensitivity to catheter material | Monitor for erythema at urinary meatus or stoma; consider trial of different catheter material |
| Urine leakage | Monitor for urine visible at urinary meatus or stoma, with associated erythema or skin breakdown; cleanse and protect skin; trial of different catheter size |
| Yeast or fungal infection | Monitor for skin changes at urinary meatus or stoma; consider potassium hydroxide preparation or culture to confirm diagnosis |
| Bypass urine leakage | |
| Obstructed urine flow due to kinked tube or blockage | Secure catheter and drainage tubing to maintain unobstructed flow; consider treatment with antispasmodic drug if the patient has bladder spasms; attempt to flush catheter with saline or sterile water to remove tubing debris |
| Urethral damage from traumatic insertion or removal, balloon inflation in urethra, frequent insertions, long-term use | Patient may report pain or irritation at catheter insertion site; fill balloon according to manufacturer's instructions; smaller balloon can cause less damage to bladder neck |
Common complications of clean intermittent catheterization include UTI, urethral trauma or bleeding, creation of false passages, hematuria, and stricture formation.16 Inflation valve malfunction, damage to the inflation canal, or obstruction of the inflation canal by solute crystallization can prevent the catheter balloon from deflating. Cutting the tubing proximal to the inflation valve or passing a wire through the inflation channel tubing can help to remove or disperse obstructing crystals.44
Bacteriuria, Bacterial Colonization, and Catheter-Associated UTI
The incidence of bacteriuria associated with indwelling catheterization is 3% to 8% per day, often leading to asymptomatic bacteriuria.14,15,45,46 The risk of UTI increases with length of catheter use; 15% of patients develop a UTI after three days of use, and 68% of patients develop a UTI after eight days.46
Almost 6% of the 70.4 million catheterized adult patients discharged from U.S. hospitals from 2001 to 2010 developed catheter-associated UTIs.15,47,48 These UTIs are diagnosed in patients who are currently catheterized or who have had a catheter removed within the previous 48 hours who have bacteriuria with signs or symptoms attributable to UTI (Table 4).14 Female sex, age older than 60 years, and not maintaining a closed catheter system (self-contained catheter housed within its own collection bag) are associated with increased risk of catheter-associated UTI.7,48
TABLE 4. Infectious Diseases Society of America Diagnostic Criteria for Catheter-Associated Urinary Tract Infection

| Presence of symptoms or signs compatible with urinary tract infection and no other identified source of infection or cause: |
| Acute hematuria |
| Costovertebral angle tenderness |
| Dysuria, urgent or frequent urination, or suprapubic pain or tenderness in patients whose catheter has been removed within the previous 48 hours |
| Flank pain |
| Increased spasticity, autonomic dysreflexia, or sense of unease in patients with spinal cord injury |
| New onset or worsening of fever, rigors, altered mental status, malaise, or lethargy |
| Pelvic discomfort |
| and |
| ≥ 103 colony-forming units per mL of one or more bacterial species in a single catheter urine specimen or in a midstream voided urine specimen from a patient whose urethral, suprapubic, or condom catheter has been removed within the previous 48 hours |
Information from reference 14.
Typical symptoms of catheter-associated UTI include fever, chills, abdominal or flank pain, and changes in urine consistency.15 Proper management of urinary catheters can prevent complications for up to 65% to 70% of patients.49,50 Catheters that have been in place for more than 2 weeks should be replaced before obtaining a urine sample or initiating antimicrobial therapy.5,14,51 The American Urological Association recommends against daily antibiotic prophylaxis to prevent UTI for patients who use a urinary catheter.52 Antimicrobial-coated catheters, systemic antimicrobial prophylaxis, methenamine salts, cranberry products, and catheter irrigation with antimicrobials should not routinely be used to decrease the risk of bacteriuria or catheter-associated UTI.7,14
INDICATIONS FOR UROLOGY REFERRAL
Referral should be considered when long-term catheterization is being considered or patients requiring urinary management have recurrent UTIs, acute infectious urinary retention (e.g., prostatitis), suspected urethral injury, or substantial urethral discomfort.9,53
This article updates a previous article on this topic by Cravens and Zweig.18
Data Sources: A search of PubMed, the Cochrane Database of Systematic Reviews, Essential Evidence Plus, and the Agency for Healthcare Research and Quality was performed using the key words/phrases urinary catheter, urinary catheter indications, catheter maintenance, complications of urinary catheters, and catheter-associated UTI. Results were filtered by English language. Search dates: May 2023 and August 2024.