

Chronic cough is a cough lasting longer than 8 weeks in adults and 4 weeks in children. In the United States, more than 12.3 million individuals are estimated to have chronic cough. The most common causes of chronic cough in adults are upper airway cough syndrome, asthma, nonasthmatic eosinophilic bronchitis, gastroesophageal reflux disease, and laryngopharyngeal reflux. The initial assessment of chronic cough should include cost-effective diagnostic tests, such as chest radiography and spirometry, and empiric and targeted treatment for the most common etiologies. An assessment of medications (e.g., angiotensin-converting enzyme inhibitors), environment, occupation, and potential chemical triggers should be conducted. For chronic refractory cough, physiotherapy and speech and language therapy combined with a trial of gabapentin or amitriptyline can be considered. When initial test findings are unremarkable, further diagnostic tests, such as bronchoscopy and nasendoscopy, are often warranted through referral to a pulmonologist and otolaryngologist. Common etiologies in children include protracted bacterial bronchitis, asthma, bronchiectasis, upper airway cough syndrome, and gastroesophageal reflux disease. Because of the high likelihood of spontaneous resolution, children with a dry cough without wheezing or exertional dyspnea may be observed for 2 weeks.
Chronic cough is estimated to affect 5% of the U.S. adult population (12.3 million individuals).1 The American College of Chest Physicians (CHEST) defines chronic cough as a persistent cough lasting longer than 8 weeks in adults and 4 weeks in children.2,3 According to the Centers for Disease Control and Prevention, cough of undifferentiated duration is the second most common reason that patients present to primary care ambulatory settings.4 Chronic cough can negatively impact quality of life and daily activities, which can increase the risk of depression and anxiety.5–7
SORT: KEY RECOMMENDATIONS FOR PRACTICE
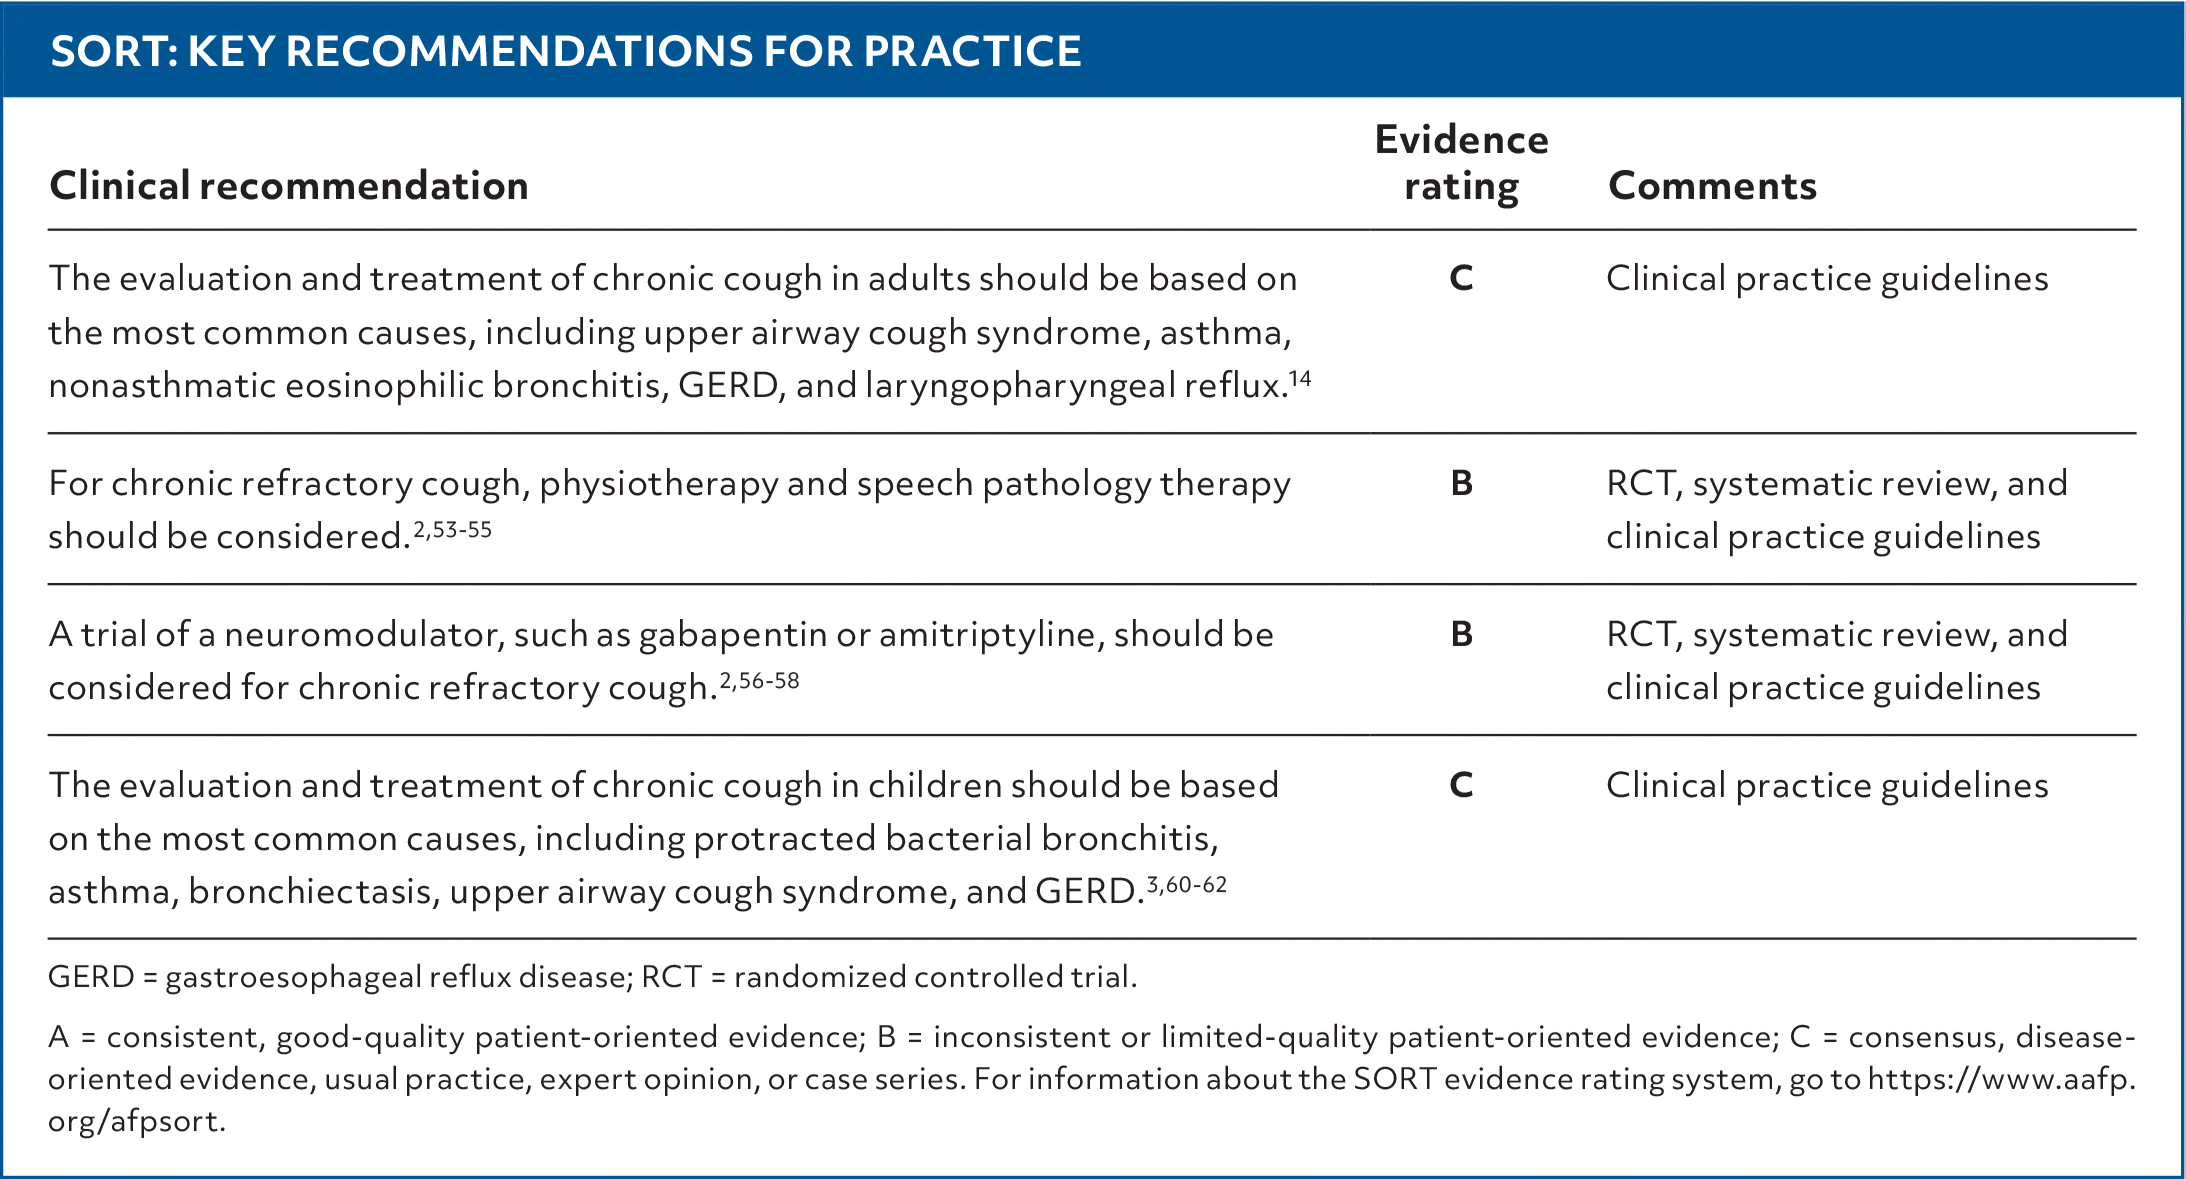
| Clinical recommendation | Evidence rating | Comments |
|---|---|---|
| The evaluation and treatment of chronic cough in adults should be based on the most common causes, including upper airway cough syndrome, asthma, nonasthmatic eosinophilic bronchitis, GERD, and laryngopharyngeal reflux.14 | C | Clinical practice guidelines |
| For chronic refractory cough, physiotherapy and speech pathology therapy should be considered.2,53–55 | B | RCT, systematic review, and clinical practice guidelines |
| A trial of a neuromodulator, such as gabapentin or amitriptyline, should be considered for chronic refractory cough.2,56–58 | B | RCT, systematic review, and clinical practice guidelines |
| The evaluation and treatment of chronic cough in children should be based on the most common causes, including protracted bacterial bronchitis, asthma, bronchiectasis, upper airway cough syndrome, and GERD.3,60–62 | C | Clinical practice guidelines |
GERD = gastroesophageal reflux disease; RCT = randomized controlled trial.
A = consistent, good-quality patient-oriented evidence; B = inconsistent or limited-quality patient-oriented evidence; C = consensus, disease-oriented evidence, usual practice, expert opinion, or case series. For information about the SORT evidence rating system, go to https://www.aafp.org/afpsort.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.
