Clinical Question
How is carpal tunnel syndrome (CTS) diagnosed clinically and how can the history and physical examination inform evidence-based management?
Evidence Summary
CTS is the most common entrapment neuropathy seen in primary care. It is caused by compression of the median nerve in the space underneath the wrist flexor retinaculum, which can produce pain in the wrist or lateral digits and thumb, paresthesia, and, in severe cases, sensory loss and weakness or atrophy of thenar muscles.
History and physical examination elements, including provocative tests, have limited accuracy compared with electrodiagnostic testing for the diagnosis of CTS. The Phalen sign has a positive likelihood ratio (LR+) of 1.4 and a negative likelihood ratio (LR−) of 0.7, and the Tinel sign has an LR+ of 1.3 and LR− of 0.8.1,2 Hypalgesia in the median nerve distribution is minimally to moderately useful for ruling in CTS, with an LR+ of 3.1, and weak thumb abduction has an LR+ of 1.8.1 A systematic review concluded that the Katz hand sensory symptom diagrams may be useful.1 According to an evidence-based guideline from the American Academy of Orthopaedic Surgery, there is strong evidence that no test alone can diagnose CTS, but the presence of thenar atrophy is useful for ruling in CTS.3 The majority of studies that examined sensitivity and specificity of history and physical examination findings for CTS were performed in specialty settings, limiting the usefulness of these findings in primary care. However, one study found that 81% of patients referred by family physicians for clinically suspected CTS had the diagnosis confirmed by a neurologist.4
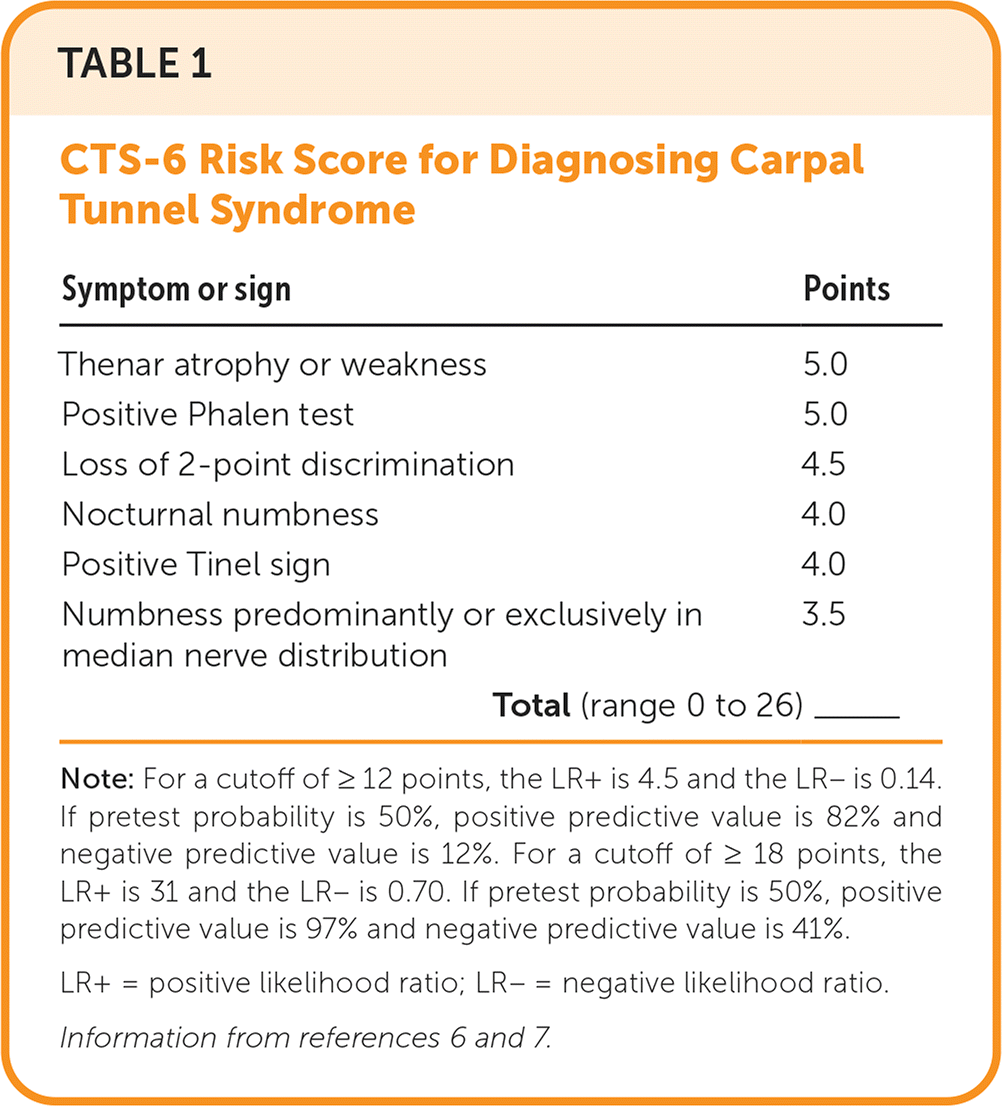
The CTS-6, a validated risk score, is useful for making the diagnosis and assessing severity of CTS.5 The CTS-6 assigns points for six signs and symptoms (Table 16,7 ). Although there is no consensus on a diagnostic reference standard for CTS, a 2014 study found that compared with electrodiagnostic testing, a CTS-6 score of 12 or more had a sensitivity of 89%, a specificity of 80%, an LR+ of 4.5, and an LR− of 0.14.6 A CTS-6 score of 18 or more is 99% specific for CTS, but is only 31% sensitive (LR+ = 31, LR− = 0.70).7
TABLE 1. CTS-6 Risk Score for Diagnosing Carpal Tunnel Syndrome
| Symptom or sign | Points |
|---|---|
| Thenar atrophy or weakness | 5.0 |
| Positive Phalen test | 5.0 |
| Loss of 2-point discrimination | 4.5 |
| Nocturnal numbness | 4.0 |
| Positive Tinel sign | 4.0 |
| Numbness predominantly or exclusively in median nerve distribution | 3.5 |
| Total (range 0 to 26) | _____ |
Note: For a cutoff of ≥ 12 points, the LR+ is 4.5 and the LR− is 0.14. If pretest probability is 50%, positive predictive value is 82% and negative predictive value is 12%. For a cutoff of ≥ 18 points, the LR+ is 31 and the LR− is 0.70. If pretest probability is 50%, positive predictive value is 97% and negative predictive value is 41%.
LR+ = positive likelihood ratio; LR− = negative likelihood ratio.
Read the full article
Get immediate access, anytime, anywhere.
Choose a single article, issue, or full-access subscription.
Earn up to 14 CME credits per issue.